


Beth root (Trillium erectum L.), Melanthiaceae
Australian Herbal Pharmacopoeia (working title) · Monograph AIP-PH-TRIERE · Version 1.0 draft
Date: 2026
Status: working document, version 1.0. Not a statutory standard.
Prepared by: the Australian Institute of Pharmacognosy, Far North Queensland, Australia. Every author and contributor is named at the end of the monograph.

0. Free-teaser block
0.1 Identity card
| Register number | AIP-PH-TRIERE (MediHerb A–Z list No. 14) |
| Title | Beth root (Trillium erectum L.), Trillii erecti rhizoma |
| Version / year | 1.0 draft, 2026. Next review 2029, or sooner if a human study of beth root reports, or when the two primary phytochemical papers now being obtained in full text are read |
| Accepted binomial | Trillium erectum L., Species Plantarum: 340 (1753), conserved name (nom. cons.). Accepted in the World Checklist of Vascular Plants (WCVP), version 16.0 of 04/06/2026, the dataset that Plants of the World Online displays, read through ChecklistBank in September 2026; IPNI 304585-2 [1] |
| Family | Melanthiaceae (APG IV placement used by WCVP). Older texts place Trillium in Liliaceae, Smilaceae or a separate Trilliaceae [1,8,10,20] |
| Plant part | Dried rhizome with its attached roots, sold in the Australian trade as "root" [8,9,13] |
| Latin drug name | Trillii erecti rhizoma (AIP form). The US National Formulary IV called the drug "Trillium", the dried rhizome [8] |
| Principal synonyms | Trillium pendulum Willd. (the name of the Eclectic drug and of two cytotoxicity screens), T. rhomboideum Michx. (homotypic), T. foetidum Salisb., T. purpureum Elliott, T. atropurpureum Raf., T. flavum Raf., T. obovatum Pursh; T. erectum var. album (Michx.) Pursh is not listed by WCVP; var. atropurpureum (Michx.) Pursh and var. flavum Torr. are heterotypic synonyms [1,10,23,24,27] |
| Common names | English: beth root, bethroot, birthroot, wake-robin, red trillium, purple trillium, stinking Benjamin, Indian balm, ground lily [10,15]. French (Québec): trille rouge, trille dressé [17] |
| Pharmacopoeial status elsewhere | US National Formulary IV (1916): yes, "Trillium", the dried rhizome, ash not more than 5 per cent, quoted in the US Dispensatory 1918 [8]; not in the current USP–NF. Ph. Eur., BP, WHO, EMA/HMPC, ChP, API: no monograph found. No German Commission E or ESCOP monograph was found in the sources read. The British Herbal Pharmacopoeia is not among the sources read for this edition, so its status is left open (section 18) |
| Australian status | Permissible Ingredients Determination: yes, item 5035 TRILLIUM ERECTUM, purposes A (active) and H (homoeopathic), no specific requirements [2]. Poisons Standard: not named, and neither diosgenin nor any saponin is scheduled [3]. Not recorded growing in Australia: of 102 Trillium records in the Atlas of Living Australia none was collected in Australia [4]. Not native, so no Nature Conservation Act 1992 (Qld) permit applies; not a prohibited or restricted invasive plant under the Biosecurity Act 2014 (Qld) [5,44] |
| Named markers | Diosgenin (CID 99474), after acid hydrolysis: identity; no limit. Pennogenin (CID 12314056), after acid hydrolysis: identity, proposed; no limit. Steroidal saponins, total: assay proposed, no limit set anywhere (sections 7, 18). Ash: not more than 5 per cent (NF IV) [8] |
| Evidence snapshot | Heavy menstrual bleeding: Tier T, 0 trials. Vaginal discharge (topical douche): Tier T, 0 trials. Aid to labour and post-partum bleeding: Tier T, 0 trials, and a pregnancy caution applies. Cough with bleeding or heavy expectoration: Tier T, 0 trials. Hormone-regulating effect: Tier P, hypothesis from chemistry only. Cytotoxicity: Tier P, 2 cell-line screens of retail root [11,13,20,23,24] |
| Suggested citation | Ridley T, Iggulden L. Beth root (Trillium erectum L.), Trillii erecti rhizoma. AIP-PH-TRIERE, version 1.0 draft. Cardwell: Australian Institute of Pharmacognosy; 2026. DOI to be assigned |
| Provenance | Original AIP data: none. Every analytical figure, limit, method and dose belongs to the source cited beside it. Sections 4, 5, 7, 8, 9 and 10 carry AIP bench data pending (no AIP voucher, section, plate or run yet). The map (Figure 9), charts (Figures 10–15) and drawings (Figures 3d, 5, 6) are AIP drawings from cited data |
| Compiler and review | Compiled by Dr Thomas Ridley (Education and Research). Technical review: Dr Fiona MacAllister (Botanical, sections 1-5, 10), reviewed in 2026; Dr Hana Suzuki (QA, sections 6-10), reviewed in 2026; Dr Eleanor Whitcombe (Medicine, sections 12, 13, 15), reviewed in 2026; Dr Thomas Ridley (Education and Research, evidence and citation audit of all sections and figures), reviewed in 2026; Jesse Kirby (Community Outreach, layout, figure placement, captions and credit lines, all sections), reviewed in 2026. Sections 11, 14 and 16–18 still await a reader outside Education and Research. Published: not yet. Last modified: 2026. Version 1.0 draft |
| Canonical URL | /pharmacopoeia/trillium-erectum/ (on publication) |

0.2 Summary
Beth root is the dried rhizome of Trillium erectum, a spring-flowering woodland perennial of eastern Canada and the eastern United States. It does not grow wild in Australia and is imported. No current pharmacopoeia carries it. The last official standard was the US National Formulary IV (1916), which described a short, obconical, ringed rhizome and set an ash limit of 5 per cent. A 1920 pharmacognosy text gives the microscopy: starch-filled parenchyma, scattered leptocentric bundles and needle crystals of calcium oxalate.
The chemistry is steroidal. Laboratory work has isolated spirostanol and furostanol saponins built on diosgenin and pennogenin, and the older literature adds tannin, fixed oil and starch. Nobody has published a content limit for any constituent, and nobody has published a TLC or HPLC fingerprint of the drug itself. Sections 8 and 9 therefore propose methods from closely related saponin drugs, and AIP bench work is pending.
Australian practitioners use a 1:2 liquid extract at 10 to 30 mL a week for heavy menstrual bleeding, and diluted as a douche for vaginal discharge. That use rests on Eclectic and later practitioner tradition. No clinical trial of beth root has been found. The laboratory evidence is two cytotoxicity screens of retail material and studies of isolated saponins. Beth root has a long history of use to hasten labour, so it is avoided in pregnancy except under supervision. The species is secure across its range as a whole (NatureServe G5; IUCN Least Concern), but it is rare in several US states, wild harvest has pressured it, and United Plant Savers lists it as at risk.
0.3 Contents with extent
| Section | Extent (A4 pages, estimated for this printing) |
|---|---|
| 0 Free-teaser block | 4 |
| 1 Nomenclature | 2 |
| 2 Definition | 1 |
| 3 Source and Australian supply, with 3.1 origin, climate and chemistry | 4 |
| 4 Macroscopy | 4 |
| 5 Microscopy | 3 |
| 6 Chemistry | 2 |
| 7 Named markers and assay limits | 2 |
| 8 TLC fingerprint | 2 |
| 9 HPLC fingerprint | 2 |
| 10 Identity, purity, adulterants and contaminants | 3 |
| 11 Traditional use | 3 |
| 12 Current practice | 2 |
| 13 Clinical evidence | 2 |
| 14 Pharmacology | 2 |
| 15 Safety | 2 |
| 16–18 Discussion, conclusions, research needed | 4 |
| 19 References | 3 |
| 20 Document control | 2 |
| Totals (draft) | 51 A4 pages in this printing. 36 embedded figures: 12 licensed or public-domain photographs of the living plant, flower and fruit; 5 licensed photographs of fresh rhizomes, whole and sectioned; 6 public-domain plates and paintings and 1 licensed herbarium sheet; 1 licensed HPTLC plate and 1 licensed UPLC chromatogram (both of other plants, not beth root); 1 AIP composite of PubChem structures; 9 AIP drawings, charts and replots. About 24 tables. 0 AIP photomicrographs, 0 AIP chromatograms, 0 AIP plates. 0 clinical trials to grade; 1 trial register searched and 2 more attempted; 2 literature databases searched; TGA safety alerts and ARTG checked, DAEN not yet queried. 49 numbered references |
Gaps stated plainly. AIP holds no voucher, photomicrograph, TLC plate or chromatogram of beth root. No licensed photomicrograph of the rhizome was found, so Figure 4 is a licensed macroscopic photograph of a cut fresh rhizome and Figure 5 an AIP schematic drawn from Kraemer’s description. No published TLC or HPLC fingerprint of beth root was found in the sources read; Figures 7 and 8 show published systems run on other plants and are labelled so. The two primary papers that isolated the saponins of beth root (a Japanese study of 2008 and a Queensland study of 2009) are being obtained in full text, and nothing from them is used here beyond what a published review reports. The CITES checklist, the ANZCTR search page, the WHO trials portal and the TGA adverse-event database could not be read or fully queried by our tools in September 2026 and are to be checked by hand.
0.4 Contributors and access
Compiled by Dr Thomas Ridley, Head of Education and Research. The Botanical review of sections 1–5 and 10 by Dr Fiona MacAllister, Head of Botanical, is on record: names, distribution, historical descriptions, library sources and figure credits were re-read against their sources and corrected where needed. The QA review of sections 6–10 by Dr Hana Suzuki, Head of Botanical QA, is on record: every method parameter, CID, limit and regulatory figure was re-read against its source, and the purity and contaminant limits now carry the Ph. Eur. general figures. The Medicine review of sections 12, 13 and 15 by Dr Eleanor Whitcombe, Head of Medicine, is on record: every dose, indication and safety statement was re-read in the library texts, the literature and register searches were re-run, the TGA safety alerts and ARTG were checked, and red flags now lead section 15. The Education and Research evidence and citation audit by Dr Thomas Ridley is on record: every PMID and DOI was resolved, the open papers and library texts were re-read at the locations cited, the figure licences were re-checked, and the conclusions were held to the evidence grading. The Community Outreach review of layout and figures by Jesse Kirby, Head of Community Outreach, is on record: every figure was checked for its place in the section it illustrates, its numbered caption and its source, licence and credit line, and the printed layout was set. Dr Ridley was also the compiler, so a reader from another department is still needed for sections 11, 14 and 16–18. Each reviewer is credited once the review is on record. Dr Luke Iggulden, Chief Scientific Officer, is senior author: he set the scope of the pharmacopoeia series and made the research possible. A preview of the monograph and all of section 15 (Safety) are free to every reader; the full text is for Scholar members and above, or the AUD $20 copy of this one title.
Free to every reader. The safety section of every monograph is open to everyone, signed in or not. In an emergency call 000. For poisoning, call the Poisons Information Centre on 13 11 26.
15. Safety
Red flags first.
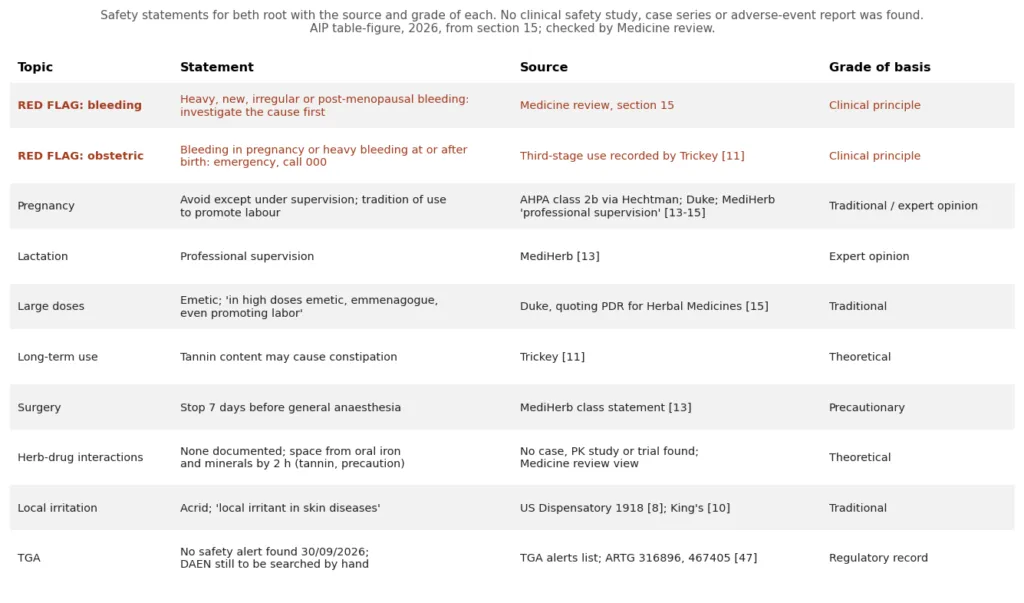
- Heavy bleeding is a symptom, and its cause has to be found. Heavy or irregular bleeding can come from fibroids, polyps, thyroid disease, bleeding disorders, anticoagulant medicines, pregnancy complications or cancer. Anyone with heavy, new or irregular bleeding, or bleeding after menopause, should have it investigated, and should consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy before using beth root.
- Bleeding in pregnancy, or heavy bleeding during or after birth, is an emergency: call 000. Beth root has a practice record in the third stage of labour [11], and no herb replaces emergency obstetric care.
- Bleeding heavy enough to cause dizziness, fainting, breathlessness or soaking a pad or tampon every hour is also an emergency (000).
Evidence base. No clinical safety study, case report, case series or adverse-event report of beth root was found in PubMed or Europe PMC (searches in section 13). TGA checks on 30/09/2026: the current safety alerts list and a search of the TGA website for Trillium and beth root found no alert, recall or safety advisory about beth root; the only TGA records found were the two ARTG listings in section 12 [47]. The TGA Database of Adverse Event Notifications (DAEN) sits behind a terms-of-use page and an interactive report that our tools could not query, so it has not been searched and must be searched by hand (section 18). Every statement below is graded by the kind of evidence behind it.
Adverse effects.
- Gastrointestinal: large doses are emetic. Duke, citing the source he codes PHR: "In high doses emetic, emmenagogue, even promoting labor" [15]; Sayre calls it "emmenagogue and emetic" [16]. Duke notes that his entry is generic across Trillium species [15]. Grade: traditional.
- Constipation with long use: Trickey warns that "the tannin fraction should inspire caution and symptoms such as constipation may indicate adverse effects from tannins on the gut wall" [11]. Grade: theoretical.
- Local irritation: the rhizome is acrid and was used "as a local irritant in skin diseases" [8]; chewing it causes heat in the throat and salivation [8,10]. A review of toxic North American plants lists T. erectum with skin burns from the leaves [25]. Grade: traditional.
- Normal doses: Duke quotes the source he codes PH2: "Hazards and/or side effects not known for proper therapeutic dosages" [15]. Grade: expert opinion.
Toxicology. No acute, repeated-dose, genotoxicity or reproductive toxicity study of beth root was found. The cytotoxicity in section 14 is in cultured cells only.
Contraindications and cautions.
- Pregnancy: avoid except under the supervision of a practitioner trained for it. Hechtman lists "Bethroot, Trillium spp." in her table of herbs contraindicated in pregnancy, taken from Romm (2009), with American Herbal Products Association class 2b and "not categorised" in the Mills and Bone scheme [14]; Duke gives class 2b and says that "as an emmenagogue/uterotonic, should not be used by pregnant mothers" [15]; MediHerb advises professional supervision [13]. The tradition of use to hasten labour, its use in the third stage of labour [11] and the historical record of attempted abortion (section 11) point the same way [10,28,31]. Use in labour is for a practitioner trained in obstetric herbal care, working with the midwife or obstetric team, and never in place of emergency care. Grade: traditional and expert opinion; no study.
- Lactation: professional supervision [13]. Nothing is known about transfer into breast milk. Grade: precautionary expert opinion; no data.
- Surgery: MediHerb’s standard advice to stop 7 days before general anaesthesia [13]. Grade: precautionary class statement, not specific to this herb.
Herb–drug interactions. None documented. No case report, pharmacokinetic study or trial of an interaction with beth root was found. MediHerb refers readers to its own interaction chart, which was not among the sources read [13]. AIP comment (Medicine review): tannin-rich drugs can in theory reduce the absorption of drugs and minerals, including iron, taken at the same time. A woman with heavy bleeding is often taking oral iron, so beth root and iron or other mineral supplements are best taken at least two hours apart. This is a precaution drawn from the tannin content; no study of beth root supports or refutes it. Grade: theoretical. The listed capsules in section 12 also contain chaste tree and black cohosh, whose own cautions apply to those products.
Children and older people. No data. The current indications concern menstruating women.
Overdose. Vomiting is the expected effect (see above). No overdose case was found.
Regulatory safety actions. None found for beth root. It is not scheduled in the Poisons Standard [3] and is permitted as an active ingredient in listed medicines with no specific requirements [2]. No TGA safety alert about it was found on 30/09/2026, and neither ARTG public summary carries a warning that concerns beth root [47].
29 more pages follow · 14,256 words, 33 figures, 13 tables
Still to come in this monograph
- 1. Nomenclature
- 2. Definition
- 3. Source and Australian supply
- 4. Macroscopy
- 5. Microscopy
- 6. Chemistry
- 7. Named markers and assay limits
- 8. TLC fingerprint
- 9. HPLC fingerprint
- 10. Identity, purity, adulterants and contaminants
- 11. Traditional use
- 12. Current practice: use, preparations and doses
- 13. Clinical evidence
- 14. Pharmacology
- 16. Discussion
- 17. Conclusions
- 18. Research still needed
- 19. References
- 20. Document control
The rest of this monograph is open to members. One membership covers every members’ feature on the site.
Checking your membership…
Report an error or submit evidence
If something in this monograph is wrong, out of date or missing, tell us and show us the evidence. Every report is logged under the AIP Evidence Charter and assessed on the evidence alone; the outcome is kept on the record, and an upheld report is corrected with a dated notice on this page.
Open the report form
The Institute sets and publishes its own monographs. The catalogue is in Publications.


