


Licorice root (Glycyrrhiza glabra L.), Fabaceae
Australian Herbal Pharmacopoeia (working title), Monograph AIP-PH-GLYGLA (formerly AIP-HP 009)
Status: version 1.0 draft. Working draft, published while in build. Technical reviews by Botanical, QA and Medicine are on record; History and Philosophy (section 11), the Librarian reference audit and the Legal read are still to come.
Date: 2026. Next review: on sign-off, then three-yearly or sooner if a major trial, a safety signal or a new pharmacopoeial text appears.
Prepared by: the Australian Institute of Pharmacognosy, Far North Queensland, Australia. Every author and contributor is named at the end of the monograph.
Contributors: Dr Thomas Ridley (library and literature search, full-text retrieval, registry and regulatory-instrument search, synthesis, drafting, figure sourcing and placement, AIP schematics and charts, reference verification). Technical review requested of Dr Fiona MacAllister (Botanical, sections 1-5 and 10), Dr Hana Suzuki (QA, sections 6-10) and Dr Eleanor Whitcombe (Medicine, sections 12, 13, 15). Dr Luke Iggulden, Chief Scientific Officer, is senior author: he set the scope of the series in the CEO directive and made the research possible.
0. Free teaser
0.1 Identity card
| Monograph | AIP-PH-GLYGLA (formerly AIP-HP 009), Licorice root. Version 1.0 draft, 2026. Next review: on sign-off |
| Accepted name | Glycyrrhiza glabra L., Leguminosae (Fabaceae Lindl., APG IV), order Fabales. Protologue: Linnaeus, Species Plantarum 2: 742 (1 May 1753); IPNI 496941-1, flag inPowo: true [2]. Accepted in the World Checklist of Vascular Plants, read in September 2026 through ChecklistBank dataset 2000; WCVP native-range note "C. Medit. to Mongolia and Pakistan" [1] |
| Synonyms | Heterotypic (WCVP, 23/09/2026): Liquiritia officinalis Moench; Liquiritia officinarum Medik.; Glycyrrhiza glandulifera Waldst. & Kit.; G. violacea Boiss.; G. hirsuta L.; G. laevis Pall.; G. officinalis Lepech.; G. pallida Boiss. & Noë; G. echinata Lepech. (not G. echinata L., which is a separate accepted species); and the trade "varieties" var. glandulifera and var. violacea, both sunk into the species; "var. typica" is not a published name at all and has no record in IPNI [1,2] |
| Drug name | Liquiritiae radix. The article of commerce is the dried, unpeeled or peeled, whole or cut root and stolons of G. glabra and/or G. inflata Batalin and/or G. uralensis Fisch. ex DC. The Ph. Eur. label must state whether the drug is peeled or unpeeled [3] |
| Common names | Licorice, liquorice, sweet root, sweetwood (English); Süssholzwurzel, Lakritzenwurzel (German); réglisse, bois doux (French); liquirizia (Italian); regaliz (Spanish); yashtimadhu, jethimadh, madhuyashti (Sanskrit and Indian vernaculars); gancao (Chinese, usually G. uralensis); kanzo (Japanese); irksos, ud al sus (Arabic) [7,9,10] |
| Pharmacopoeial status | Ph. Eur.: yes, Liquorice root 01/2012:0277, plus Liquorice dry extract for flavouring purposes 01/2012:2378 and Liquorice ethanolic liquid extract, standardised 01/2012:1536 [3,4,5,8]. BP: yes (the BP adopts the Ph. Eur. monograph) [10,12]. WHO: yes, Radix Glycyrrhizae, WHO monographs vol. 1, pp. 183-94, library copy [9]. EMA/HMPC: yes, EU herbal monograph EMA/HMPC/108399/2024, final revision 1, adopted 04/03/2026, traditional use only [7]. USP-NF: yes, as recorded by Mills and Bone at USP 34-NF 29 [10]. Chinese Pharmacopoeia and Japanese Pharmacopoeia: yes, for G. uralensis and allied species [9]. BHP 1996: yes (BHP 1983 entry cited by Mills and Bone; AIP does not hold either edition) [10] |
| Australian status | Poisons Standard: not scheduled. Glycyrrhiza glabra and liquorice appear nowhere in the Schedules of the Therapeutic Goods (Poisons Standard, June 2026) Instrument 2026; the only entry is "LIQUORICE, DEGLYCYRRHISINISED", Appendix B clause 3 (substances considered not to require control by scheduling), area of use 7.1 "any use", reason (a) "low toxicity", included May 1999 [14]. Permissible Ingredients Determination: item 2418 GLYCYRRHIZA GLABRA, purposes A, E, H (active, excipient, homoeopathic), column 4 blank: no dose ceiling, no warning statement, no specific requirement; also item 2420 G. uralensis, item 2419 Glycyrrhiza species (flavour only), item 2421 glycyrrhizinic acid (excipient), items 3066-3069 LIQUORICE, LIQUORICE DRY, LIQUORICE LIQUID EXTRACT and LIQUORICE POWDER [13]. ARTG: 243 entries returned for "Glycyrrhiza glabra" on 23/09/2026, including MediHerb Licorice High Grade Liquid (347191, Integria Healthcare Australia Pty Ltd) [15,16]. Not native; not a declared weed in Queensland; 103 Atlas of Living Australia records, none from Queensland [17] |
| Assay marker | 18β-Glycyrrhizic acid (glycyrrhizin, PubChem CID 14982; C42H62O16, Mr 823). Ph. Eur. limit: minimum 4.0 per cent, calculated with reference to the dried drug, by liquid chromatography against monoammonium glycyrrhizate CRS (CID 62074) at 254 nm [3]. WHO sets the same 4 per cent minimum [9] |
| Identity markers | 18β-Glycyrrhetinic acid (CID 10114), the TLC identity zone after hydrolysis, and isoliquiritigenin (CID 638278), the yellow upper-third zone [3]. Species markers (not pharmacopoeial): glabridin (CID 124052) for G. glabra, licochalcone A (CID 5318998) for G. inflata, glycycoumarin (CID 5317756) for G. uralensis [56] |
| Purity limits | Loss on drying maximum 10.0 per cent; total ash maximum 10.0 per cent unpeeled / 6.0 per cent peeled; ash insoluble in hydrochloric acid maximum 2.0 per cent unpeeled / 0.5 per cent peeled; ochratoxin A maximum 20 µg/kg (Ph. Eur. 2.8.22) [3,6] |
| Evidence snapshot | Blood-pressure rise and potassium fall from regular intake: Tier A, the best-supported human effect of this drug is an adverse one. 18 studies, n = 337, pooled systolic +5.45 mm Hg (95% CI 3.51 to 7.39), plasma potassium −0.33 mmol/L [38]; confirmed in 8 RCTs, n = 541 [39], and reproduced in a randomised crossover trial at only 100 mg glycyrrhizic acid a day [40]. Post-operative sore throat, topical gargle: Tier B — 5 RCTs, n = 574, relative risk 0.44 (95% CI 0.28 to 0.69), number needed to treat 4, with a sensitivity analysis that overturns the result [25]. Functional dyspepsia, deglycyrrhizinated acetone extract 75 mg twice daily: Tier B, one RCT, n = 50 [18]. H. pylori gastric load and eradication, as add-on: Tier B — 2 small RCTs, n = 227 [19,20]. Recurrent aphthous stomatitis, topical: Tier B — 6 small trials [8]. Peptic-ulcer healing with deglycyrrhizinated licorice: Tier C and conflicting [8,31,32,33]. Menopausal hot flushes, PCOS, oral mucositis, COVID-19: Tier C. Cough, bronchial catarrh, adrenal support: Tier T, traditional only. Antiviral, hepatoprotective, antitumour: Tier P, preclinical only |
| Main safety point | Glycyrrhizin is hydrolysed by gut bacteria to 18β-glycyrrhetinic acid, which inhibits renal 11β-hydroxysteroid dehydrogenase type 2 and lets cortisol act at the mineralocorticoid receptor. The result is apparent mineralocorticoid excess: sodium and water retention, potassium loss, suppressed renin and aldosterone, raised blood pressure, and at the extreme hypokalaemic myopathy, rhabdomyolysis, arrhythmia and hypertensive encephalopathy [8,10,11,38]. The European Scientific Committee on Food set an upper limit for regular intake at 100 mg glycyrrhizin a day and said even that will not protect everyone [8]; a 2024 randomised crossover trial found a measurable blood-pressure rise at exactly that dose [40]. Every routine therapeutic dose of whole root in the practitioner literature exceeds it. Liquorice is contraindicated in pregnancy, in hypertension, in hypokalaemia, in cholestatic liver disease and cirrhosis, and in severe renal insufficiency [7,9,10,11]. Anyone considering licorice should consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy |
| Suggested citation | Ridley T, Iggulden L. Liquiritiae radix (licorice root, Glycyrrhiza glabra L.). Australian Herbal Pharmacopoeia monograph AIP-PH-GLYGLA (draft v1.0). Cardwell (QLD): Australian Institute of Pharmacognosy; 2026. DOI to be assigned |
| Compiler and review | Compiled by Dr Thomas Ridley (Education and Research). Technical review: Dr Fiona MacAllister (Botanical, sections 1-5 and the adulterant part of 10) reviewed in 2026; Dr Hana Suzuki (Botanical QA, sections 6-10) reviewed in 2026; Dr Eleanor Whitcombe (Medicine, sections 12, 13, 15) reviewed in 2026; Dr Thomas Ridley (Education and Research, evidence and citation audit, reviewed in 2026: sections 1-3 and 3.1, the sources behind 6-9, 11, the sources behind 12 and 15, 13, 14, 16-18 and the reference audit at 19, together with the source and licence of every figure. Every PMID, DOI, PubChem CID and trial-registry record in the document was resolved live and checked against the sentence it supports. Under Evidence Charter rule 7 this is the compiler’s own check of his own draft and is not an independent review; an audit by a second department stays open at 20.5); Jesse Kirby (Community Outreach, free-teaser and whole-document layout: figure placement, caption numbering, source and licence credit lines, free-sample cut and page design) reviewed in 2026. Published: not yet. Last modified: 2026. Version 1.0 draft |
| Provenance | Original AIP data: none. No bench, field or clinic data of AIP’s own appears anywhere in this monograph. Every limit, method, measurement, assay figure and trial result comes from the cited pharmacopoeias, regulators, reference works and papers; sections 4, 5, 7, 8, 9 and 10 are marked "AIP bench data pending". AIP’s own primary records here are of two kinds only, and neither is data about the drug: the dated literature, registry, regulatory and image searches recorded in sections 3, 5, 13 and 15, and the AIP-drawn map, charts and schematics, each captioned with what it was drawn from |
| Canonical URL | /pharmacopoeia/glycyrrhiza-glabra/ (on publication) |

0.2 Summary
Licorice is the dried root and stolons of Glycyrrhiza glabra, a leguminous perennial of the belt running from the central Mediterranean through western and central Asia to Mongolia and Pakistan. The European Pharmacopoeia admits two further species to the same drug name, G. inflata and G. uralensis, and requires at least 4.0 per cent 18β-glycyrrhizic acid on the dried drug. Glycyrrhizin gives the root its sweetness, about fifty times that of sucrose, and also gives it its characteristic toxicity, because its gut metabolite blocks the enzyme that protects the mineralocorticoid receptor from cortisol. Identity rests on a yellow, fibrous, splintery root with a distinct cambium ring, on a powder of long thick-walled fibres in crystal sheaths with prismatic calcium oxalate and simple round starch, and on a TLC and HPLC profile keyed to glycyrrhetinic acid and glycyrrhizic acid. The clinical evidence is thinner than the reputation and points in an awkward direction: the strongest and most consistent human finding about licorice is that regular intake raises blood pressure and lowers plasma potassium, at doses well inside ordinary practitioner prescribing. Efficacy evidence exists for a topical gargle in post-operative sore throat, for a deglycyrrhizinated extract in functional dyspepsia, and for licorice added to Helicobacter pylori regimens, all of it low-certainty. In Australia the drug is not scheduled and carries no dose ceiling in the Permissible Ingredients Determination, which places the whole burden of safe dosing on the prescriber. Anyone considering licorice should consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy.
0.3 Contents and extent (draft)
| Section | Approx. pages |
|---|---|
| 1-3 Nomenclature, definition, source and Australian supply (1 map, 1 historical plate, 2 photographs, 1 chart) | 6 |
| 3.1 Origin, climate and chemistry: where it must be grown (1 chart, 3 tables) | 4 |
| 4-5 Macroscopy and microscopy (4 photographs, 1 labelled schematic, 1 pending slot) | 5 |
| 6-7 Chemistry, markers and limits (14 structures, 4 tables) | 6 |
| 8-9 TLC and HPLC fingerprints (2 AIP schematics, 1 licensed published chromatogram) | 4 |
| 10 Identity, purity, adulterants, contaminants (3 tables) | 4 |
| 11 Traditional use | 2 |
| 12 Current practice and doses (1 chart, 2 tables) | 3 |
| 13 Clinical evidence (search, graded trials, registries, 1 evidence chart) | 7 |
| 14 Pharmacology and pharmacokinetics | 3 |
| 15 Safety, interactions, pregnancy (1 forest chart, 5 tables) | 6 |
| 16-18 Discussion, conclusions, research needed | 4 |
| 19-20 References and document control | 5 |
| Totals (draft) | 54 A4 pages in the laid-out PDF, of which the first 5 are the free sample; 25 tables; 32 embedded figures (7 licensed or public-domain photographs, 1 public-domain botanical plate, 14 PubChem structures, 1 AIP microscopy schematic, 2 AIP chromatography schematics drawn from the Ph. Eur. method text, 1 licensed CC BY published HPLC fingerprint, 1 AIP map, 5 AIP data charts), each placed in the section it illustrates. Photomicrographs: none. AIP bench data pending. A search of Wikimedia Commons and of Europe PMC open-access literature in September 2026 found no openly licensed photomicrograph of G. glabra root transverse section or powder, so figure slot F4 stays open and is shown as a captioned placeholder in section 5. Chromatograms: none measured by AIP; the section 8 and section 9 figures are AIP schematics drawn from the published Ph. Eur. method and are labelled as such. Trials graded: 25 human studies graded individually and 5 syntheses in section 13.2, 8 harms studies in 13.3, 23 registry records retrieved. 83 numbered references. Every one of the 61 PMIDs and 58 DOIs in the list was resolved live at NCBI and Crossref in September 2026 and checked against what the text says (section 19). |
0.4 Contributors and access
Prepared by the Australian Institute of Pharmacognosy. Botanical, QA and Medicine reviews are on record; who covers what is set out in 0.1 and 20.3. History and Philosophy (section 11), the Librarian reference audit and the Legal read are outstanding. A Legal read is advisory and does not gate publication (CEO order 22/09/2026, as amended 17/09/2026). The Australian Herbal Pharmacopoeia is AIP’s own series and carries no statutory, TGA or government standing. Access to the full monograph beyond the free sample follows the membership rules set by the CEO.
Free to every reader. The safety section of every monograph is open to everyone, signed in or not. In an emergency call 000. For poisoning, call the Poisons Information Centre on 13 11 26.
15. Safety
15.1 The dose-response for harm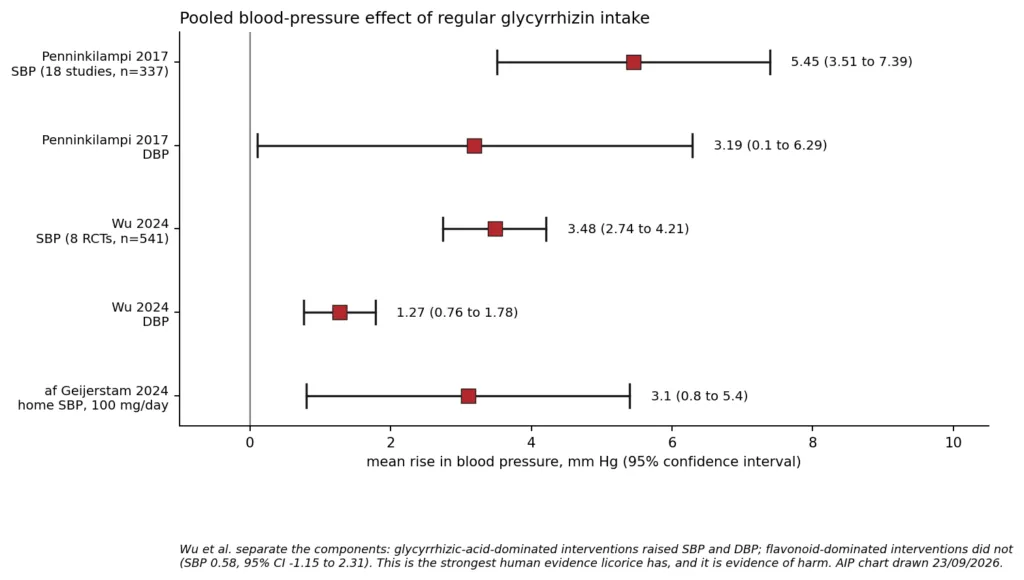
| Daily glycyrrhizin | What happens | Source |
|---|---|---|
| About 2 mg/kg | Proposed no-effect level in a study of 39 women (about 140 mg for a 70 kg adult) | van Gelderen et al. [42] |
| 12 mg (0.2 mg/kg for a 60 kg adult) | Acceptable daily intake proposed by the authors of the Dutch dose-ranging study, from their own 2 mg/kg no-effect level with a safety factor of 10. It is the lowest figure any group has put forward, and it is an order of magnitude below the SCF ceiling | van Gelderen et al. [42] |
| 10 mg | A safe dose for most healthy adults, derived by applying a safety factor of 10 to the 100 mg lowest-observed-adverse-effect level. Mills and Bone call this "a very conservative estimate" | Størmer et al., as reported by Mills and Bone [10,43] |
| 100 mg | SCF 2003 upper limit for regular ingestion — and the dose at which a 2024 randomised crossover trial found home systolic BP rising by 3.1 mm Hg with renin down 30 per cent and aldosterone down 45 per cent. JECFA reached the same 100 mg figure in 2005 | SCF via EMA AR; af Geijerstam et al. [8,40] |
| 100-400 mg | The range in which Braun and Cohen place most licorice adverse effects | Braun and Cohen [11] |
| 150 mg | 100 g/day confectionery for 4 weeks: office systolic +3.5 mm Hg in normotensives, +15.3 mm Hg in hypertensives | Sigurjonsdottir et al. [41] |
| 290-370 mg | Two weeks: increased extracellular volume, amplified pressure-wave reflection, elevated central systolic and diastolic pressure | EMA AR, citing Leskinen 2014 and Hautaniemi 2017 [8] |
| 400 mg | "Most individuals" experience adverse effects | Størmer et al. via Mills and Bone [10,43] |
| 500 mg (7 g of a commercial preparation, 7 days) | Pseudoaldosteronism: weight gain, suppressed renin and aldosterone, reduced serum potassium. In the same dose range, serum testosterone fell by about 35 per cent in seven men after 4 days | Mills and Bone; Armanini et al. [10,49] |
| 700-1,400 mg (100-200 g liquorice/day, 1-4 weeks) | Plasma potassium fell by more than 0.3 mmol/L in 11 of 14 volunteers, four withdrawn for hypokalaemia; renin-angiotensin-aldosterone suppression in all. Urinary cortisol stayed elevated for at least a week after withdrawal | EMA AR, citing Epstein 1977 and 1978 [8] |
| Chronic, 25-200 g liquorice/day for 6 months to 5 years | Renin-angiotensin-aldosterone suppressed for several months after stopping | EMA AR, citing Epstein 1977 [8] |
15.2 Adverse effects
From trials. The meta-analytic findings at 13.3 are themselves the adverse-effect data: systolic +5.45 mm Hg, diastolic +3.19, potassium −0.33 mmol/L, renin and aldosterone suppressed [38,39,40].
From case reports and series (each with the causality judgement stated):
| Effect | Evidence | Causality |
|---|---|---|
| Apparent mineralocorticoid excess / pseudohyperaldosteronism: sodium and fluid retention, oedema, hypertension, hypokalaemia, breathlessness | Multiple case series and controlled studies | Established, dose-related, mechanism understood [8,10,11,38] |
| Hypokalaemia presenting as hypotonia, flaccid paralysis, peripheral oedema, polyuria, proximal myopathy, lethargy, paraesthesiae, cramps, headache, tetany | Case reports | Probable to established [11] |
| Hypokalaemic arrhythmia, including a case of recurrent torsade de pointes | Rare case reports | Probable [11] |
| Hypokalaemic periodic paralysis | Case reports | Probable [11] |
| Rhabdomyolysis, with acute renal failure and calcium deposition in skeletal and cardiac muscle | Several case reports | Probable [10,11] |
| Hypertensive encephalopathy, at intakes around 100 mg glycyrrhizin/day in susceptible people | Case reports | Probable; may occur at low dose in 11β-HSD2 deficiency [10,11] |
| Transient visual loss (monocular or binocular), attributed to retinal or occipital vasospasm, after 110-900 g of confectionery | Case series of five | Possible [10,11] |
| Thrombocytopenia with hypokalaemia and oedema, resolving on cessation | Single case report | Possible [11] |
| Dropped head syndrome from licorice-induced hypokalaemia | Single case report | Possible [11] |
| Carpal tunnel syndrome following licorice-induced fluid retention | Single case report | Possible [11] |
| Reduced serum testosterone in men, about 35 per cent at 500 mg glycyrrhizin/day | One small study; two replication attempts failed, finding only a non-significant decrease; a later Iranian study at 400-500 mg/day again found about 35 per cent | Conflicting. Braun and Cohen call the evidence inconsistent [10,11,49,50] |
| Contact dermatitis to licorice-containing topicals, patch-test confirmed | Case reports | Probable [11] |
| Reversible growth retardation in a child with Addison’s disease consuming 300-400 g confectionery/day | Single case report | Probable [10] |
TGA safety alerts, recalls and DAEN. Medicine attempted all three Australian sources in September 2026 and reports honestly what each returned.
- TGA safety alerts. No safety alert, product alert or hazard communication for Glycyrrhiza glabra, licorice or glycyrrhizin was located. The TGA website’s own search sits behind a bot-challenge interstitial that refuses automated requests, so the finding rests on an external index of tga.gov.au rather than on the site search, and it is a negative finding of the weakest kind: no alert was found; that is not the same as confirming none exists.
- Database of Recalls, Product Alerts and Product Corrections (DRAC). Searched for licorice, liquorice and glycyrrhiza in September 2026. The database’s search only accepts a product or ingredient chosen from its own suggestion widget, which does not respond to an automated request, so no result set was obtained. DRAC covers actions from 01/07/2012 onward.
- Database of Adverse Event Notifications (DAEN). The medicines search is a Microsoft Power Pages application that will not return a result set outside an interactive browser session, and no downloadable DAEN dataset exists on data.gov.au. DAEN was therefore not searched successfully, and the gap stays open at 20.5. A manual browser search is a ten-minute job for whoever next has the draft in front of them, and it must be done before release.
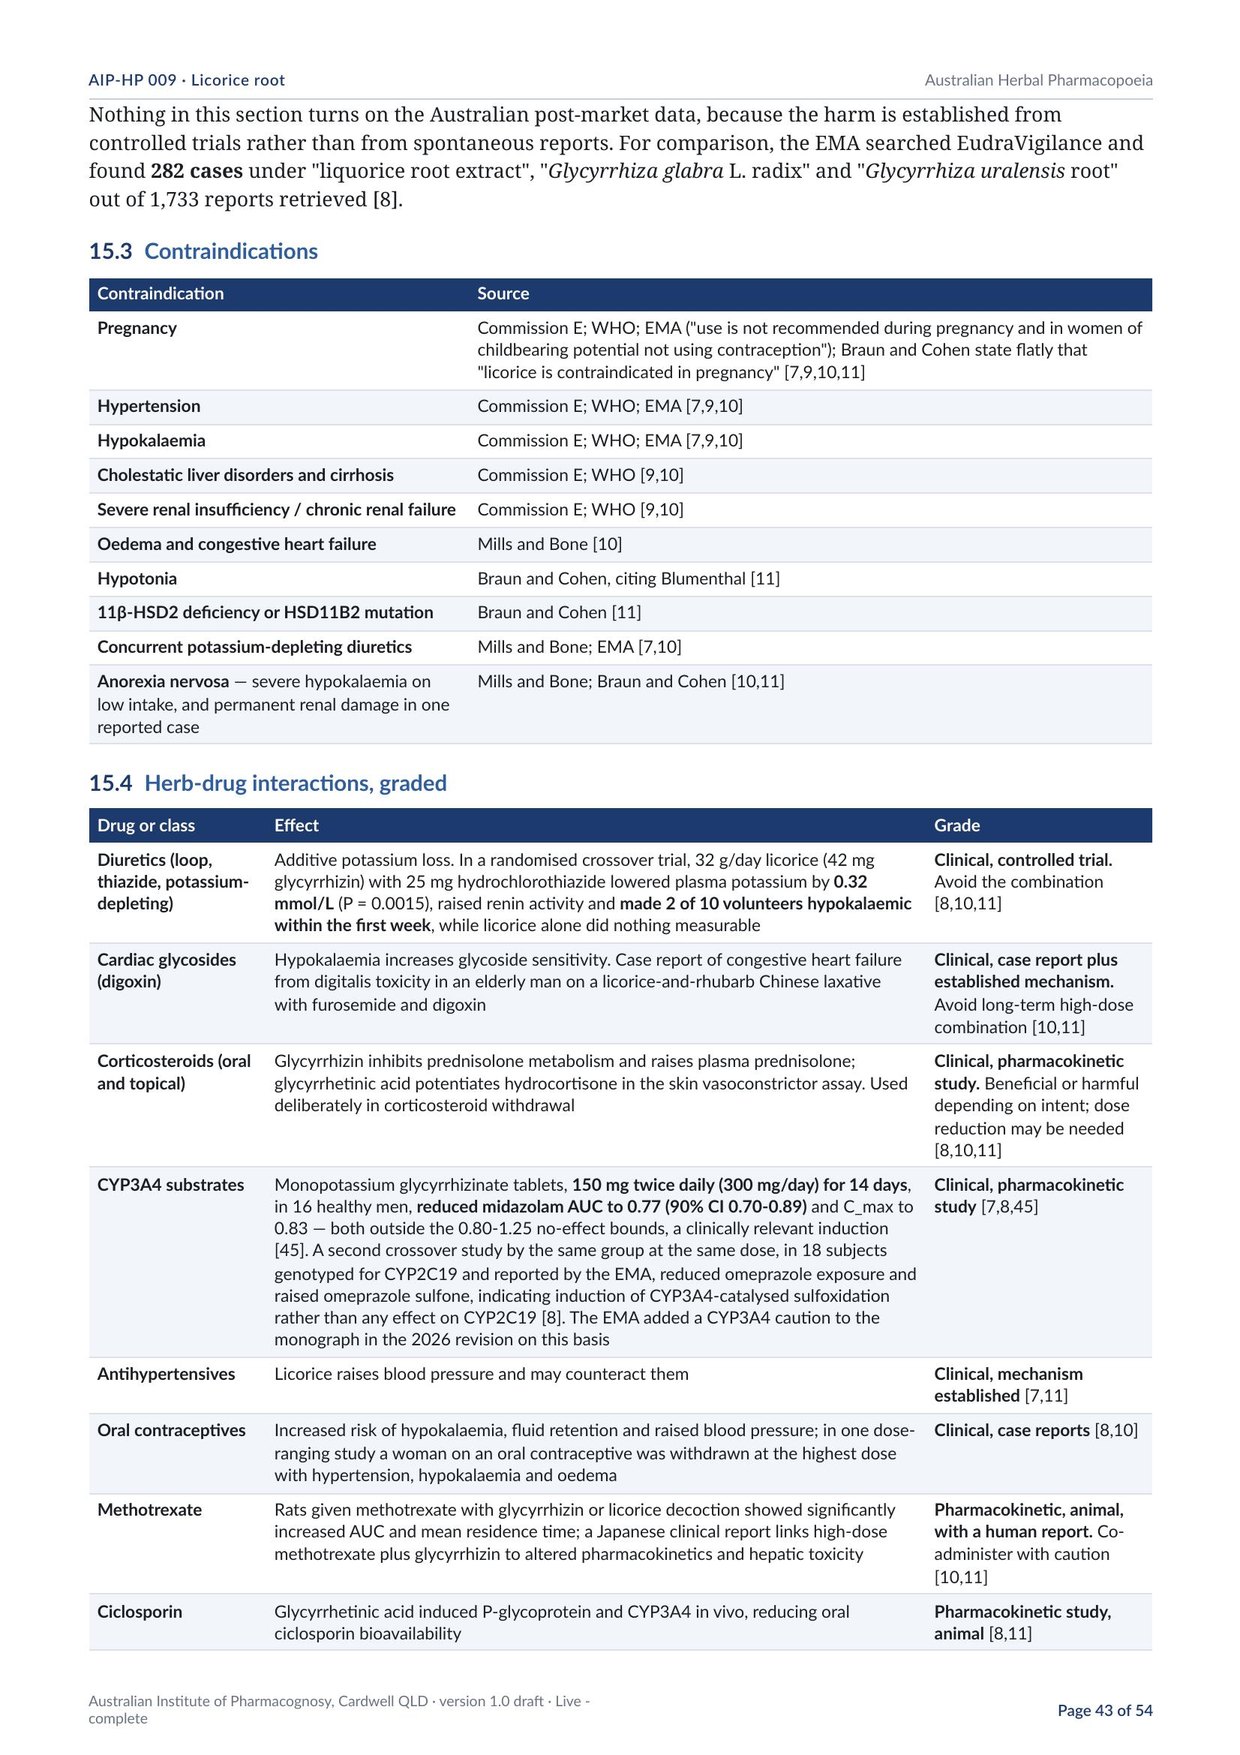
Nothing in this section turns on the Australian post-market data, because the harm is established from controlled trials rather than from spontaneous reports. For comparison, the EMA searched EudraVigilance and found 282 cases under "liquorice root extract", "Glycyrrhiza glabra L. radix" and "Glycyrrhiza uralensis root" out of 1,733 reports retrieved [8].
15.3 Contraindications
| Contraindication | Source |
|---|---|
| Pregnancy | Commission E; WHO; EMA ("use is not recommended during pregnancy and in women of childbearing potential not using contraception"); Braun and Cohen state flatly that "licorice is contraindicated in pregnancy" [7,9,10,11] |
| Hypertension | Commission E; WHO; EMA [7,9,10] |
| Hypokalaemia | Commission E; WHO; EMA [7,9,10] |
| Cholestatic liver disorders and cirrhosis | Commission E; WHO [9,10] |
| Severe renal insufficiency / chronic renal failure | Commission E; WHO [9,10] |
| Oedema and congestive heart failure | Mills and Bone [10] |
| Hypotonia | Braun and Cohen, citing Blumenthal [11] |
| 11β-HSD2 deficiency or HSD11B2 mutation | Braun and Cohen [11] |
| Concurrent potassium-depleting diuretics | Mills and Bone; EMA [7,10] |
| Anorexia nervosa — severe hypokalaemia on low intake, and permanent renal damage in one reported case | Mills and Bone; Braun and Cohen [10,11] |
15.4 Herb-drug interactions, graded
| Drug or class | Effect | Grade |
|---|---|---|
| Diuretics (loop, thiazide, potassium-depleting) | Additive potassium loss. In a randomised crossover trial, 32 g/day licorice (42 mg glycyrrhizin) with 25 mg hydrochlorothiazide lowered plasma potassium by 0.32 mmol/L (P = 0.0015), raised renin activity and made 2 of 10 volunteers hypokalaemic within the first week, while licorice alone did nothing measurable | Clinical, controlled trial. Avoid the combination [8,10,11] |
| Cardiac glycosides (digoxin) | Hypokalaemia increases glycoside sensitivity. Case report of congestive heart failure from digitalis toxicity in an elderly man on a licorice-and-rhubarb Chinese laxative with furosemide and digoxin | Clinical, case report plus established mechanism. Avoid long-term high-dose combination [10,11] |
| Corticosteroids (oral and topical) | Glycyrrhizin inhibits prednisolone metabolism and raises plasma prednisolone; glycyrrhetinic acid potentiates hydrocortisone in the skin vasoconstrictor assay. Used deliberately in corticosteroid withdrawal | Clinical, pharmacokinetic study. Beneficial or harmful depending on intent; dose reduction may be needed [8,10,11] |
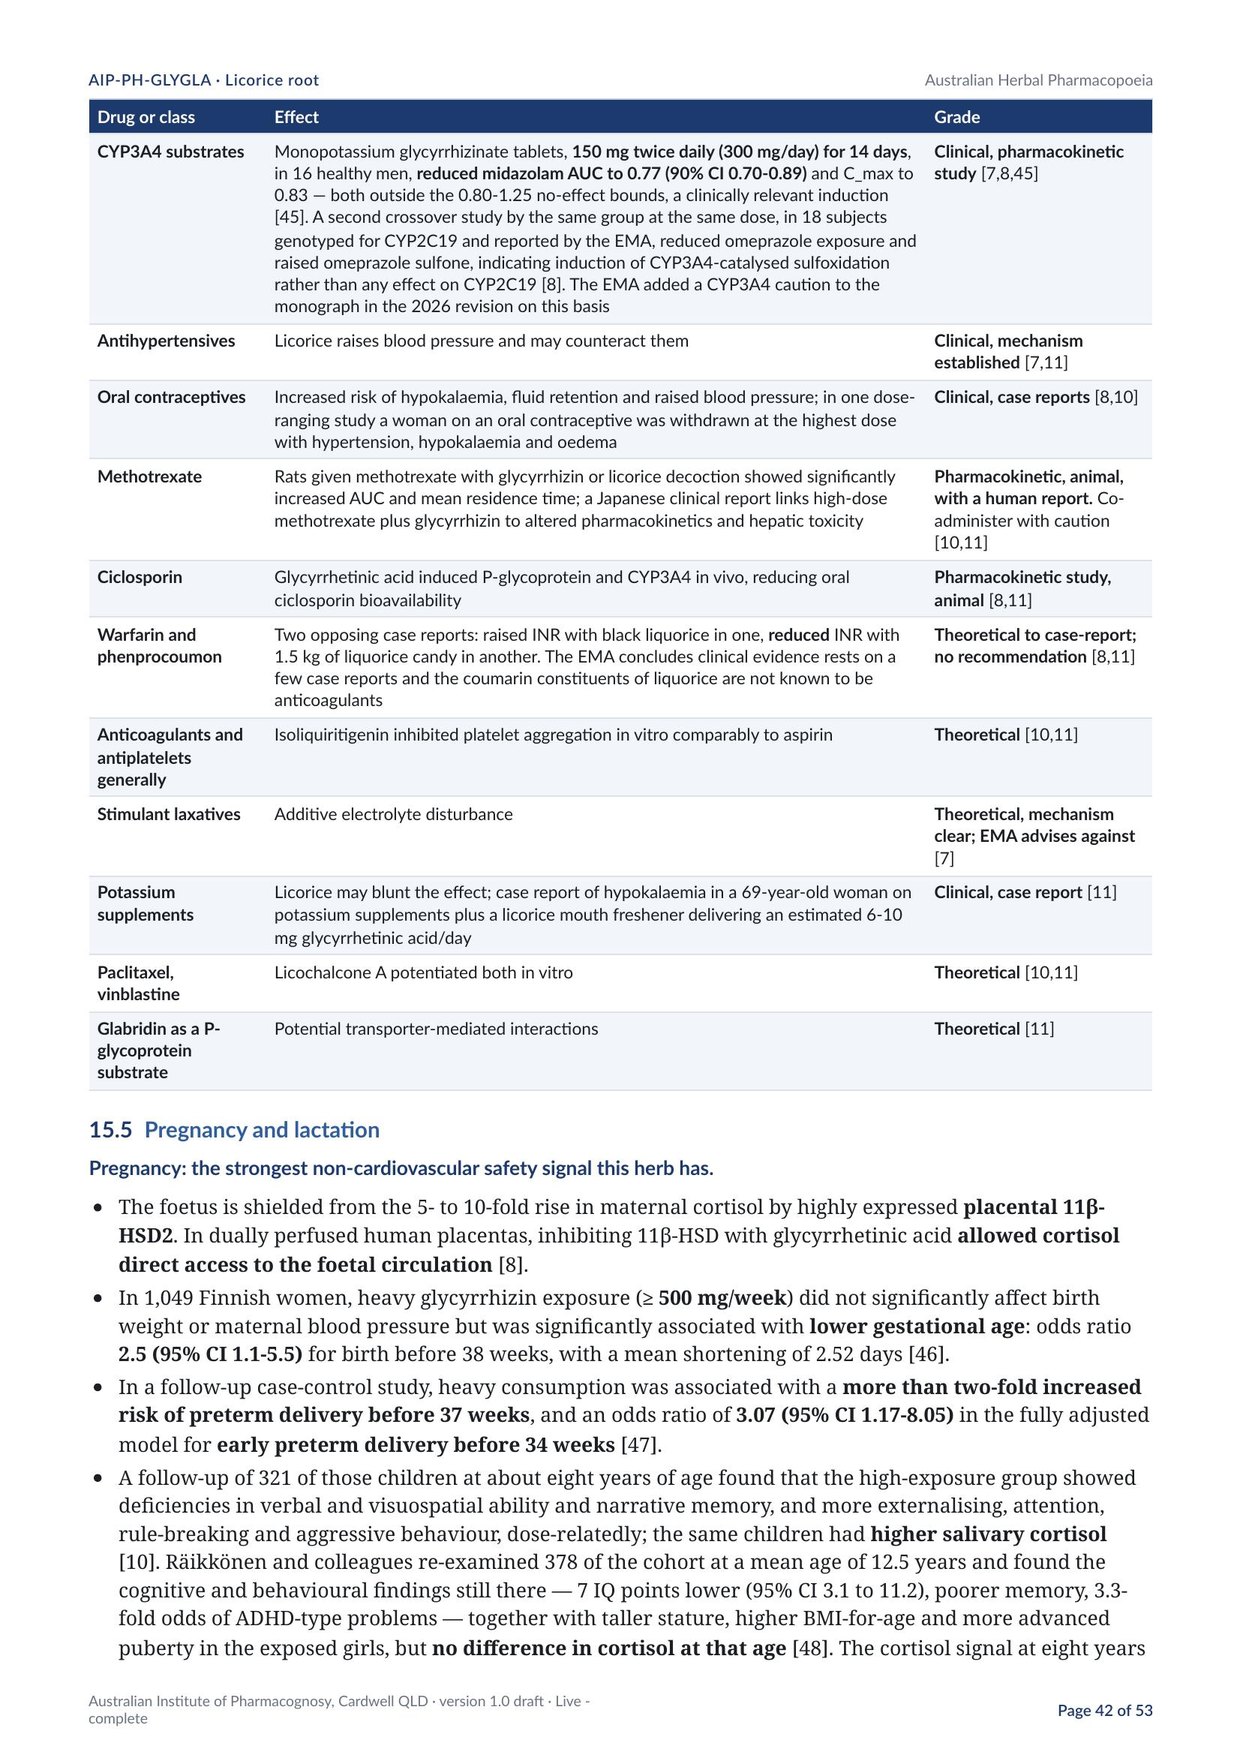
| CYP3A4 substrates | Monopotassium glycyrrhizinate tablets, 150 mg twice daily (300 mg/day) for 14 days, in 16 healthy men, reduced midazolam AUC to 0.77 (90% CI 0.70-0.89) and C_max to 0.83 — both outside the 0.80-1.25 no-effect bounds, a clinically relevant induction [45]. A second crossover study by the same group at the same dose, in 18 subjects genotyped for CYP2C19 and reported by the EMA, reduced omeprazole exposure and raised omeprazole sulfone, indicating induction of CYP3A4-catalysed sulfoxidation rather than any effect on CYP2C19 [8]. The EMA added a CYP3A4 caution to the monograph in the 2026 revision on this basis | Clinical, pharmacokinetic study [7,8,45] |
| Antihypertensives | Licorice raises blood pressure and may counteract them | Clinical, mechanism established [7,11] |
| Oral contraceptives | Increased risk of hypokalaemia, fluid retention and raised blood pressure; in one dose-ranging study a woman on an oral contraceptive was withdrawn at the highest dose with hypertension, hypokalaemia and oedema | Clinical, case reports [8,10] |
| Methotrexate | Rats given methotrexate with glycyrrhizin or licorice decoction showed significantly increased AUC and mean residence time; a Japanese clinical report links high-dose methotrexate plus glycyrrhizin to altered pharmacokinetics and hepatic toxicity | Pharmacokinetic, animal, with a human report. Co-administer with caution [10,11] |
| Ciclosporin | Glycyrrhetinic acid induced P-glycoprotein and CYP3A4 in vivo, reducing oral ciclosporin bioavailability | Pharmacokinetic study, animal [8,11] |
| Warfarin and phenprocoumon | Two opposing case reports: raised INR with black liquorice in one, reduced INR with 1.5 kg of liquorice candy in another. The EMA concludes clinical evidence rests on a few case reports and the coumarin constituents of liquorice are not known to be anticoagulants | Theoretical to case-report; no recommendation [8,11] |
| Anticoagulants and antiplatelets generally | Isoliquiritigenin inhibited platelet aggregation in vitro comparably to aspirin | Theoretical [10,11] |
| Stimulant laxatives | Additive electrolyte disturbance | Theoretical, mechanism clear; EMA advises against [7] |
| Potassium supplements | Licorice may blunt the effect; case report of hypokalaemia in a 69-year-old woman on potassium supplements plus a licorice mouth freshener delivering an estimated 6-10 mg glycyrrhetinic acid/day | Clinical, case report [11] |
| Paclitaxel, vinblastine | Licochalcone A potentiated both in vitro | Theoretical [10,11] |
| Glabridin as a P-glycoprotein substrate | Potential transporter-mediated interactions | Theoretical [11] |
15.5 Pregnancy and lactation
Pregnancy: the strongest non-cardiovascular safety signal this herb has.
- The foetus is shielded from the 5- to 10-fold rise in maternal cortisol by highly expressed placental 11β-HSD2. In dually perfused human placentas, inhibiting 11β-HSD with glycyrrhetinic acid allowed cortisol direct access to the foetal circulation [8].
- In 1,049 Finnish women, heavy glycyrrhizin exposure (≥ 500 mg/week) did not significantly affect birth weight or maternal blood pressure but was significantly associated with lower gestational age: odds ratio 2.5 (95% CI 1.1-5.5) for birth before 38 weeks, with a mean shortening of 2.52 days [46].
- In a follow-up case-control study, heavy consumption was associated with a more than two-fold increased risk of preterm delivery before 37 weeks, and an odds ratio of 3.07 (95% CI 1.17-8.05) in the fully adjusted model for early preterm delivery before 34 weeks [47].
- A follow-up of 321 of those children at about eight years of age found that the high-exposure group showed deficiencies in verbal and visuospatial ability and narrative memory, and more externalising, attention, rule-breaking and aggressive behaviour, dose-relatedly; the same children had higher salivary cortisol [10]. Räikkönen and colleagues re-examined 378 of the cohort at a mean age of 12.5 years and found the cognitive and behavioural findings still there — 7 IQ points lower (95% CI 3.1 to 11.2), poorer memory, 3.3-fold odds of ADHD-type problems — together with taller stature, higher BMI-for-age and more advanced puberty in the exposed girls, but no difference in cortisol at that age [48]. The cortisol signal at eight years and its absence at twelve are both reported here as the two follow-ups found them; they are not reconciled, and the endocrine mechanism in the child is unsettled.
- The EMA’s position, adopted 04/03/2026: "The use is not recommended during pregnancy and in women of childbearing potential not using contraception." Animal studies show reproductive toxicity: 18β-glycyrrhetinic acid crosses the rat placenta, and glycyrrhizin at 239-1,000 mg/kg from day 7 of pregnancy was minorly embryotoxic to rat foetus kidney and lung [7].
- Mills and Bone assign Category C (has caused, or may be suspected of causing, harmful effects on the foetus or neonate without causing malformations) and add that doses up to 3 g/day of root are likely to be safe for short periods [10]. Medicine’s ruling, 23/09/2026 (Dr Eleanor Whitcombe, Head of Medicine): the EMA position stands and the 3 g/day allowance is not carried into this monograph. The reason is arithmetic rather than preference. The Finnish signal attaches to a heavy exposure of 500 mg glycyrrhizin a week, which is about 71 mg a day [46,47]. Root that meets the Ph. Eur. minimum of 4.0 per cent glycyrrhizin delivers, at 3 g a day, about 120 mg a day [3]; at the 6 per cent upper end of the range Mills and Bone give, about 180 mg [10]. A 3 g/day allowance therefore permits an intake well above the exposure associated with preterm delivery, and above the 100 mg ceiling at which a randomised crossover trial has already measured a pressor effect in healthy young adults [40]. Mills and Bone’s own sentence is hedged ("likely to be safe for short periods") and carries no supporting study. Braun and Cohen, writing for the same Australian readership, say licorice is contraindicated in pregnancy without qualification [11]. Licorice is not prescribed in pregnancy at AIP, in any preparation containing glycyrrhizin, at any dose, and the incidental exposure from a flavouring quantity in a formula is avoided as well. Deglycyrrhizinated licorice is a separate question on which there is no pregnancy data either way, and it is not recommended in the absence of any.
- Women with or prone to pre-eclampsia should avoid licorice: 11β-HSD activity is significantly lower in pre-eclamptic placentas and umbilical cord cortisol higher, with decreased foetal weight [10].
Lactation. Mills and Bone state that licorice is compatible with breastfeeding [10]. The EMA does not agree: glycyrrhizin is detectable in the breastmilk of some women taking liquorice, no study has measured glycyrrhetinic acid in milk, the effect on the infant is unknown, and use during breastfeeding is not recommended [7,8]. Medicine’s ruling, 23/09/2026: the EMA position is adopted and licorice is not recommended in lactation. The conflict is real and stays printed. Mills and Bone’s "compatible with breastfeeding" is a bare assertion with no study behind it in their text [10]; the EMA’s position rests on the finding that glycyrrhizin is detectable in the breastmilk of some women taking liquorice, on the absence of any measurement of glycyrrhetinic acid in milk, and on the absence of any infant data [7,8]. Where one source asserts safety without evidence and the other declines to assert it because the measurements have not been made, Medicine follows the one that matches the state of the evidence. MediHerb’s own guide says only that "professional supervision is suggested for pregnancy and lactation" [80], which is a supervision instruction and not a safety finding, and it does not change the ruling.
15.6 Children, older people, overdose
Children and adolescents. The EMA: use under 18 years is not recommended, because it has not been established for want of adequate data [7]. WHO: safety and effectiveness in children have not been established [9]. Mills and Bone warn that children like licorice confectionery and that its use as a flavouring in tinctures should be moderate [10]. A child with Addison’s disease consuming 300-400 g/day of confectionery developed reversible growth retardation [10].
Older people. Special precautions in the elderly, and in anyone with hypertension or cardiac, renal or hepatic disease; do not give high-glycyrrhizin preparations for prolonged periods, and monitor closely [10]. MediHerb’s own guide says "exercise care with elderly patients" [80].
Overdose. The EMA records overdose with prolonged use beyond 4 weeks or high intake, presenting as water retention, hypokalaemia, hypertension, cardiac rhythm disorders and hypertensive encephalopathy [7]. Five reported cases link high-dose ingestion to transient visual loss [10,11].
Toxicology. Acute intraperitoneal LD₅₀ for glycyrrhetinic acid in mice 308 mg/kg; oral LD₅₀ greater than 610 mg/kg. Little short-term, subchronic or chronic toxicity in rats given glycyrrhizin salts; genotoxic and carcinogenic effects have not been observed for glycyrrhizin derivatives [10]. The EMA notes that adequate tests on reproductive toxicity, genotoxicity and carcinogenicity have not been performed for the herbal preparations themselves [7]. A 2017 review gathers the acute, sub-acute, sub-chronic and chronic toxicity work on G. glabra and glycyrrhizin salts in one place and reaches the same practical conclusion as this monograph: the effects that matter in people are hypertension and the consequences of hypokalaemia, and the risk rises with prolonged gastrointestinal transit, reduced 11β-HSD2 activity, existing hypertension, anorexia nervosa, older age and female sex [64].
15.7 Practical risk reduction
- Prescribe by glycyrrhizin, not by millilitres. Ask for the assayed content of the batch and calculate the daily glycyrrhizin.
- Take a blood pressure before prescribing, and again during, as MediHerb’s own guide directs [80].
- High potassium, low sodium diet for anyone on high-glycyrrhizin preparations for more than a short period; monitor weight and blood pressure [10,11,80].
- Use DGL where the flavonoids are what is wanted — ulcer, dyspepsia, mucosal healing — and keep whole root for where the glycyrrhizin is the point [10,11].
- Take a licorice-food history. Confectionery, liquorice tea and Chinese and Kampo formulas all contribute. A Danish survey found pure liquorice confectionery at a mean 17,922 mg/kg glycyrrhizic acid, and one Dutch herbal-tea brand at 450 mg/L of the prepared beverage [8].
- Stop 7 days before general anaesthesia [80].
- Anyone considering licorice should consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy.
Inside the typeset monograph


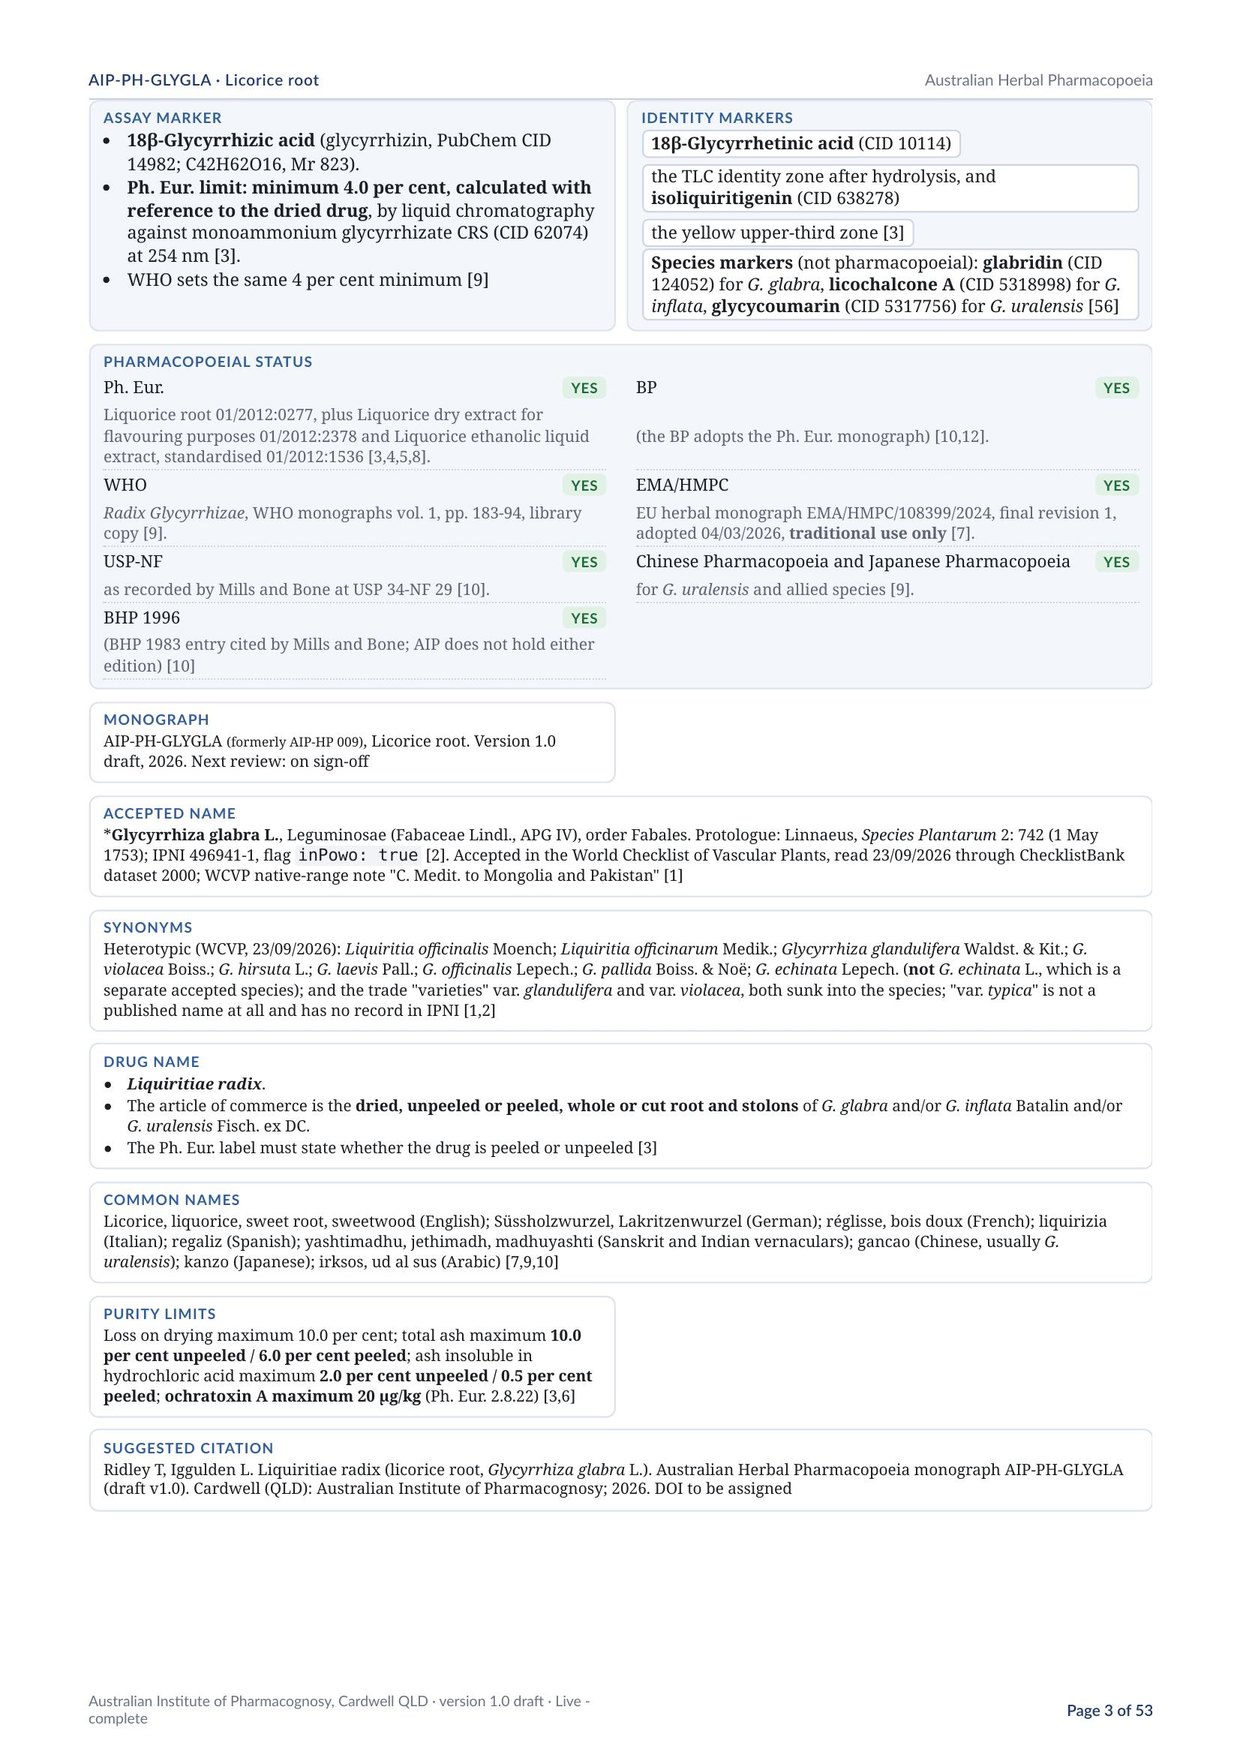










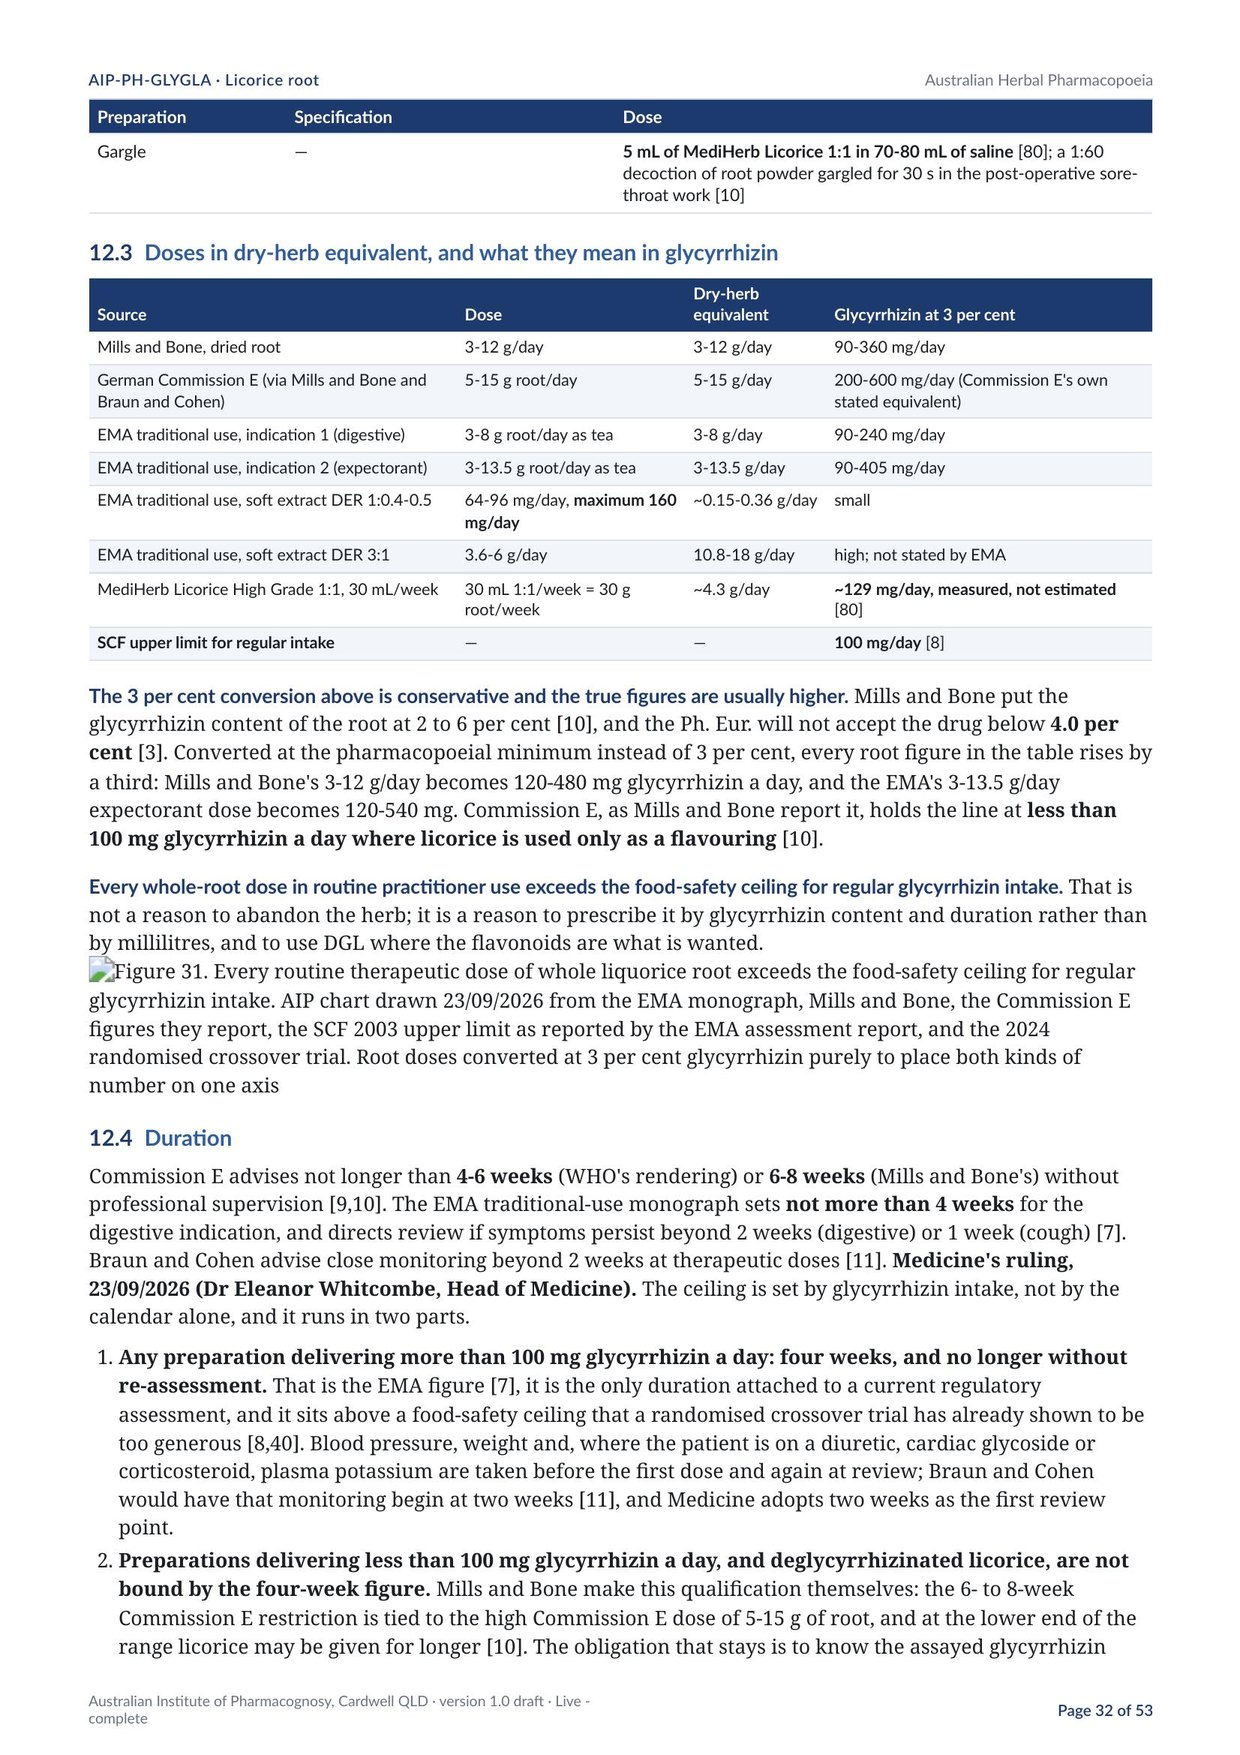

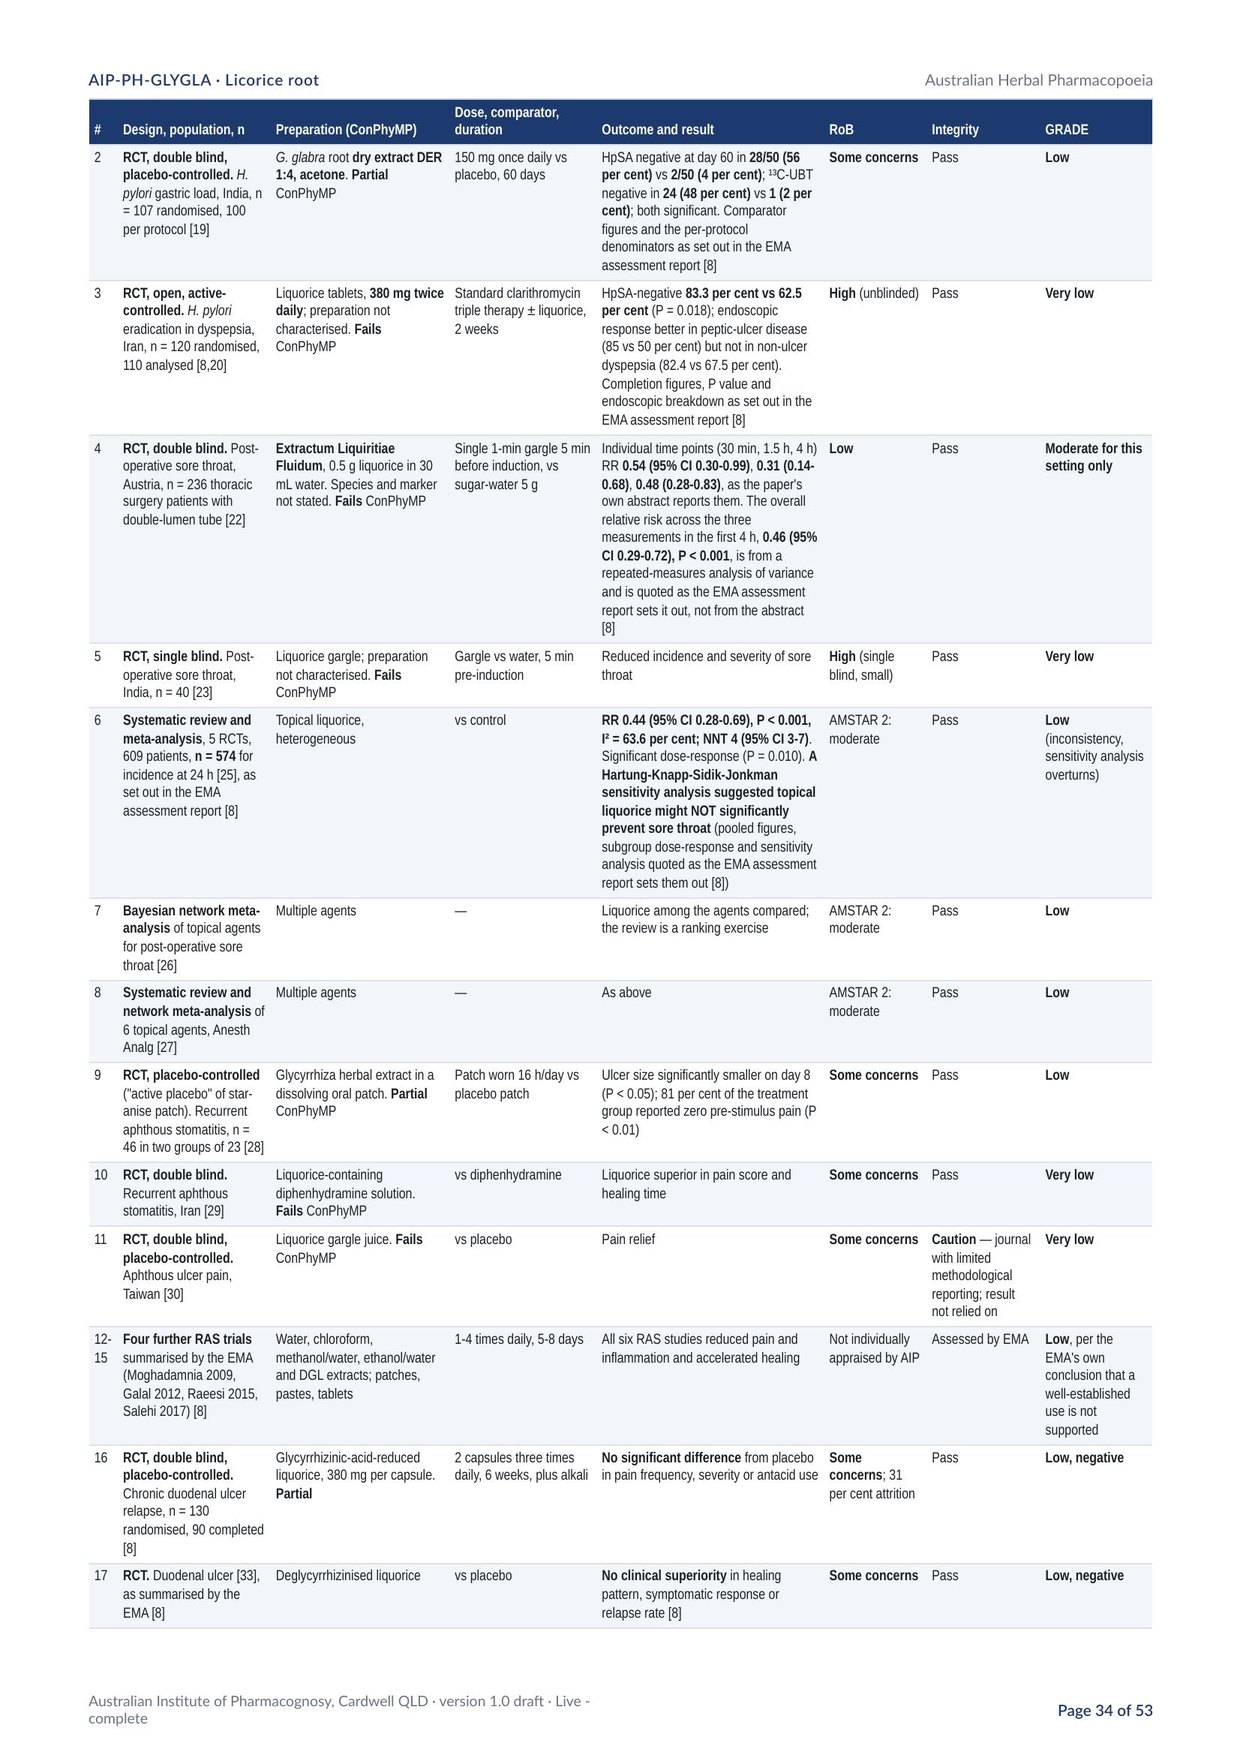
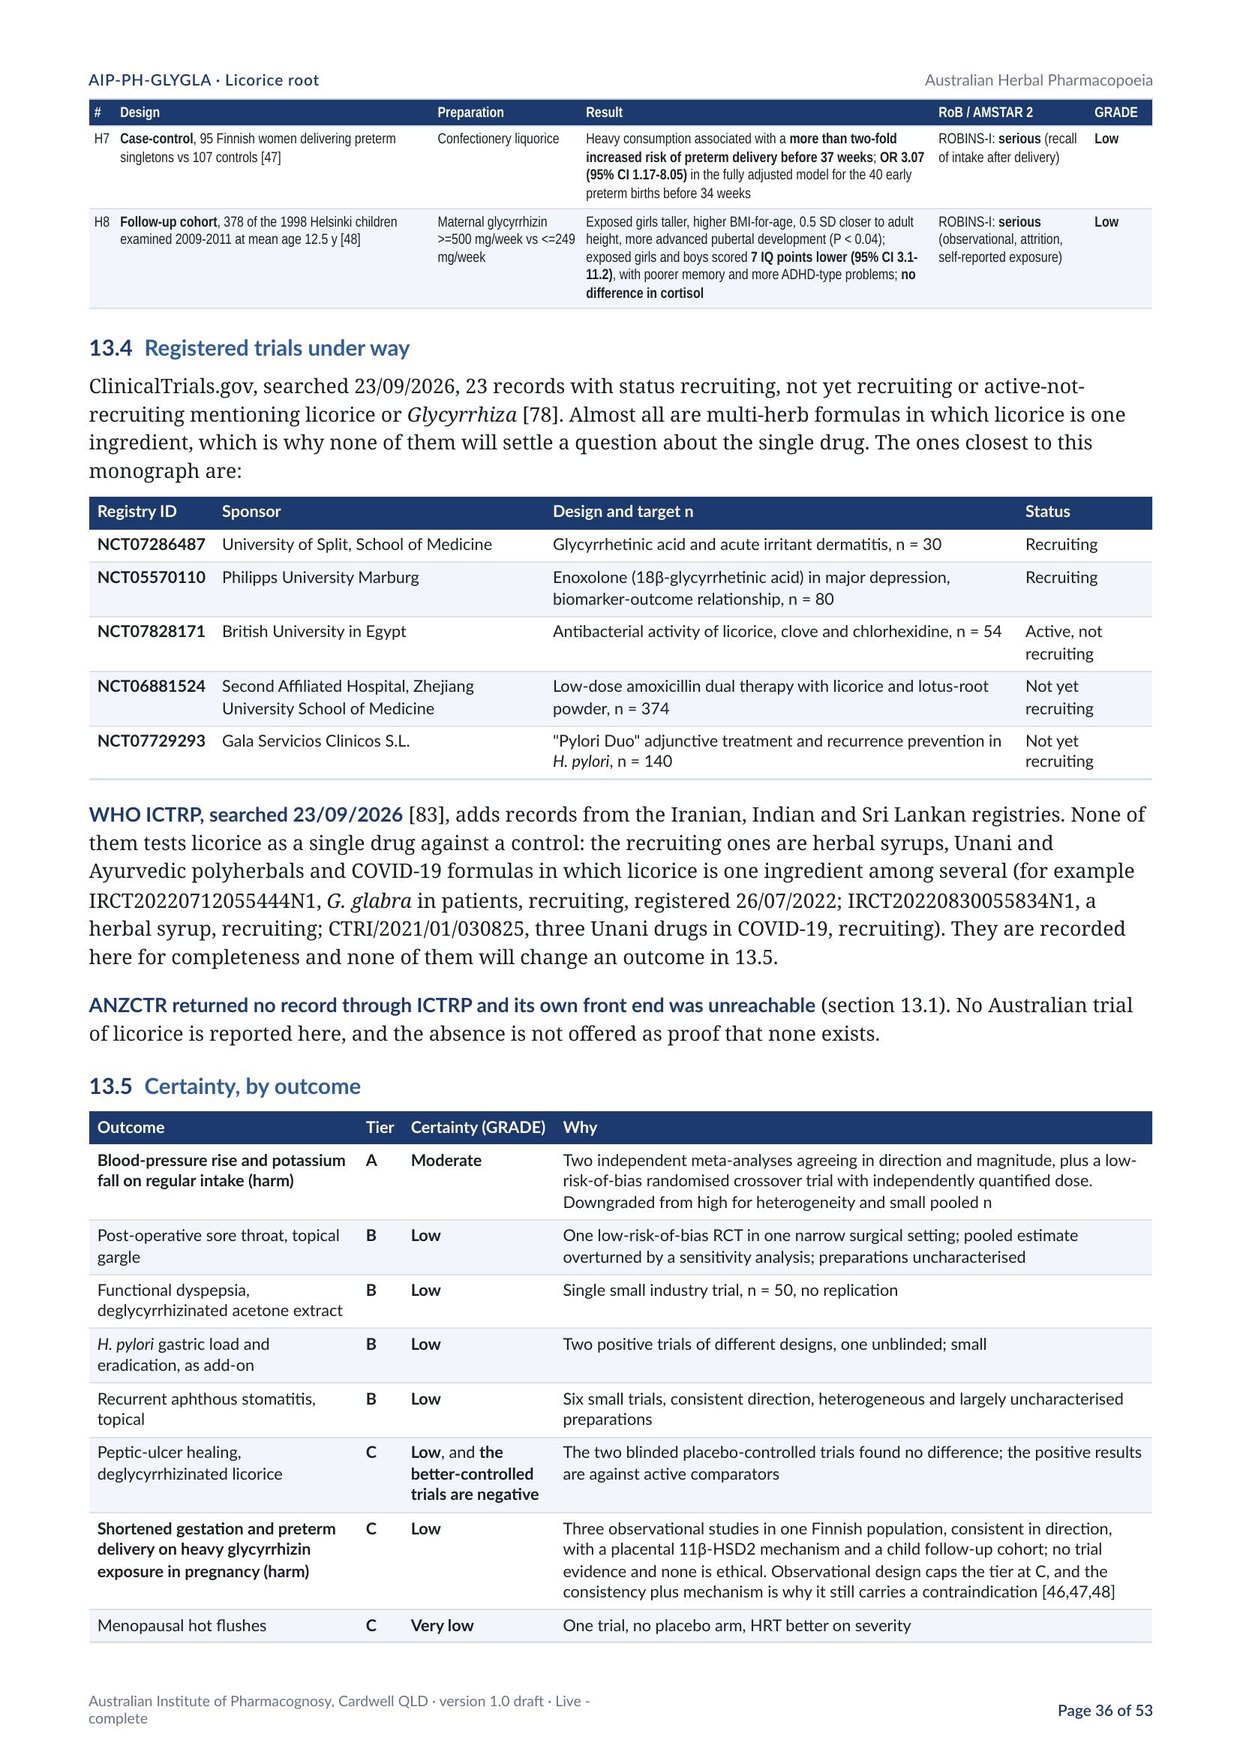
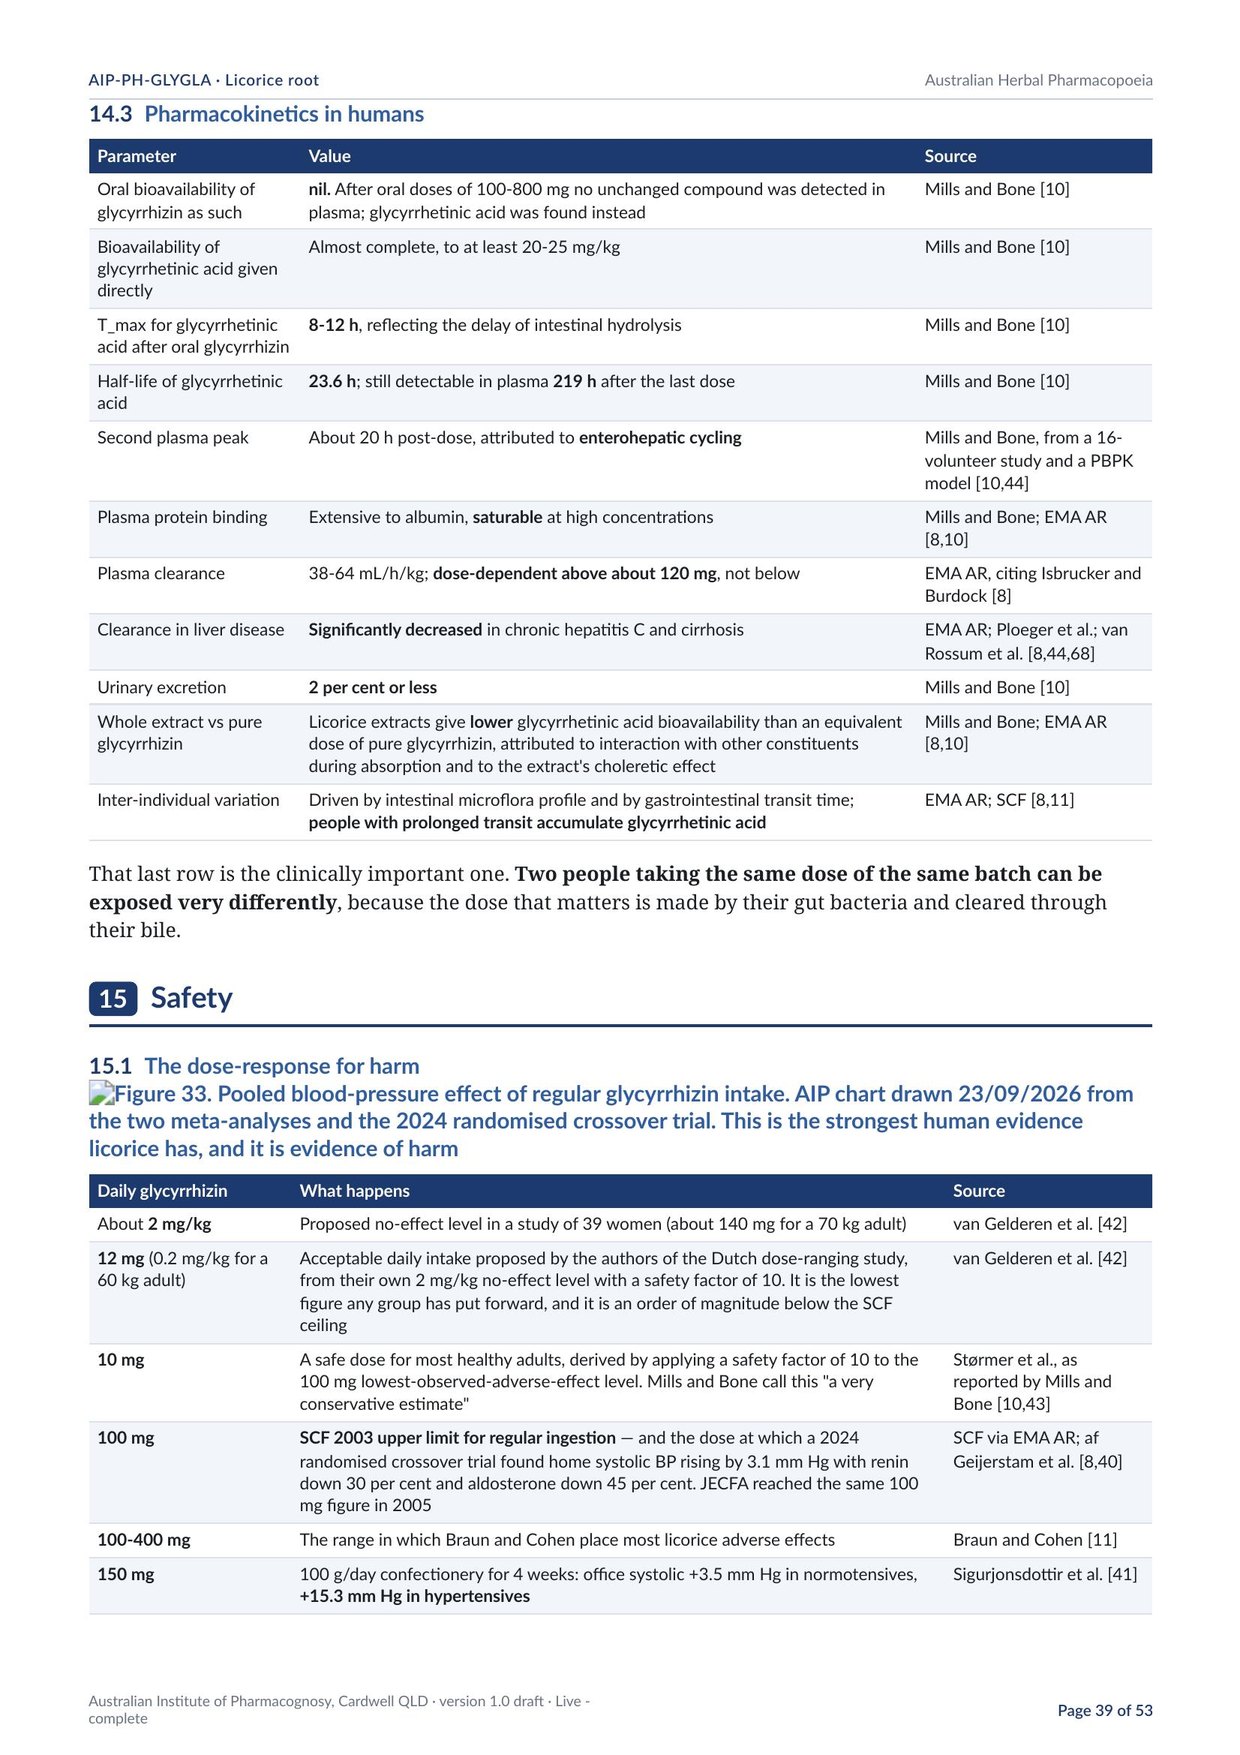
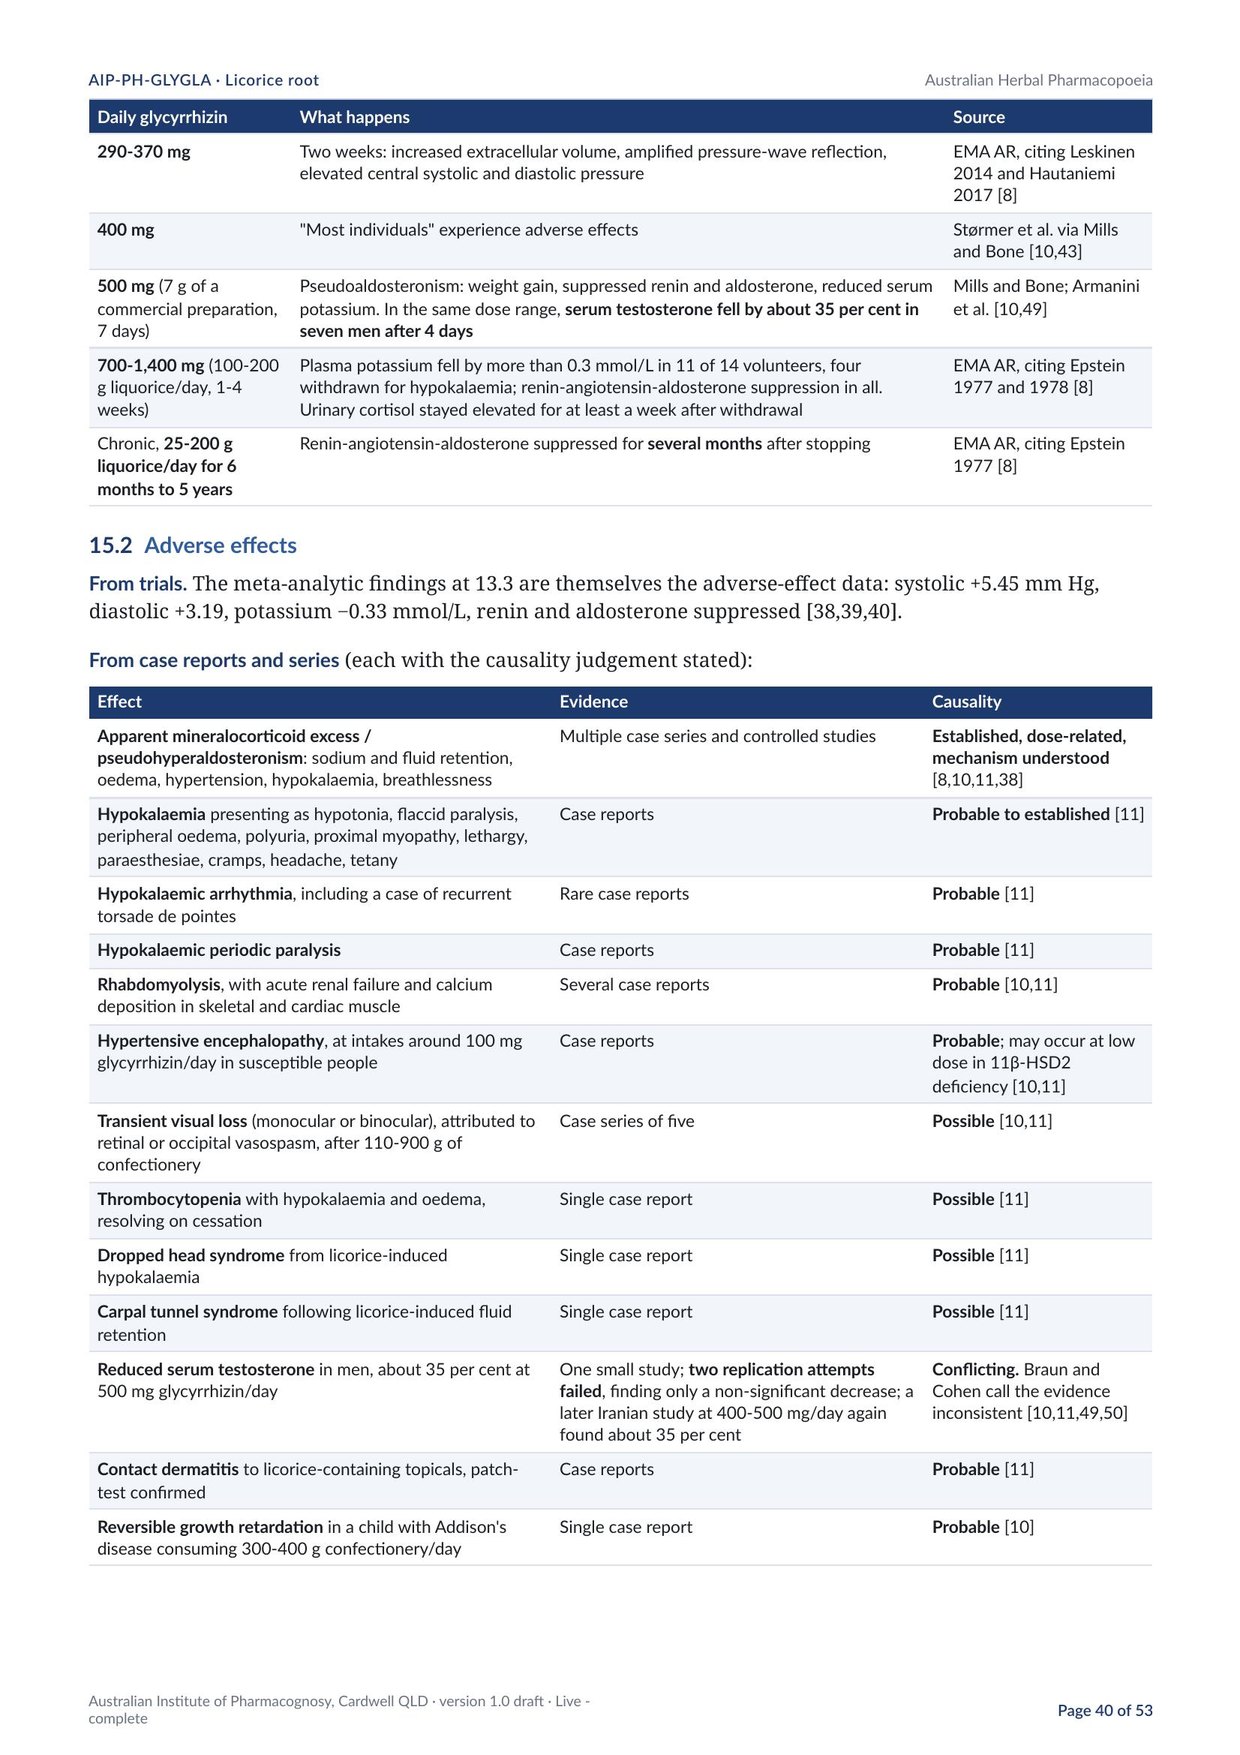
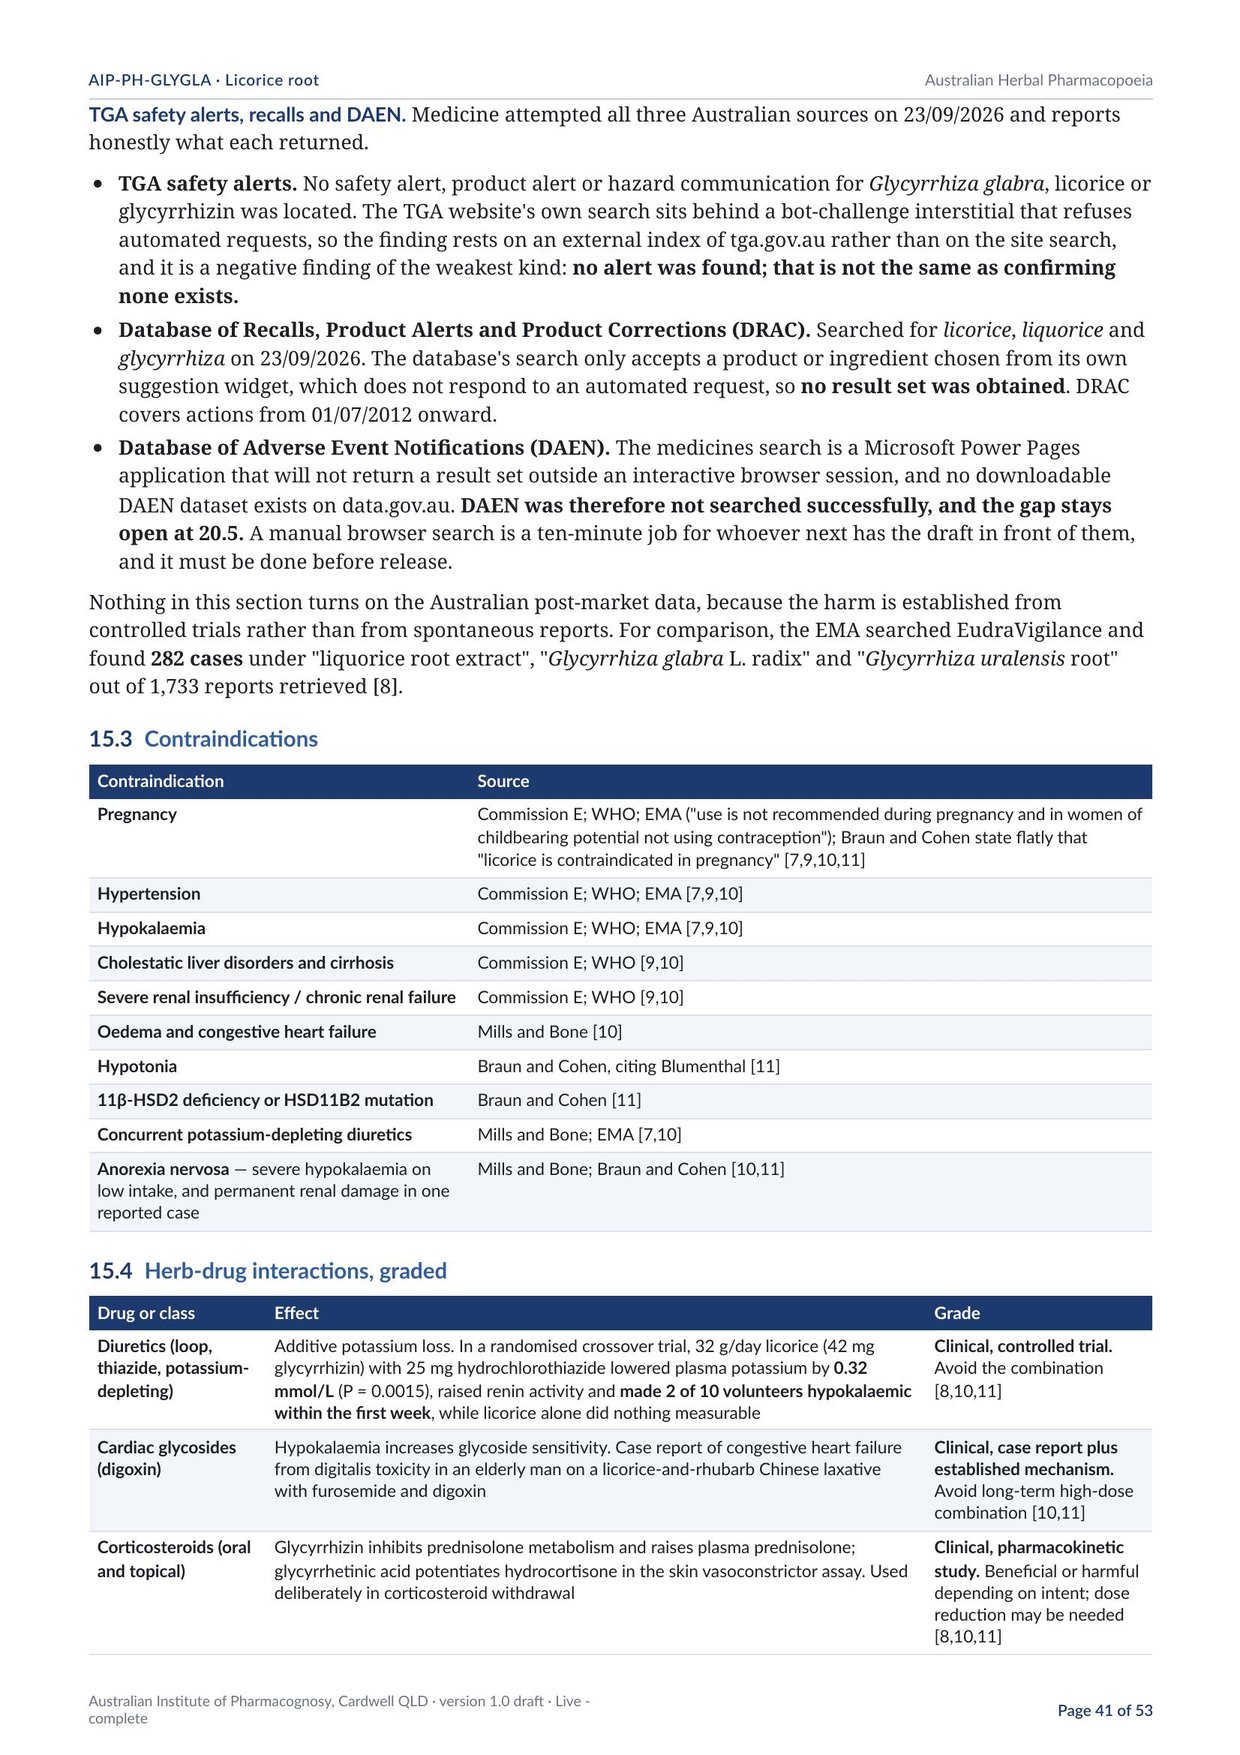



Tap a page to open it big enough to read.
15 pages read at full size, the safety section among them. The pages shown small are in the full monograph.
- 53 pages, read in the AIP Reader
- Version 1.0 draft
- Licence personal, for life, one screen at a time
AUD $20this monograph in full, in the AIP Reader
The preview and the safety section are free, with no account and no sign-in. The microscopy, the chemistry, the TLC and HPLC fingerprints and the rest read in the AIP Reader, on this AUD $20 licence or a Scholar membership.
47 more pages follow · 23,537 words, 27 figures, 24 tables
Still to come in this monograph
- 1. Nomenclature
- 2. Definition
- 3. Source and Australian supply
- 3.1 Where it must be grown: origin, climate and chemistry
- 4. Macroscopy
- 5. Microscopy
- 6. Chemistry
- 7. Named markers and assay limits
- 8. TLC fingerprint
- 9. HPLC fingerprint
- 10. Identity, purity, adulterants and contaminants
- 11. Traditional use
- 12. Current practice: use, preparations and doses
- 13. Clinical evidence
- 14. Pharmacology
- 16. Discussion
- 17. Conclusions
- 18. Research still needed
- 19. References
- 20. Document control
The rest of this monograph reads in the AIP Reader: every page in your name, always the current version, on a Scholar membership or the AUD $20 copy of this one title.
Checking your membership…
Report an error or submit evidence
If something in this monograph is wrong, out of date or missing, tell us and show us the evidence. Every report is logged under the AIP Evidence Charter and assessed on the evidence alone; the outcome is kept on the record, and an upheld report is corrected with a dated notice on this page.
Open the report form
The typeset edition of this monograph, set for print with the plates and chromatograms at full size, is $20 AUD in Publications.


