


Blue cohosh root and rhizome (Caulophyllum thalictroides (L.) Michx.), Berberidaceae
Australian Herbal Pharmacopoeia (working title) · Monograph AIP-PH-CAUTHA · Version 1.0 draft
Date: 2026
Status: working document, version 1.0. Not a statutory standard.
Prepared by: the Australian Institute of Pharmacognosy, Far North Queensland, Australia. Every author and contributor is named at the end of the monograph.

0. Free-teaser block

0.1 Identity card
| Register number | AIP-PH-CAUTHA (MediHerb A–Z list No. 20) |
| Title | Blue cohosh root (Caulophyllum thalictroides (L.) Michx.), Caulophylli rhizoma et radix |
| Version / year | 1.0 draft, 2026. Next review 2029, or sooner when the 27 primary papers now being obtained in full text have been read, or if a human study reports |
| Accepted binomial | Caulophyllum thalictroides (L.) Michx., Flora Boreali-Americana 1: 205 (1803). Basionym Leontice thalictroides L., Species Plantarum: 312 (1753). Accepted in the World Checklist of Vascular Plants (WCVP) version 16.0 of 04/06/2026, the dataset Plants of the World Online displays, read through ChecklistBank in September 2026; IPNI 1056122-2 [1] |
| Family | Berberidaceae, order Ranunculales, as placed in APG IV, which WCVP follows for flowering-plant families [1,54]; subfamily Nandinoideae, tribe Leonticeae [34,55]. No family change affects the genus |
| Plant part | Dried rhizome and roots [9,10,11]; sold in the Australian practitioner trade as "root" [13] |
| Latin drug name | Caulophylli rhizoma et radix (AIP form). The US National Formulary IV (1916) called the drug "Caulophyllum", the dried rhizome and roots [11] |
| Principal synonyms | Leontice thalictroides L. (basionym); Leontice thalictrifolium Salisb. (illegitimate, superfluous name) [1]. Not synonyms: C. giganteum (Farw.) H.Loconte & W.H.Blackw. and C. robustum Maxim. are accepted as separate species by WCVP [1] |
| Common names | English: blue cohosh, squaw root, papoose root, false cohosh, blueberry (old regional name) [9,14]; blue ginseng, yellow ginseng [17]. French (Québec): caulophylle faux-pigamon [35]. The Asian sister species C. robustum is hong mao qi in Chinese [22] |
| Pharmacopoeial status elsewhere | US Pharmacopeia 1882–1905 (as reported) [22,32]; the USDA’s 1907 bulletin names the 1890 edition [57]. US National Formulary IV (1916): yes, "Caulophyllum", with macroscopy, powder microscopy and ash not more than 6 per cent, quoted in the US Dispensatory 1918 [11]. British Herbal Pharmacopoeia 1983: listed (as reported by Barnes; the BHP text itself is not among the sources read) [14]. Ph. Eur.: no monograph in the 8th edition read [39]. BP, WHO, EMA/HMPC, ChP, API: no monograph found in the sources searched |
| Australian status | Permissible Ingredients Determination: yes, item 1247 CAULOPHYLLUM THALICTROIDES, purposes A (active), E (excipient) and H (homoeopathic), no specific requirements [2]. Poisons Standard: blue cohosh is not named; two minor constituent alkaloids are, as substances: cytisine (Schedules 3 and 4) and sparteine (Schedule 4) (section 10) [3]. ARTG: a product-name search found no product called blue cohosh or Caulophyllum [51]. Not recorded growing in Australia: the 50 Caulophyllum specimens in Australian and New Zealand herbaria were all collected overseas [4]. Not native, so no Nature Conservation Act 1992 (Qld) permit applies; not a prohibited or restricted invasive plant under the Biosecurity Act 2014 (Qld) [5] |
| Named markers | Magnoflorine (CID 73337): identity, assay proposed; no limit. N-Methylcytisine (CID 670971): safety marker; no limit exists anywhere. Caulosides C and D, and hederagenin after hydrolysis (CIDs 13878151, 21630094, 73299): identity; no limit. Total ash: not more than 6 per cent (NF IV) [11] |
| Evidence snapshot | Dysmenorrhoea: Tier T, 0 trials. Amenorrhoea and irregular menstruation: Tier T, 0 trials. Preparing for or inducing labour: Tier T, 0 trials, and contraindicated (section 15). Rheumatic pain: Tier T, 0 trials. Anti-inflammatory: Tier P, cell and mouse studies of the saponins. Toxicity signals (teratogenic alkaloid, mitochondrial damage by saponins, neonatal case reports): preclinical and case-report evidence, graded in section 15 [13,15,22–24] |
| Suggested citation | Ridley T, Iggulden L. Blue cohosh root (Caulophyllum thalictroides (L.) Michx.), Caulophylli rhizoma et radix. AIP-PH-CAUTHA, version 1.0 draft. Cardwell: Australian Institute of Pharmacognosy; 2026. DOI to be assigned |
| Provenance | Original AIP data: none. Every analytical figure, limit, method and dose belongs to the source cited beside it. Every photograph of the living plant or fresh rhizome is a licensed photograph, named by its photographer, and its identification is provisional. Sections 4, 5, 7, 8, 9 and 10 carry AIP bench data pending (no AIP voucher, section, plate or run yet). The map (Figure 9), charts (Figures 10–15) and drawings (Figures 3c, 5, 6, 6b) are AIP drawings from cited data |
| Compiler and review | Compiled by Dr Thomas Ridley (Education and Research). Technical review: Dr Fiona MacAllister (Botanical, sections 1-5 and the adulterant species of 10), reviewed in 2026; Dr Hana Suzuki (QA, sections 6-10), reviewed in 2026; Dr Eleanor Whitcombe (Medicine, sections 12, 13, 15), reviewed in 2026. Layout and figures (Figures 1–15, captions, credit lines and page design): Jesse Kirby (Community Outreach), reviewed in 2026. Evidence and citation audit (every reference, the sources of sections 6–9, 12 and 15, and the conclusions against section 13): Dr Thomas Ridley (Education and Research), reviewed in 2026; as compiler he is not an independent reader of sections 11, 14 and 16–18, which still need a reader outside Education and Research. Published: not yet. Last modified: 2026. Version 1.0 draft |
| Canonical URL | /pharmacopoeia/caulophyllum-thalictroides/ (on publication) |
0.2 Summary
Blue cohosh is the dried rhizome and roots of Caulophyllum thalictroides, a spring-flowering woodland perennial of the barberry family, native to central and eastern Canada and the eastern United States. It does not grow wild in Australia and is imported. No current pharmacopoeia carries it. The last official standard was the US National Formulary IV (1916), which described a knotty, horizontal rhizome under a matted mass of wiry roots, a starch-rich powder, and an ash limit of 6 per cent.
The chemistry has two sides. Quinolizidine and aporphine alkaloids include magnoflorine, the most abundant, and N-methylcytisine, a nicotinic agonist that was teratogenic in rat embryo culture. Oleanane saponins built on hederagenin and caulophyllogenin (the caulosides) are the larger fraction by weight. No pharmacopoeia sets a content limit for any of them. The fingerprint methods published for the drug are being obtained in full text; this edition gives the two systems read in full, an HPLC fingerprint validated on the Asian sister species and an LC-MS profiling method used on US blue cohosh products, and flags AIP bench work as pending.
Australian practitioners who still use it prescribe a 1:2 liquid extract at 10 to 20 mL a week for painful or delayed periods. That use rests on Eclectic and later practitioner tradition; no clinical trial of the herb has been found. The main safety point is pregnancy: blue cohosh was long used to bring on labour, and neonatal heart failure, stroke and hypoxic injury have been reported after maternal use. It is contraindicated in pregnancy, while breastfeeding and when trying to conceive.
0.3 Contents with extent
| Section | Extent (A4 pages, estimated for this printing) |
|---|---|
| 0 Free-teaser block | 4 |
| 1 Nomenclature | 2 |
| 2 Definition | 1 |
| 3 Source and Australian supply, with 3.1 origin, climate and chemistry | 4 |
| 4 Macroscopy | 6 |
| 5 Microscopy | 3 |
| 6 Chemistry | 3 |
| 7 Named markers and assay limits | 2 |
| 8 TLC fingerprint | 2 |
| 9 HPLC fingerprint | 3 |
| 10 Identity, purity, adulterants and contaminants | 3 |
| 11 Traditional use | 3 |
| 12 Current practice | 2 |
| 13 Clinical evidence | 2 |
| 14 Pharmacology | 3 |
| 15 Safety | 3 |
| 16–18 Discussion, conclusions, research needed | 4 |
| 19 References | 3 |
| 20 Document control | 2 |
| Totals (draft) | About 55 A4 pages. 38 embedded figures: 16 licensed or public-domain photographs of the living plant, flower, fruit and seed; 2 licensed photographs of fresh rhizome and roots; 4 public-domain plates and drawings and 1 licensed herbarium sheet; 1 public-domain page of 1920 section drawings; 2 licensed HPLC chromatogram panels (of the Asian sister species, not blue cohosh); 2 AIP composites of PubChem structures; 9 AIP drawings, charts and replots; 1 captioned placeholder for the AIP TLC plate. About 22 tables. 0 AIP photomicrographs, 0 AIP chromatograms, 0 AIP plates. 0 clinical trials of the herb to grade (1 trial of a homoeopathic dilution graded for comparison); 1 trial register searched in full and 2 more attempted; 2 literature databases searched. 59 numbered references |
Gaps stated plainly. AIP holds no voucher, photomicrograph, TLC plate or chromatogram of blue cohosh. No openly licensed photomicrograph of the drug was found, so Figure 4 is a public-domain page of 1920 section drawings and Figure 5 an AIP schematic drawn from the 1916 and 1920 descriptions. No openly licensed TLC plate of the drug was found, so the Figure 7 slot carries a captioned placeholder and no plate. The HPLC figure is of C. robustum and is labelled so. Every photograph of the living plant and the fresh rhizome is a licensed photograph named by its photographer; where it was taken inside the range of C. giganteum, or on a cultivated plant, the species cannot be confirmed from the image, and the captions say so (section 1). No photograph of the dried drug with a scale bar is openly licensed; Figure 3c gives the published dimensions instead. The papers that describe the validated TLC, HPTLC and HPLC methods for blue cohosh, the isolation of its alkaloids and saponins, and the neonatal case reports are on AIP’s full-text request list; none of them is used here beyond what a text AIP has read in full reports about it. The ANZCTR register, the TGA website search and the TGA adverse-event database (DAEN) refused our tools in September 2026; the WHO trial register answered but failed its control search; the CITES checklist and the DAFF BICON case could not be read. All are listed for a hand search (section 18).
0.4 Contributors and access
Compiled by Dr Thomas Ridley, Head of Education and Research. The Botanical review of sections 1–5 and the adulterant species of section 10, with Figures 1–5 and 9, was done by Dr Fiona MacAllister, Head of Botanical, in 2026. The QA review of sections 6–10, with Figures 6, 6b, 7 and 8, was done by Dr Hana Suzuki, Head of Botanical QA, in 2026. The Medicine review of sections 12, 13 and 15, with Figures 10, 11 and 12, was done by Dr Eleanor Whitcombe, Head of Medicine, in 2026. The evidence and citation audit of every reference was done by Dr Thomas Ridley, Head of Education and Research, in 2026. Each reviewer is credited by name once the review is on record. Dr Luke Iggulden, Chief Scientific Officer, is senior author: he set the scope of the pharmacopoeia series and made the research possible. A preview of the monograph and all of section 15 (Safety) are free to every reader; the full text is for Scholar members and above, or the AUD $20 copy of this one title.
Free to every reader. The safety section of every monograph is open to everyone, signed in or not. In an emergency call 000. For poisoning, call the Poisons Information Centre on 13 11 26.
15. Safety
Red flags (Medicine, reviewed 2026).
- Pregnancy, at any stage, including to induce or assist labour: do not use. Neonatal heart attack and heart failure, perinatal stroke and hypoxic brain injury have been reported after maternal use in late pregnancy, one of its constituents is teratogenic in embryo culture, and a root extract disrupts heart and face development in fish embryos [17,18,22,28]. Evidence: case reports (very low certainty for cause) with consistent preclinical toxicity; no study shows safety.
- Breastfeeding and trying to conceive: do not use [13,18,31]. Evidence: manufacturer and practitioner-text contraindications; no human data.
- Children: keep the plant and the seeds away from them. Children have been poisoned by eating the bright blue seeds [14].
- Signs of nicotinic poisoning after a blue cohosh preparation (fast heart, sweating, abdominal pain, vomiting, muscle twitching or weakness, high blood pressure, fits, laboured breathing) are an emergency: call 000, or the Poisons Information Centre on 13 11 26 for advice [14,18,30].
- Blue cohosh is a different plant from black cohosh (Actaea racemosa), and practitioner texts warn against confusing them [8]; one of nine US products sold as blue cohosh contained black cohosh, and two were homoeopathic sugar tablets (section 10) [25]. Check the botanical name and plant part on the label.
Adverse effects from trials. None; there are no trials.
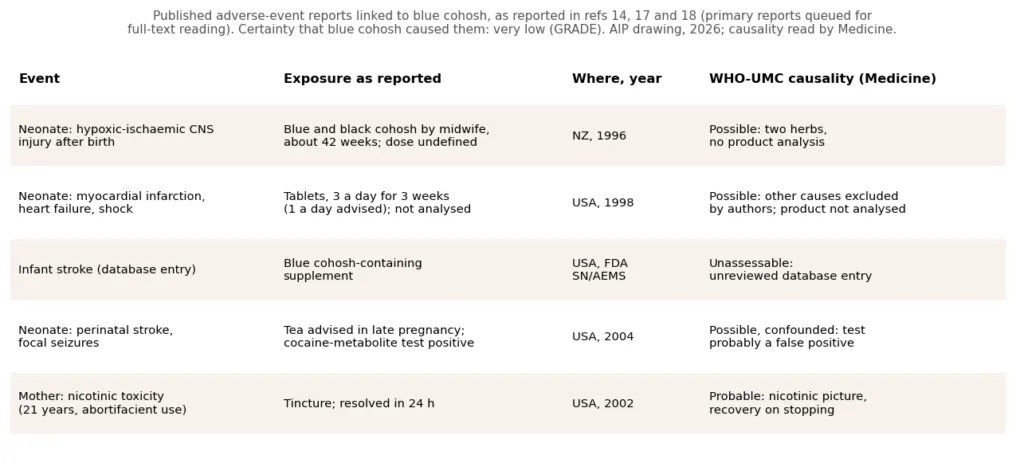
Case reports and causality. The primary reports are on the full-text request list; the accounts below are as given in the full-text library books and reviews cited. Causality is read on the WHO-UMC scale by Medicine (Dr Eleanor Whitcombe), from those accounts; it will be re-read when the primary reports arrive. Certainty that blue cohosh causes these outcomes, taken together: very low (GRADE; case reports only, no product analysed, co-exposures in two).
| Report | Exposure as reported | Outcome | Causality (AIP reading) | Source |
|---|---|---|---|---|
| New Zealand, 1996 | Blue and black cohosh given orally by a midwife to induce labour at about 42 weeks; dose undefined | Infant did not breathe at birth; severe multi-organ hypoxic injury, permanent CNS damage | Possible; two herbs; product not analysed | [17,18] |
| USA, 1998 | Tablets, 1 a day advised, 3 a day taken for 3 weeks before delivery; herb quantity not stated; not analysed | Newborn with acute myocardial infarction, heart failure and shock. Bone and Mills report cardiomegaly and mildly reduced left ventricular function still present at 2 years [18]; Mills and colleagues say only that he eventually recovered [17] | Possible; the report’s authors excluded other causes of infarction, but the product was not analysed and the account of dose and duration differs between sources [17,18,32] | [17,18,32] |
| USA, FDA adverse-event database | Blue cohosh-containing supplement | Infant stroke | Unassessable; unreviewed database entry, poorly documented [18] | [18] |
| USA, 2004 | Tea advised in late pregnancy; failed vaginal delivery, caesarean | Perinatal stroke with focal seizures; urine and meconium, and the tea, tested positive for a cocaine metabolite, later judged a probable false positive | Possible, confounded | [18] |
| USA, 2002 | 21-year-old woman, tincture taken to induce abortion | Tachycardia, sweating, abdominal pain, vomiting, muscle weakness and fasciculations; resolved in 24 h | Probable (a nicotinic picture consistent with N-methylcytisine, with recovery on stopping; not rechallenged, product not analysed); one review scored it probable on the Naranjo scale | [14,17,18,46] |
Midwives in the 1999 US survey also reported nausea, more meconium-stained fluid and transient fetal tachycardia with blue and black cohosh, without separating the two herbs [16,18]. Trickey records that these reports were formally disputed, citing a 1997 reply to the New Zealand case, on the ground that the toxic effects would need much higher doses than those reported, and advises caution in pregnancy until the question is settled [15]. That dispute does not weaken the red flag: the reports are few and uncontrolled, but their outcomes are grave and no study shows safety.
Toxicology. Nicotinic toxidrome with high doses: nausea, vomiting, headache, dizziness, fasciculations, seizures, tachycardia, tachypnoea and hypertension, progressing to respiratory failure, with muscarinic signs (salivation, bronchorrhoea, slow heart) possible; the saponin fraction is credited with vasoconstriction, hypertension and vaso-occlusion; the review notes that death can follow severe untreated poisoning [30]. Evidence: a clinical toxicology review extrapolating from nicotine and the case reports, not from measured blue cohosh overdoses. The powdered root irritates mucous membranes [14], and the dust provokes sneezing [11]. Developmental and mitochondrial toxicity in section 14 [22,23,28]. No repeat-dose animal study of the root was found.
Contraindications.
Each line carries its sources and the kind of evidence behind it.
- Pregnancy: contraindicated [13,19,45]; Mills and Bone’s pregnancy table lists it as contraindicated "except to assist with birth" [18]; Hechtman’s pregnancy table, taken from Romm, gives AHPA class 2b and Mills and Bone category D, "possibly safe for short-term use during labour only, and with proper monitoring of fetal heart tones", while Hechtman’s own text says it "is no longer recommended for use in pregnancy" [16]. Trickey (2003) still gave a first-trimester dose, not more than 0.25–0.5 mL three times a day, always with Viburnum prunifolium and only on a trained herbalist’s prescription [15]; that advice is superseded by the current manufacturer contraindication and is not followed here. AIP adopts the strictest position, with no exception for labour (red flag 1). Evidence: case reports (very low certainty) with consistent embryo-culture and fish-embryo toxicity; practitioner consensus.
- Lactation: contraindicated [13,18]; LactMed finds no data on use while breastfeeding, notes the gastrointestinal and cardiovascular toxicity, and reports that most sources recommend strongly against it [31]. Evidence: no human data; precaution from toxicity.
- Women trying to conceive: contraindicated [13]. Evidence: manufacturer label, with antifertility and developmental effects in animals and embryo culture (section 14); no human data.
- Cardiovascular disease, hypertension or angina: avoid. Barnes notes that it is not known whether excessive doses raise blood pressure through N-methylcytisine, and an older British compendium warns of interference with angina therapy [14,20]; the caulosaponin constricted coronary vessels in animals [14]. Evidence: pharmacology and theory; no human study. AIP makes this an avoid rather than a caution because the toxicity would fall on the heart.
- Gastrointestinal inflammation: may irritate [14]. Evidence: reference-text statement.
Herb–drug interactions.
| Interacting drug | Grade | Basis |
|---|---|---|
| Drugs metabolised by CYP3A4, 2D6, 2C19, 1A2 | Theoretical (in vitro alkaloid fraction only; the whole methanolic extract did not inhibit) | [22] |
| Cardiovascular drugs, including antianginals and antihypertensives | Theoretical | [14,17,20] |
| Nicotine and nicotinic agents (including varenicline or cytisine for smoking cessation) | Theoretical, additive | [17]; AIP interpretation |
| Antidiabetic drugs | Theoretical (tertiary database) | [17] |
| Oxytocics and prostaglandins used in labour | Theoretical, additive | AIP interpretation |
| General anaesthesia | Precaution: stop 7 days before | [13] |
No clinical interaction study or pharmacokinetic interaction study exists, so no interaction is graded above theoretical. MediHerb refers prescribers to its separate herb–drug interaction chart for this extract [13].
Children and older people. No data. Not for children: no source read gives a dose for children, and children have been poisoned by the seeds (red flag 3). This is AIP’s position, from the absence of data. Older people: no data; those with heart disease or high blood pressure should avoid it (see contraindications).
Overdose. There is no antidote. Treat as nicotinic poisoning: cardiovascular and respiratory support, fluids and vasopressors for low blood pressure, benzodiazepines for seizures, atropine for muscarinic signs, antihypertensives for a hypertensive crisis; haemodialysis is unlikely to help [30]. In Australia, call 000 in an emergency; the Poisons Information Centre is on 13 11 26.
Australian safety record. Checked by Medicine in September 2026. The TGA website search and the DAEN medicines search both returned a bot-protection challenge page to our tools, so neither could be read that day; a web search restricted to the TGA site returned no TGA page naming blue cohosh or Caulophyllum. That is not proof of absence. No TGA safety alert, advisory or recall for blue cohosh was found in any source read, and none is cited by the Australian practitioner texts [13,15,16,19]. The DAEN query and a TGA alert search by hand stay on the list in section 18; the result, nil or not, is to be added here. Blue cohosh is a permitted ingredient with no specific requirements (section 0.1) [2]; no ARTG product carries its name [51].
Referral. Anyone considering blue cohosh should consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy, and should not use it at all if pregnant, breastfeeding or trying to conceive.
31 more pages follow · 15,514 words, 35 figures, 12 tables
Still to come in this monograph
- 1. Nomenclature
- 2. Definition
- 3. Source and Australian supply
- 4. Macroscopy
- 5. Microscopy
- 6. Chemistry
- 7. Named markers and assay limits
- 8. TLC fingerprint
- 9. HPLC fingerprint
- 10. Identity, purity, adulterants and contaminants
- 11. Traditional use
- 12. Current practice: use, preparations and doses
- 13. Clinical evidence
- 14. Pharmacology
- 16. Discussion
- 17. Conclusions
- 18. Research still needed
- 19. References
- 20. Document control
The rest of this monograph is open to members. One membership covers every members’ feature on the site.
Checking your membership…
Report an error or submit evidence
If something in this monograph is wrong, out of date or missing, tell us and show us the evidence. Every report is logged under the AIP Evidence Charter and assessed on the evidence alone; the outcome is kept on the record, and an upheld report is corrected with a dated notice on this page.
Open the report form
The Institute sets and publishes its own monographs. The catalogue is in Publications.


