


Astragalus root (Astragalus mongholicus Bunge; trade and MediHerb name Astragalus membranaceus), Fabaceae
Australian Herbal Pharmacopoeia (working title) · Monograph AIP-PH-ASTMEM · Version 1.0 draft
Date: 2026
Status: working document, version 1.0. Not a statutory standard.
Prepared by: the Australian Institute of Pharmacognosy, Far North Queensland, Australia. Every author and contributor is named at the end of the monograph.

0. Free-teaser block
0.1 Identity card
| Monograph number | AIP-PH-ASTMEM (MediHerb A–Z list No. 8) |
| Title | Astragalus root (Astragalus mongholicus Bunge), Astragali mongholici radix |
| Version / year | 1.0 draft, 2026. Next review 2029, or sooner if a registered trial of the oral drug reports (section 13) |
| Accepted binomial | Astragalus mongholicus Bunge, Mém. Acad. Imp. Sci. Saint Pétersbourg, sér. 7, 11(16): 25 (1868); IPNI 478720-1. Accepted in the World Checklist of Vascular Plants (WCVP), read through ChecklistBank in September 2026 [1]. The name on the MediHerb label and in most trade and clinical literature, Astragalus membranaceus Fisch. ex Bunge (nom. cons.), is a heterotypic synonym in WCVP [1]. Re-checked by Botanical in September 2026 against the WCVP record (release loaded 06/06/2026) that Plants of the World Online publishes; the POWO page itself refused automated access that day |
| Family | Fabaceae (Leguminosae), subfamily Papilionoideae, as classified in WCVP [1,5] |
| Plant part | Whole, dried root, freed from rootlets and rootstock [2] |
| Latin drug name | Astragali mongholici radix (Ph. Eur. 2435) [2]; Astragali radix (JP XVIII, ChP) [3,17]; Radix Astragali (WHO) [4] |
| Principal synonyms | Astragalus membranaceus Fisch. ex Bunge; A. membranaceus var. mongholicus (Bunge) P.K.Hsiao; A. mongholicus var. dahuricus (Fisch. ex DC.) Podlech; A. propinquus Schischk.; Phaca membranacea Fisch. ex Link, and others (section 1) [1] |
| Common names | English: astragalus, membranous milk-vetch, Mongolian milk-vetch. Chinese: huang qi (黄芪). Japanese: ōgi. Korean: hwanggi [4,5] |
| Pharmacopoeial status elsewhere | Ph. Eur.: yes, Astragalus mongholicus root 01/2011:2435, library copy 8th Edition [2]. JP XVIII: yes, Astragalus Root [3]. ChP: yes, Astragali radix (reported by refs 13, 17; the ChP itself not read for this draft). WHO: yes, Radix Astragali, vol. 1, 1999 [4]. BP: carries the Ph. Eur. text [14]. EMA/HMPC, BHP 1996: no monograph found for this species. USP–NF: not confirmed; the USP sells astragaloside IV and Astragalus Root Dry Extract reference standards [46], which points to a compendial text, but the USP–NF itself was not read |
| Australian status | Permissible Ingredients Determination: yes, item 733 ASTRAGALUS MEMBRANACEUS, purposes A, E, H, no specific requirements [9]. Poisons Standard: not scheduled (June 2026 instrument searched in September 2026) [10]. ARTG: 244 entries returned for the keyword "astragalus", 29/09/2026, among them MediHerb Astragalus Complex (ARTG 367675) [35]. Introduced: no Australian record in the Atlas of Living Australia [36]; not native, so no Nature Conservation Act 1992 (Qld) permit applies; not listed in the Biosecurity Regulation 2016 (Qld) [34] |
| Named markers | Astragaloside IV (CID 13943297): assay, minimum 0.040 per cent on the dried drug, HPLC-ELSD, Ph. Eur. 2435 [2]. Daidzin (CID 107971) and daidzein (CID 5281708): TLC reference substances [2]. Calycosin-7-O-glucoside (CID 5318267): ChP assay marker, minimum 0.020 per cent as reported [13]; no Ph. Eur. limit. No safety marker is set |
| Evidence snapshot | Heart failure with reduced ejection fraction, add-on: Tier C, 19 RCTs (14 injection, 5 granule), very low certainty [24]. Chronic kidney disease, add-on: Tier C, 22 RCTs, 19 of them injected; the 2 oral decoction trials showed no significant change in serum creatinine; very low certainty for the oral drug [22]. Cancer-related fatigue: Tier C, 8 RCTs, all injected preparations [23]. Healthy-adult and athlete trials of oral extracts: Tier C, 4 small RCTs, no consistent clinical benefit [26–29]. Recurrent respiratory infection in children: no eligible placebo-controlled trial [21]. Qi tonic, colds, fatigue: Tier T [4,5]. Immune modulation: Tier P [5,18] |
| Suggested citation | Ridley T, Iggulden L. Astragalus root (Astragalus mongholicus Bunge), Astragali mongholici radix. AIP-PH-ASTMEM, version 1.0 draft. Cardwell: Australian Institute of Pharmacognosy; 2026. DOI to be assigned |
| Provenance | Original AIP data: none. Every analytical figure, limit, method and trial result belongs to the source cited beside it. Sections 4, 5, 7, 8, 9 and 10 carry AIP bench data pending (no AIP voucher, section, plate or run yet). The distribution map (Figure 9), charts (Figures 10–15) and drawings (Figures 2, 5, 7) are AIP drawings from cited data |
| Compiler and review | Compiled by Dr Thomas Ridley (Education and Research). Technical review: Dr Fiona MacAllister (Botanical, sections 1-5 and adulterant species in 10), reviewed in 2026; Dr Hana Suzuki (QA, sections 6-10), reviewed in 2026; Dr Eleanor Whitcombe (Medicine, sections 12, 13, 15), reviewed in 2026; Dr Thomas Ridley (Education and Research, evidence and citation audit of all references and figures, sections 6–9 sources, 11, 12, 14–19), reviewed in 2026; Jesse Kirby (Community Outreach, figures and layout), reviewed in 2026. Published: not yet. Last modified: 2026. Version 1.0 draft |
| Canonical URL | /pharmacopoeia/astragalus-membranaceus/ (on publication) |

0.2 Summary
Astragalus root is the dried taproot of a perennial Asian milk-vetch, Astragalus mongholicus, which grows wild from Siberia to northern China and is now almost all cultivated in northern China. The plant is sold everywhere under its older name, A. membranaceus; the World Checklist treats the two as one species. It does not grow in Australia and every kilogram used here is imported.
The European Pharmacopoeia identifies the drug by its long fibrous root, by fibres with tassel-like ends in the powder, and by a TLC fingerprint read against daidzin and daidzein. It sets one assay, astragaloside IV not less than 0.040 per cent. The Japanese Pharmacopoeia adds a microscopic test that catches the commonest substitute, Hedysarum root, by its crystal fibres. The chemistry varies with root diameter, age and province: thin roots carry more saponin, and in one survey of 31 Chinese batches five fell below the Ph. Eur. minimum.
The clinical record is large and weak. Most trials are Chinese, add-on, unblinded, and use injected preparations that have no counterpart in Australian practice. No trial of the oral drug reaches low certainty for a clinical outcome. Traditional use as a qi tonic is well recorded. The main safety points are its traditional avoidance in acute infection, theoretical interactions with immunosuppressants, and the absence of pregnancy data.
0.3 Contents with extent
| Section | Estimated extent (A4 pages, draft) |
|---|---|
| 0 Free-teaser block | 3 |
| 1 Nomenclature | 2 |
| 2 Definition | 0.5 |
| 3 Source and Australian supply, with 3.1 origin, climate and chemistry | 5 |
| 4 Macroscopy | 3 |
| 5 Microscopy | 3 |
| 6 Chemistry | 3 |
| 7 Named markers and assay limits | 1.5 |
| 8 TLC fingerprint | 1.5 |
| 9 HPLC fingerprint | 2.5 |
| 10 Identity, purity, adulterants and contaminants | 3 |
| 11 Traditional use | 1 |
| 12 Current practice | 2 |
| 13 Clinical evidence | 4 |
| 14 Pharmacology | 2 |
| 15 Safety | 2.5 |
| 16–18 Discussion, conclusions, research needed | 3 |
| 19 References | 3 |
| 20 Document control | 1 |
| Totals (draft) | About 50 pages. 34 embedded figures: 11 licensed plant or drug photographs from Wikimedia Commons, 3 licensed photomicrograph or section panels from one open-access paper (none is an AIP photomicrograph), 2 licensed HPLC chromatogram figures (neither is an AIP run), 5 other licensed figures from open-access papers, 3 AIP composites of PubChem structures, 10 AIP drawings and data charts. About 20 tables. 0 AIP photomicrographs, 0 AIP chromatograms, 0 AIP plates. 9 trials or systematic reviews graded, 1 reported ungraded; 12 registered trials listed. 50 numbered references, one of them withdrawn until its full text is read |
Gaps stated plainly. AIP holds no vouchered sample and has made no section, plate or run: sections 4, 5, 7, 8, 9 and 10 carry "AIP bench data pending". No licensed photograph of a developed Ph. Eur. 2435 TLC plate was found, so Figure 7 is a zone-order drawing. The licensed chromatograms (Figure 8) are research HPLC runs following the Chinese and Hong Kong methods, not the Ph. Eur. assay. The Chinese Pharmacopoeia was not read for this draft; ChP limits are given as reported by others and labelled so. Fifteen papers are on the library fetch queue and are not cited until read (section 19). ANZCTR refused access in September 2026 and the WHO ICTRP portal did not complete an automated search the same day; Europe PMC was unavailable for searching; Cochrane CENTRAL, Embase, the TGA Database of Adverse Event Notifications and the DAFF BICON import case were not searched. ClinicalTrials.gov and the TGA safety alerts were searched (sections 13 and 15).
0.4 Contributors and access
Compiled by Dr Thomas Ridley, Head of Education and Research. The Botanical review (Dr Fiona MacAllister, sections 1–5 and adulterant species in section 10) is complete. The QA review (Dr Hana Suzuki, sections 6–10), the Medicine review (Dr Eleanor Whitcombe, sections 12, 13 and 15) and the Education and Research evidence and citation audit (Dr Thomas Ridley) are complete; each reviewer is credited once their review is on record (section 20). A preview of the monograph and all of section 15 (Safety) are free to every reader; the full text is for Scholar members and above, or the AUD $20 copy of this one title.
Free to every reader. The safety section of every monograph is open to everyone, signed in or not. In an emergency call 000. For poisoning, call the Poisons Information Centre on 13 11 26.
15. Safety
Evidence grades used in this section: clinical (seen in people: trials, case reports with causality assessed), pharmacokinetic study, animal or in vitro, theoretical (inferred from pharmacology), and traditional (a rule of practice with no trial behind it).
Adverse effects in trials (clinical). The oral single-herb trials are small and mostly silent on safety. The telomere trial of a multi-ingredient product reported that all 40 participants completed and no adverse effects occurred over 6 months [30]. The knee, rowing, resistance-training and diastolic-function trials did not report adverse events at all [26–29], so their silence is no evidence of safety. In the heart-failure review, 7 of 19 trials reported on adverse reactions and 4 of those reported none; the reactions seen were hypotension, sinus bradycardia, nausea, dizziness and cough, 13.4 per cent with astragalus against 16.3 per cent with conventional care alone, and the authors say they usually settled with symptom management [24]. In the cancer-fatigue review, injected preparations were followed by fever, and in one trial rash, eczema and pruritus, mostly mild [23]. The Cochrane CKD review notes that astragalus injection has been associated with allergic reactions including allergic shock; 6 of its 22 trials reported no adverse effects and the other 16 did not report on them [22]. Bone and Mills: controlled studies suggest a low incidence of significant side effects, and "no adverse effects are expected if used as recommended" [5, pp. 382, 389]. Braun and Cohen: none known [7, p. 53].
Case reports (clinical). A 21-year-old man with atopic dermatitis developed oedematous erythema of both hands and feet about 18 hours after astragalus root was added to a Kampo decoction he had taken without trouble for three years; it cleared within 2 days of stopping, and he continued the original formula afterwards without recurrence. Astragaloside was negative on lymphocyte transformation testing and he declined rechallenge [48]. AIP causality assessment (WHO-UMC criteria): probable, on timing, positive dechallenge and tolerance of the base formula; the causative constituent is unknown. The authors cite two earlier eruption cases linked to astragalus-containing medicines, which were not read for this draft. A 2014 case report of raised CA19-9 with liver and kidney cysts attributed to astragalus is on order and is not assessed here until read.
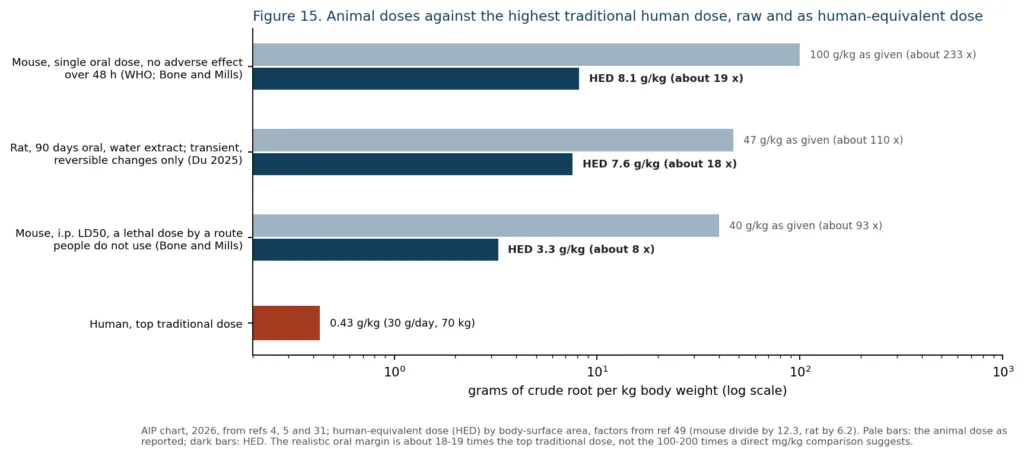
Toxicology (animal). No adverse effects within 48 hours of single oral doses of 75 and 100 g/kg in mice [4, p. 55; 5, p. 389]. Intraperitoneal LD50 in mice reported as 40 g/kg (Bone and Mills) or 39.8 g/kg (Mills et al.); in another study 50 g/kg i.p. produced no significant toxicity [5, p. 389; 8, p. 39]. A 3-month study of astragalus given by injection found no distinct toxicity up to 39.9 g/kg in rats and 19.95 g/kg in dogs [5, p. 389]. A 90-day study of a root water extract at 47 g crude drug/kg/day in rats found no mortality or organ pathology; food intake, rectal temperature and rotarod latency fell and recovered within the 30-day recovery period, so 47 g/kg is a dose with transient effects and not a clean no-effect level [31]. An aqueous extract at 1.25 mg/mL modestly raised aberrant cells (16 per cent) in vitro; other extracts were non-mutagenic in the Ames test or antimutagenic [4, p. 56; 5, p. 389; 8, p. 39]. Intravenous astragaloside IV was maternally toxic at 1.0 mg/kg and fetotoxic above 0.5 mg/kg in rats, without teratogenicity in rats and rabbits [5, p. 389]. AIP comment: converted to human-equivalent doses by body-surface area [49], the highest oral animal doses above (100 g/kg once in mice; 47 g/kg/day for 90 days in rats) are about 18–19 times the top traditional human dose of 30 g/day, and the 75 g/kg mouse dose about 14 times (Figure 15). That is a comfortable margin for acute and subchronic use, and a much smaller one than the raw mg/kg figures suggest.
Immune effect at high dose (secondary report). Mills et al. state that doses above 28 g/day may suppress immunity, citing a secondary reference work [8, pp. 39–40]. The primary source was not read and the claim is ungraded; it sits at the top of the traditional dose range (9–30 g/day), and is a reason not to push decoction doses beyond it without cause.
Contraindications (traditional). Acute infection, on traditional grounds (Bone and Mills; MediHerb; Braun and Cohen) [5, p. 389; 6, p. 26; 7, p. 54]. No trial has tested this rule. Bone and Mills list no other special warnings [5, p. 389].
Herb–drug interactions.
| Drug or class | Effect | Evidence grade | Reference |
|---|---|---|---|
| Immunosuppressants (transplant, autoimmune therapy) | Possible opposition of effect; Bone and Mills: "in principle, immune-enhancing herbs should not be given long-term to transplant recipients receiving immune-suppressing drugs"; Braun and Cohen: use caution in the immunosuppressed | Theoretical | [5, p. 389; 7, p. 53; 8, p. 40] |
| Cyclophosphamide | Reduced efficacy suggested in vivo; clinical relevance uncertain | Animal | [5, p. 389; 8, p. 40] |
| CYP1A2, CYP2C9 and CYP2C19 substrates | Root extract inhibited CYP1A2 and CYP2C9 in human liver microsomes (IC50 3.16 and 1.80 mg/mL); formononetin and daidzein inhibited CYP2C9 (IC50 5.63 and 6.60 µM); in rats at 0.9–3.6 g/kg the extract weakly inhibited CYP1A2 and induced CYP2C6 (the rat counterpart of CYP2C19), with no change in enzyme protein | In vitro and animal; the microsomal concentrations are unlikely to be reached in plasma after oral doses | [32] |
| Positive inotropes (e.g. digoxin) | Additive effect possible with intravenous astragalus; oral relevance unknown | Theoretical | [7, p. 53] |
| Chemotherapy | Braun and Cohen: possible benefit to wellbeing and nausea, to be combined only under professional supervision | Theoretical (clinical data mostly injected or multi-herb) | [7, p. 53] |
| General anaesthesia | MediHerb advises stopping 7 days before | Manufacturer advice; basis not given | [6, p. 26] |
No clinical or pharmacokinetic interaction study of the oral drug in people was among the sources read. A human P-glycoprotein study with fexofenadine (2013) is on order and is not cited here until read. MediHerb refers users to its herb–drug interaction chart [6].
Pregnancy (no human data). Bone and Mills place astragalus in category B1 of the Australian pregnancy categorisation (no increase in malformation from limited use in women; no fetal damage in animal studies of oral doses); this is the authors’ own assignment, not a TGA categorisation [5, p. 389]. Braun and Cohen: safety unknown, although no fetal damage has been reported in animal studies [7, p. 54]. Mills et al.: safety unknown, no report either way (their evidence level 5) [8, p. 38]. WHO: no data, so it should not be given in pregnancy [4, p. 56]. MediHerb: professional supervision suggested [6, p. 116]. Locoweed toxicity belongs to other Astragalus species; swainsonine has not been detected in this drug [5, p. 389; 8, pp. 38–39].
Lactation (no data). Bone and Mills: no data on safety in breastfeeding [5, p. 389]. Mills et al.: unknown (evidence level 5) [8, p. 39]. WHO: use not recommended, since excretion into milk is not established [4, p. 56]. MediHerb: professional supervision [6, p. 116].
AIP comment on pregnancy and lactation: there are no human data either way. The conservative course, which WHO takes, is to avoid it; where it is used, it should be only under the care of a degree-qualified herbalist with competencies and adequate training in pharmacognosy.
Children and older people. Children: limited information; adverse effects are not expected (Bone and Mills) [5, p. 389]. The Cochrane review found no placebo-controlled trial in children [21]. Older people: no source read gives advice specific to older adults; the theoretical interactions above (immunosuppressants, cardiac drugs) matter more in this group because they take more medicines.
Overdose. No incidents found in the published literature (Bone and Mills) [5, p. 389].
TGA safety alerts and DAEN. Searched in September 2026 by Medicine. TGA safety alerts and safety information: a search of the TGA website for "astragalus" found no safety alert, product recall or safety advisory; the one regulatory notice found was the cancellation of an ARTG listing (Bioglan Astragalus, ARTG 319762) under section 30(1)(c) of the Therapeutic Goods Act 1989, published among the TGA’s cancellations by sponsors, effective 16/06/2025 [50]. The TGA site’s own search page did not return results to automated access, so this rests on an indexed web search limited to tga.gov.au. The Database of Adverse Event Notifications opens only behind a terms-of-use page that could not be passed automatically, so DAEN has not been searched; this is to be done by hand before release.
Referral. For use alongside immunosuppressant, chemotherapy or cardiac medicines, in pregnancy or breastfeeding, or in serious illness, consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy.
27 more pages follow · 13,652 words, 31 figures, 13 tables
Still to come in this monograph
- 1. Nomenclature
- 2. Definition
- 3. Source and Australian supply
- 4. Macroscopy
- 5. Microscopy
- 6. Chemistry
- 7. Named markers and assay limits
- 8. TLC fingerprint
- 9. HPLC fingerprint
- 10. Identity, purity, adulterants and contaminants
- 11. Traditional use
- 12. Current practice: use, preparations and doses
- 13. Clinical evidence
- 14. Pharmacology
- 16. Discussion
- 17. Conclusions
- 18. Research still needed
- 19. References
- 20. Document control
The rest of this monograph is open to members. One membership covers every members’ feature on the site.
Checking your membership…
Report an error or submit evidence
If something in this monograph is wrong, out of date or missing, tell us and show us the evidence. Every report is logged under the AIP Evidence Charter and assessed on the evidence alone; the outcome is kept on the record, and an upheld report is corrected with a dated notice on this page.
Open the report form
The Institute sets and publishes its own monographs. The catalogue is in Publications.


