


Echinacea angustifolia root (Echinacea angustifolia DC.), Asteraceae
Australian Herbal Pharmacopoeia (working title), Monograph AIP-PH-ECHANG (formerly AIP-HP 004)
Status: version 1.0, live at https://www.australian-pharmacognosy.org/pharmacopoeia/echinacea-angustifolia/, all reviews and the pre-publication final test on record. Published at first draft under the CEO’s order. Botanical, QA and Medicine reviews and the Education and Research evidence and citation audit done in 2026; not reviewed by Legal.
Date: 2026. Next review: on sign-off, then three-yearly or sooner if a major trial, safety signal or new pharmacopoeial text appears.
Prepared by: the Australian Institute of Pharmacognosy, Far North Queensland, Australia. Every author and contributor is named at the end of the monograph.
Contributors: Dr Thomas Ridley (library and literature search, registry search, synthesis, drafting, figure sourcing and placement, AIP schematics and charts, reference verification). Section reviewers named in 0.1 are credited once they have reviewed. Dr Luke Iggulden, Chief Scientific Officer, is senior author: he set the scope of the series in the CEO directive and made the research possible.
0. Free teaser
0.1 Identity card
| Monograph | AIP-PH-ECHANG (formerly AIP-HP 004), Echinacea angustifolia root. Version 1.0, 22/09/2026. Next review: on sign-off |
| Accepted name | Echinacea angustifolia DC., Asteraceae (APG IV). Accepted in WCVP/POWO (WCVP release 16/09/2026, read in September 2026; IPNI 87143-2) [1] |
| Synonyms | Homotypic: Brauneria angustifolia (DC.) A.Heller; Echinacea pallida var. angustifolia (DC.) Cronquist. Heterotypic: Echinacea angustifolia var. strigosa McGregor [1]. TGA ARTG and MediHerb: Echinacea angustifolia [9,26] |
| Drug name | Echinaceae angustifoliae radix, narrow-leaved coneflower root (Ph. Eur. 1821) [3]; WHO title Radix Echinaceae (covers E. angustifolia and E. pallida) [4] |
| Common names | Narrow-leaved coneflower, narrow-leaved purple coneflower, black sampson, Kansas snakeroot, Indian head (English); Schmalblättriger Sonnenhut (German); échinacée à feuilles étroites (French) [4,5] |
| Pharmacopoeial status | Ph. Eur.: monograph 01/2008:1821, corrected 6.0 (read in the Ph. Eur. 8.0 library copy) [3]. WHO monographs vol. 1 (1999): yes, as Radix Echinaceae [4]. EMA/HMPC: Community herbal monograph, traditional use, 2012 [5,6]. USP-NF and BP: monographs recorded by Mills and Bone (USP31-NF26 2008; BP 2012) [2]. BHP 1974 and 1983: listed, as recorded by the HMPC [6] |
| Australian status | Present in ARTG-listed medicines: the tablet used in two trials is AUST L 75124 [18]. Permissible Ingredients Determination and Poisons Standard entries not re-read for this draft (QA to confirm before release). Not native to Australia; no Atlas of Living Australia records under this name [19] |
| Assay marker | Echinacoside (CID 5281771): not less than 0.5 per cent, dried drug (Ph. Eur. 1821, HPLC at 330 nm) [3] |
| Identity markers | Echinacoside with cynarin (CID 5281769) on TLC and HPLC; absence of the cichoric acid zone excludes E. purpurea [3]. Cynarin separates E. angustifolia from E. pallida [4]. Alkamides (dodeca-2E,4E,8Z,10E/Z-tetraenoic acid isobutylamides, CID 6440539) are the manufacturer’s standardisation marker [9] |
| Evidence snapshot | Common cold prevention, E. angustifolia root alone: Tier C, 1 RCT plus 1 challenge trial, no significant benefit. Common cold treatment, E. purpurea plus E. angustifolia root tablets: Tier B, 1 large RCT, non-significant trend. Respiratory symptoms in air travel (same tablets): Tier C, 1 RCT, borderline. Wounds, skin and septic conditions: Tier T. Immune modulation: Tier P |
| Main safety point | Allergy, including anaphylaxis. Avoid with Asteraceae allergy, past severe allergy, or a reaction to echinacea or andrographis (TGA 2024 [29]). Theoretical concern with immunosuppressants |
| Suggested citation | Ridley T, Iggulden L. Echinaceae angustifoliae radix (echinacea angustifolia root, Echinacea angustifolia DC.). Australian Herbal Pharmacopoeia monograph AIP-PH-ECHANG (v1.0). Cardwell (QLD): Australian Institute of Pharmacognosy; 2026. DOI to be assigned |
| Compiler and review | Compiled by Dr Thomas Ridley (Education and Research). Technical review: Dr Fiona MacAllister (Botanical, sections 1-5, 10), reviewed in 2026; Dr Hana Suzuki (QA, sections 6-10), reviewed in 2026; Dr Eleanor Whitcombe (Medicine, sections 12, 13, 15), reviewed in 2026; Dr Thomas Ridley (Education and Research evidence and citation audit, sections 6-9 sources, 12, 13, 15, 16-19 and figures), reviewed in 2026 (compiler’s own audit; independent reference audit by the Librarian pending). Jesse Kirby (Community Outreach, figures and whole-document layout), reviewed in 2026. Published: 2026. Last modified: 2026. Version 1.0 |
| Provenance | Original AIP data: none. Every limit, method, measurement and trial result comes from the cited pharmacopoeias, regulators, reference works and papers; sections 4, 5, 8, 9 and 10 are marked "AIP bench data pending" |
| Canonical URL | /pharmacopoeia/echinacea-angustifolia/ |
0.2 Summary
Echinacea angustifolia root is the dried root and rhizome of the narrow-leaved coneflower, a low prairie perennial of the central Great Plains of North America. The crude drug is a greyish-brown, sometimes spirally twisted root with a short fracture and a radiate cut surface; under the microscope it shows long bundles of lignified fibres edged with black phytomelanin, groups of sclereids, oleoresin canals with orange content and abundant inulin. The European Pharmacopoeia identifies it by thin-layer and liquid chromatography of its caffeic acid esters and requires at least 0.5 per cent echinacoside. Cynarin is present in this species and absent from E. pallida, the substitute most often sold in its place; Parthenium integrifolium and wrongly labelled seed stock are the other documented problems. Practitioners use the root, usually as a 1:2 liquid or tablet blended with E. purpurea root, to prevent and treat upper respiratory infections and for skin and wound conditions. Randomised trials of the root alone found no significant benefit; one large trial of a root blend showed a non-significant trend. The evidence is weak and conflicting. The main safety concern is allergy in people sensitive to the daisy family. Anyone considering it should consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy.
0.3 Contents and extent (draft)
| Section | Approx. pages |
|---|---|
| 1-3 Nomenclature, definition, source and Australian supply | 2 |
| 4-5 Macroscopy and microscopy (6 figures, 1 placeholder) | 3 |
| 6-7 Chemistry, markers and limits (8 structures) | 2.5 |
| 8-9 TLC and HPLC (3 figures) | 2 |
| 10 Identity, purity, adulterants, contaminants | 1.5 |
| 11 Traditional use | 1 |
| 12 Current practice and doses | 1 |
| 13 Clinical evidence (search, graded trials, registries, 2 charts) | 4 |
| 14 Pharmacology | 1.5 |
| 15 Safety | 2 |
| 16-18 Discussion, conclusions, research needed | 1.5 |
| 19-20 References and document control | 3 |
| Totals (draft) | About 25 A4 pages before layout; 16 tables; 20 embedded figures plus 1 captioned placeholder (2 licensed photographs of the living plant, 2 public-domain plates, 1 licensed root photograph, 8 PubChem structures, 3 AIP schematics labelled as redrawn from Ph. Eur. and WHO text, 1 licensed published chromatogram, 1 AIP range map, 2 AIP data charts); 0 photomicrographs; 1 chromatogram (published, ref 14). Gaps: F4 photomicrographs are AIP bench data pending, no licensed alternative found; AIP TLC plate and HPLC run pending (F7 is a schematic; F8 is a published licensed chromatogram). Trials: 7 randomised trials described, 5 graded, plus 1 Cochrane review. 31 references: 29 read in full, 2 trial reports (refs 30, 31) read as PubMed abstracts only |
0.4 Contributors and access
Prepared by the Australian Institute of Pharmacognosy. Botanical, QA and Medicine reviews and the Education and Research evidence and citation audit done 22/09/2026; Librarian reference audit pending; A Legal read is advisory only and does not gate publication (CEO order 22/09/2026). The Australian Herbal Pharmacopoeia is AIP’s own series and carries no statutory, TGA or government standing. The full monograph is for subscribers (paywall wording to come from Legal and Community Outreach).
1. Nomenclature
- Accepted name: Echinacea angustifolia DC. (Asteraceae), accepted in WCVP (release 16/09/2026, via ChecklistBank dataset 2000), IPNI 87143-2 [1]; POWO web page refused access (HTTP 403) in September 2026.
- Synonyms (WCVP): homotypic Brauneria angustifolia (DC.) A.Heller and Echinacea pallida var. angustifolia (DC.) Cronquist; heterotypic E. angustifolia var. strigosa McGregor [1]. The WHO lists E. angustifolia var. angustifolia and var. strigosa McGregor as the source varieties and gives Brauneria angustifolia Heller and E. pallida var. angustifolia (DC.) Cronq. as synonyms [4].
- Taxonomic dispute: McGregor’s 1968 revision recognised nine species and four varieties and separated E. angustifolia from E. pallida [2,4]. A morphometric revision of 2001-2002 reduced it to E. pallida var. angustifolia; Mills and Bone record that this is still disputed [2]. WCVP treats that name as a synonym and keeps E. angustifolia DC. at species rank [1]. Ph. Eur., the EMA, MediHerb and the trials use E. angustifolia [3,5,9,16]. Aiello and colleagues note that some populations of E. angustifolia var. strigosa are tetraploid, like E. pallida [13].
- Authority written two ways: Ph. Eur. prints "Echinacea angustifolia (D.C.)" and Mills and Bone "(DC.) Hell."; the accepted form is E. angustifolia DC. [1,2,3].
- Family: Asteraceae (Compositae), APG IV; no recent change [1].
- Common names: narrow-leaved coneflower, American coneflower, black sampson, cock-up-head, Indian head, Kansas snakeroot, purple coneflower (English); Igelkopf, Kegelblume, Sonnenhut, Schmalblättriger-Sonnenhut-Wurzel (German); racine d’échinacée (French) [4,5]. Henkel (1907) adds pale-purple coneflower and Sampson-root [11]; a further name in that source is a racial slur and is not reproduced.
- Drug name and state: Echinaceae angustifoliae radix, the dried, whole or cut underground parts [3]. The WHO definition also admits fresh root and pools E. angustifolia with E. pallida under one title [4]; this monograph covers the dried root of E. angustifolia alone.
- Trade names in Australia: ARTG ingredient name "Echinacea angustifolia", without author (ARTG 384690, read in September 2026) [26]; MediHerb "Echinacea Angustifolia Root 1:2" (botanical name Echinacea angustifolia, part root) and "Echinacea Premium Blend 1:2" (60% E. purpurea root 1:2 with 40% E. angustifolia root 1:2); the A-Z work list also records Echinacea Premium and Andrographis Complex tablets [9].
- Name confusion: "Echinacea" on a label identifies neither species nor plant part. E. pallida was sold in Europe as E. angustifolia for years, and the WHO advises that data on "E. angustifolia" published before 1987 from European commercial material be read with caution [4].
2. Definition
The dried, whole or cut underground parts of Echinacea angustifolia DC., containing not less than 0.5 per cent of echinacoside (C35H46O20; Mr 786.5), calculated with reference to the dried drug.
Basis: Ph. Eur. monograph 01/2008:1821, corrected 6.0, as printed in the 8.0 edition held in the library [3]; the HMPC assessment report quotes the same definition [6]. The WHO set no minimum and gives a range of 0.4-1.7 per cent echinacoside for E. angustifolia and E. pallida roots [4]. Echinacoside is an assay marker; it is not shown to carry any clinical effect (sections 6.4 and 14). QA is asked to confirm the definition against the Ph. Eur. edition in force before release.
3. Source and Australian supply
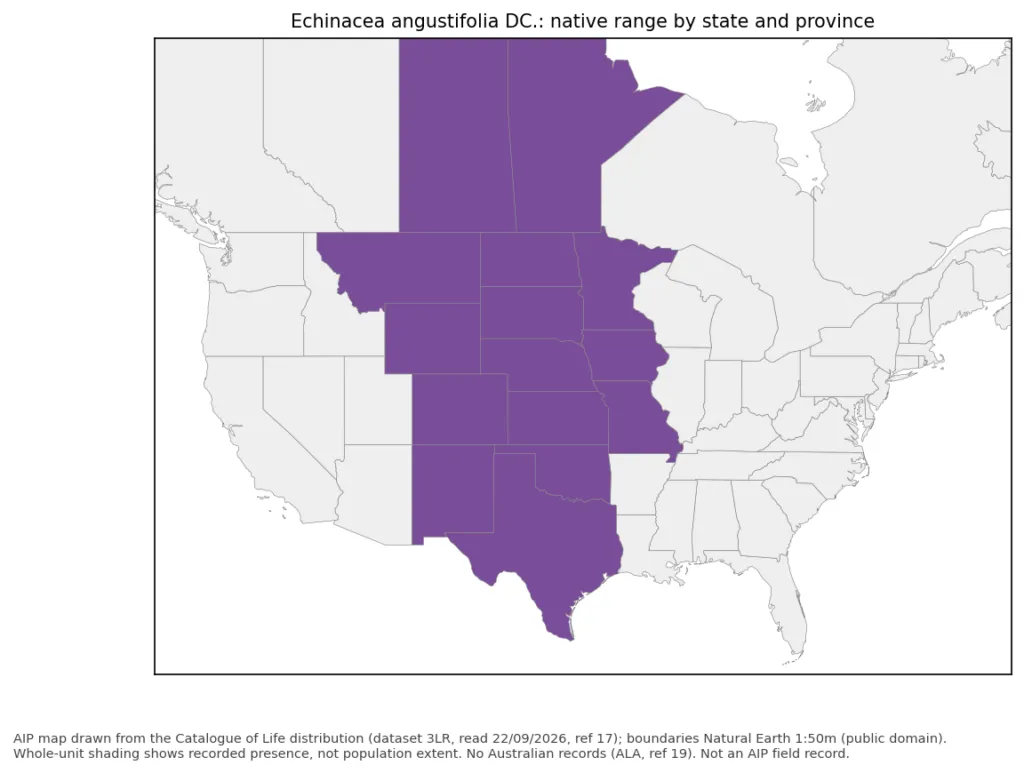
Native range. Central North America. The Catalogue of Life (dataset 3LR, read in September 2026) records it in Canada (Manitoba, Saskatchewan) and in 13 US states: Colorado, Iowa, Kansas, Minnesota, Missouri, Montana, Nebraska, New Mexico, North Dakota, Oklahoma, South Dakota, Texas and Wyoming [17]. The WHO places the genus in the Atlantic drainage of the USA and Canada, with centres in Arkansas, Kansas, Missouri and Oklahoma [4]; Henkel described it in rich prairie or sandy soil, most abundant in Kansas and Nebraska [11]. GBIF did not respond on 22/09/2026, so no occurrence-point map is given.
Free to every reader. The safety section of every monograph is open to everyone, signed in or not. In an emergency call 000. For poisoning, call the Poisons Information Centre on 13 11 26.
15. Safety
15.1 Adverse effects in trials
In Melchart’s trial, 18 of 100 people on E. angustifolia root extract reported adverse effects against 11 of 90 on placebo; none was serious [6] (Mills and Bone give the same counts [2]). The HMPC found no serious adverse events or deaths reported [6]. In the Cochrane review, drop-outs and adverse effects did not differ significantly from placebo, with a trend towards more drop-outs for adverse events in prevention trials [15]. The EU monograph lists skin hypersensitivity reactions, frequency not known [5]; the WHO lists allergic reactions, shivering, fever and headache [4].
15.2 Allergy
An Australian case of anaphylaxis in an atopic woman who took a commercial E. purpurea and E. angustifolia extract with many other supplements, at twice the recommended amount, was published in 1998 (Mullins, as reported by Mills and Bone and Braun and Cohen [2,8]). A 2002 Australian series described five reactions (two anaphylaxis, two asthma exacerbations, one rash), three with positive skin-prick tests; 20 per cent of 100 atopic people who had never taken echinacea also had positive skin-prick tests; 51 reports had reached ADRAC over 21 years; about half suggested allergy, and of those two were judged certainly, 10 probably and 12 possibly linked to echinacea (as reported by Mills and Bone and Braun and Cohen [2,8]). Mills and Bone note that it is unclear whether any of these products contained the root [2]. Mills and Bone judge root preparations less likely to cause allergy than aerial parts, which carry pollen [2]. The HMPC advises caution in atopic people and people with asthma [6]. TGA safety advisory, 02/07/2024 (issued for Andrographis paniculata): more than 80 per cent of andrographis adverse-event reports to the TGA involved multi-ingredient products that also contained echinacea; the TGA states that echinacea has also been reported to cause allergic reactions including anaphylaxis, that people with a history of severe allergy including anaphylaxis should avoid medicines containing andrographis and/or echinacea, and that anyone who reacts to a product containing either should avoid both in future, because later reactions may be more severe [29].
15.3 Contraindications and precautions (each with source and grade)
| Situation | Position | Source | Grade of evidence |
|---|---|---|---|
| Allergy to Asteraceae | Contraindicated (EMA, WHO, Braun and Cohen); caution (MediHerb, Mills and Bone) | [2,4,5,8,9] | Case reports and case series |
| History of severe allergy or anaphylaxis to any trigger | Avoid (TGA advisory) | [29] | Regulator pharmacovigilance (spontaneous reports) |
| Previous allergic reaction to an echinacea- or andrographis-containing product | Avoid both in future (TGA advisory) | [29] | Regulator pharmacovigilance (spontaneous reports) |
| Atopy, asthma | Caution (EMA, HMPC); Mills and Bone find no sound evidence for caution in asthma | [2,5,6] | Case series; sources disagree |
| Progressive systemic disease (tuberculosis, leukaemia, collagenoses, multiple sclerosis, HIV/AIDS, autoimmune disease) | Not recommended (EMA, WHO); not supported by evidence (Mills and Bone, Braun and Cohen) | [2,4,5,8] | Theoretical; no clinical data |
| Long-term immunosuppressant therapy (for example transplant) | Contraindicated long-term; short-term only (MediHerb, Mills and Bone) | [2,9] | Theoretical |
| Children under 12 | Not recommended (EMA; no adequate data); WHO: oral use not recommended in children without professional advice | [4,5] | No data |
| Pregnancy and lactation | Not recommended (EMA; WHO for pregnancy, and nursing mothers only with professional advice); professional supervision (MediHerb); category A in Mills and Bone’s pregnancy scheme, which they adapted from the Australian Medicines in Pregnancy categories | [2,4,5,9] | One prospective cohort, species not identified (see 15.5) |
| General anaesthesia | Stop 7 days before (MediHerb) | [9] | Manufacturer precaution; no data cited |
15.4 Herb-drug interactions
| Drug or class | Finding | Grade |
|---|---|---|
| Immunosuppressants | Possible antagonism; no case reports | Theoretical [2,8] |
| CYP1A2 and CYP3A4 substrates | Low potential for CYP interactions; no verifiable interaction reports (Freeman and Spelman 2008, as reported by the HMPC for E. angustifolia [6]; Mills and Bone describe the same review as mainly about E. purpurea [2]). The EU monograph lists no interactions [5] | Review of PK studies |
| CYP3A4 | Commercial E. angustifolia root extract inhibited CYP3A4 in a fluorometric screen, IC50 1-2% of full strength (Budzinski 2000 [6]); alkylamides inhibited CYP3A4, 2D6 and 2C19 in vitro, which human studies suggest is not clinically relevant [2] | In vitro |
| Warfarin | No change in warfarin pharmacodynamics; plasma S-warfarin reduced (Abdul 2010, as reported by Mills and Bone [2]) | Human pharmacokinetic study |
| Darunavir/ritonavir | No overall pharmacodynamic change (Moltó 2011, as reported by Mills and Bone [2]) | Human pharmacokinetic study |
| Cytotoxic drugs | E. angustifolia preparations reduced the effect of 5-fluorouracil and other agents on cancer cells in vitro (Jensen 2006-2007 [6]) | In vitro |
15.5 Pregnancy and lactation
A prospective controlled cohort of 206 women who took echinacea in pregnancy (112 in the first trimester) found no difference in major malformations from 206 matched controls; species and plant part were not specified (Gallo 2000, as reported by the HMPC, Mills and Bone and Mills et al. [6,2,12]). Mills and colleagues rate pregnancy "minimal risk, evidence level 1b" and lactation "minimal risk, evidence level 4" [12]. In pregnant mice fed E. purpurea, viable fetuses were reduced (Chow 2006, as reported by Mills and Bone [2]). The EU monograph does not recommend use in pregnancy and lactation for lack of data [5]; the WHO does not generally recommend it in pregnancy and advises nursing mothers to take it only with professional advice [4]. Mills and Bone place it in category A of their pregnancy scheme and judge it compatible with breastfeeding, noting that about 0.5 per cent of the maternal alkylamide dose reached the infant in one breastfeeding woman [2]. No reproductive toxicity study of E. angustifolia root exists [6].
AIP comment (Medicine, Dr Eleanor Whitcombe, 22/09/2026): the human evidence is one prospective cohort of 206 exposures, mostly 5-7 day courses, with no species or plant part recorded. It found no rise in major malformations, but it is too small to exclude less common harms and it cannot be assigned to this root. Certainty is very low. AIP does not recommend routine use in pregnancy or lactation. Where a practitioner judges a short course worthwhile, the evidence covers only short courses at standard doses, and the allergy precautions in 15.2 apply.
15.6 Children and older people
No adequate data in children; the EU monograph does not recommend use under 12 [5], and the WHO does not recommend oral use in children without professional advice [4]. Mills and Bone have no specific information for the root in children [2]. No specific data in older people.
15.7 Toxicology and overdose
Animal studies of Echinacea preparations indicate low toxicity; reproductive, genotoxicity and carcinogenicity tests on E. angustifolia root preparations have not been done, so no EU list entry was made [5,6]. The WHO reports negative mutagenicity and carcinogenicity tests on Echinacea preparations, without stating that they used this species [4]. The saturated pyrrolizidine alkaloids carry no hepatotoxic structure [4,6]. No overdose case is reported [5]. Case reports attributed to echinacea (species and part usually unstated) include erythema nodosum, leukopenia, aggravation of autoimmunity, acute hepatitis and hypereosinophilia [2]; causality has not been assessed for any of them, and none is known to involve this root.
TGA checks (Dr Eleanor Whitcombe, 22/09/2026). TGA safety alerts: the 02/07/2024 andrographis advisory covers echinacea and is summarised in 15.2 [29]; no other TGA safety alert naming echinacea was found by site search. TGA DAEN (medicines): attempted September 2026; the DAEN is now a session-based portal behind a terms-of-use page and returned no data to an automated query. A manual DAEN pull for "Echinacea" (all species) is outstanding before release. The ADRAC figures in 15.2 are from 2002 and do not stand in for it.
15.8 Referral
Anyone with a known daisy-family allergy, asthma or atopy, an autoimmune or progressive systemic disease, a transplant or immunosuppressant treatment, or who is pregnant or breastfeeding should consult a degree-qualified herbalist with competencies and adequate training in pharmacognosy before using Echinacea angustifolia root. Anyone who has had anaphylaxis to anything, or an allergic reaction to an echinacea or andrographis product, should avoid it (TGA advice [29]). Throat or tongue swelling, wheeze, hives or faintness after a dose is an emergency: call 000.
Inside the typeset monograph
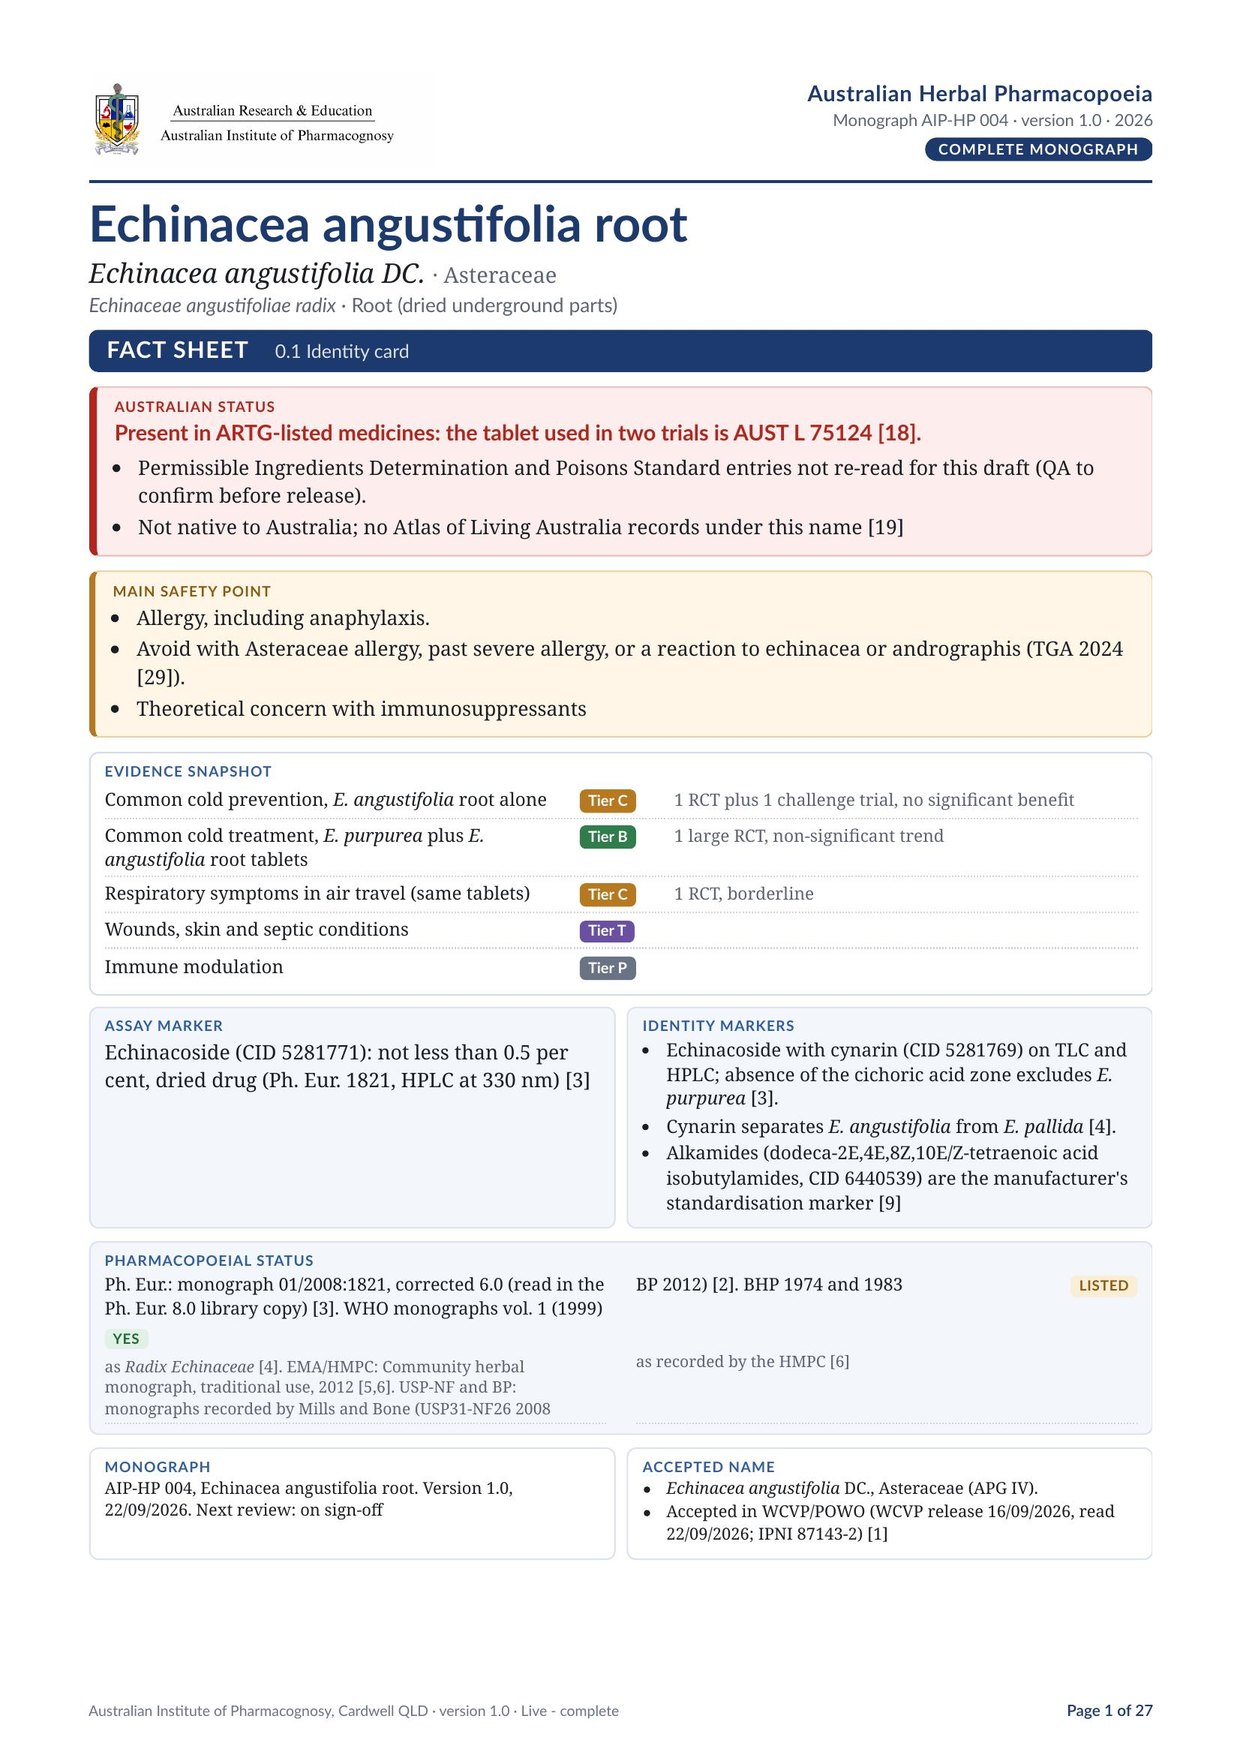







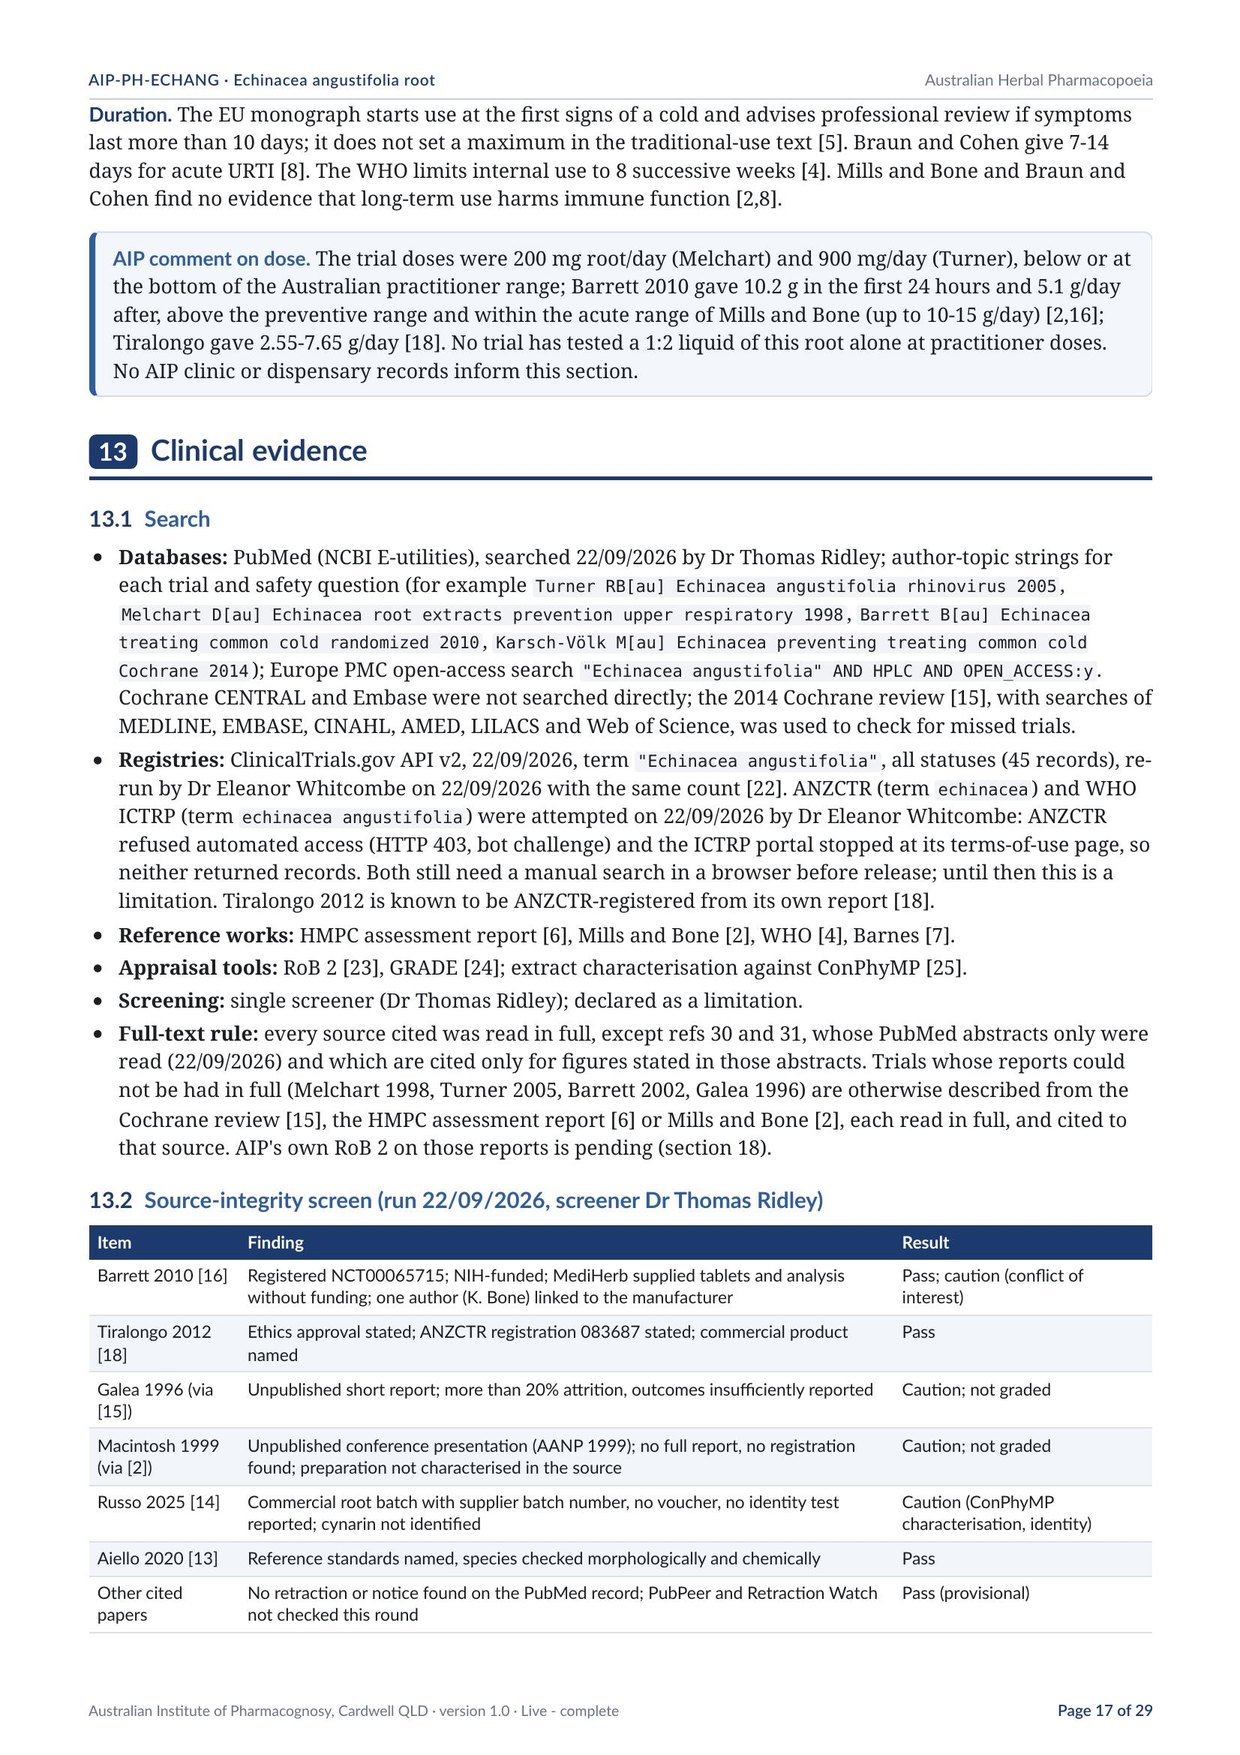

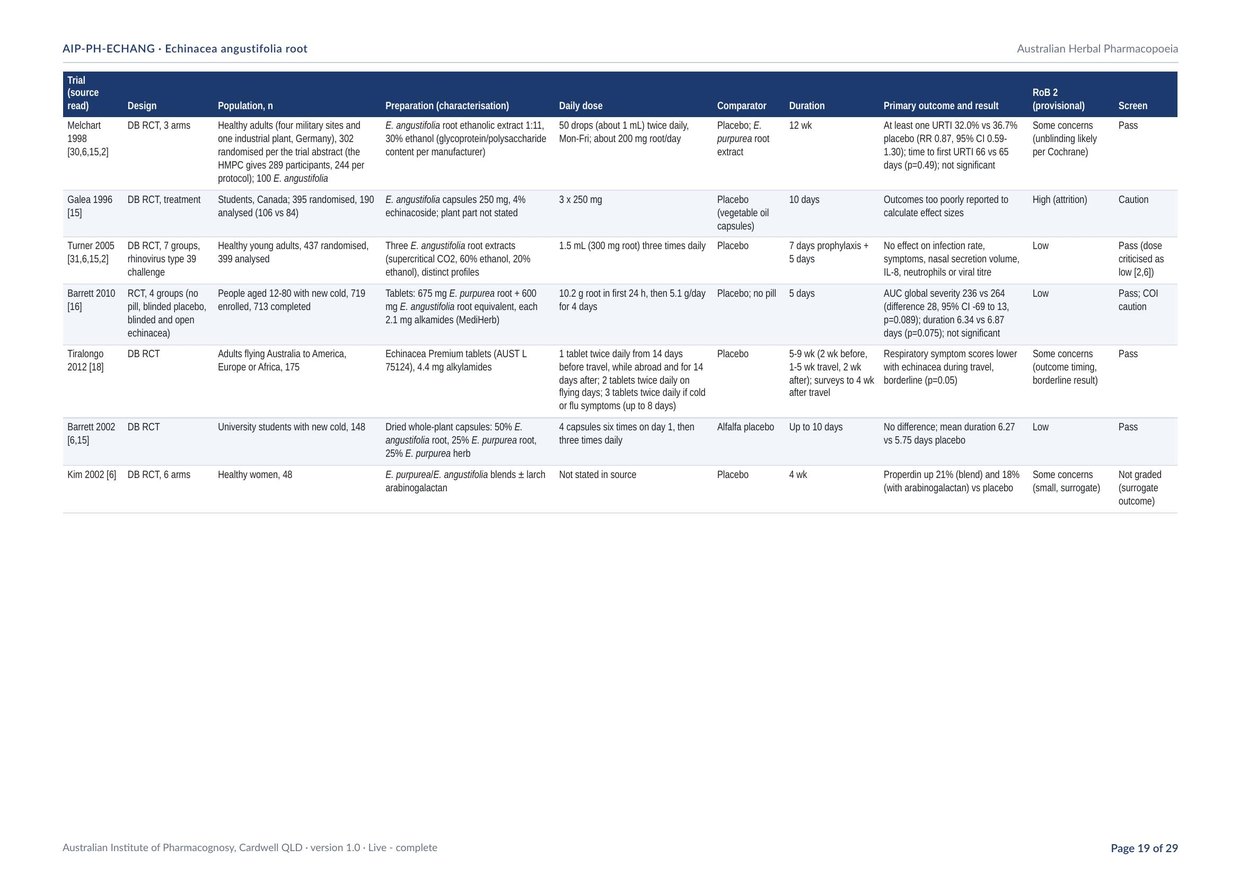
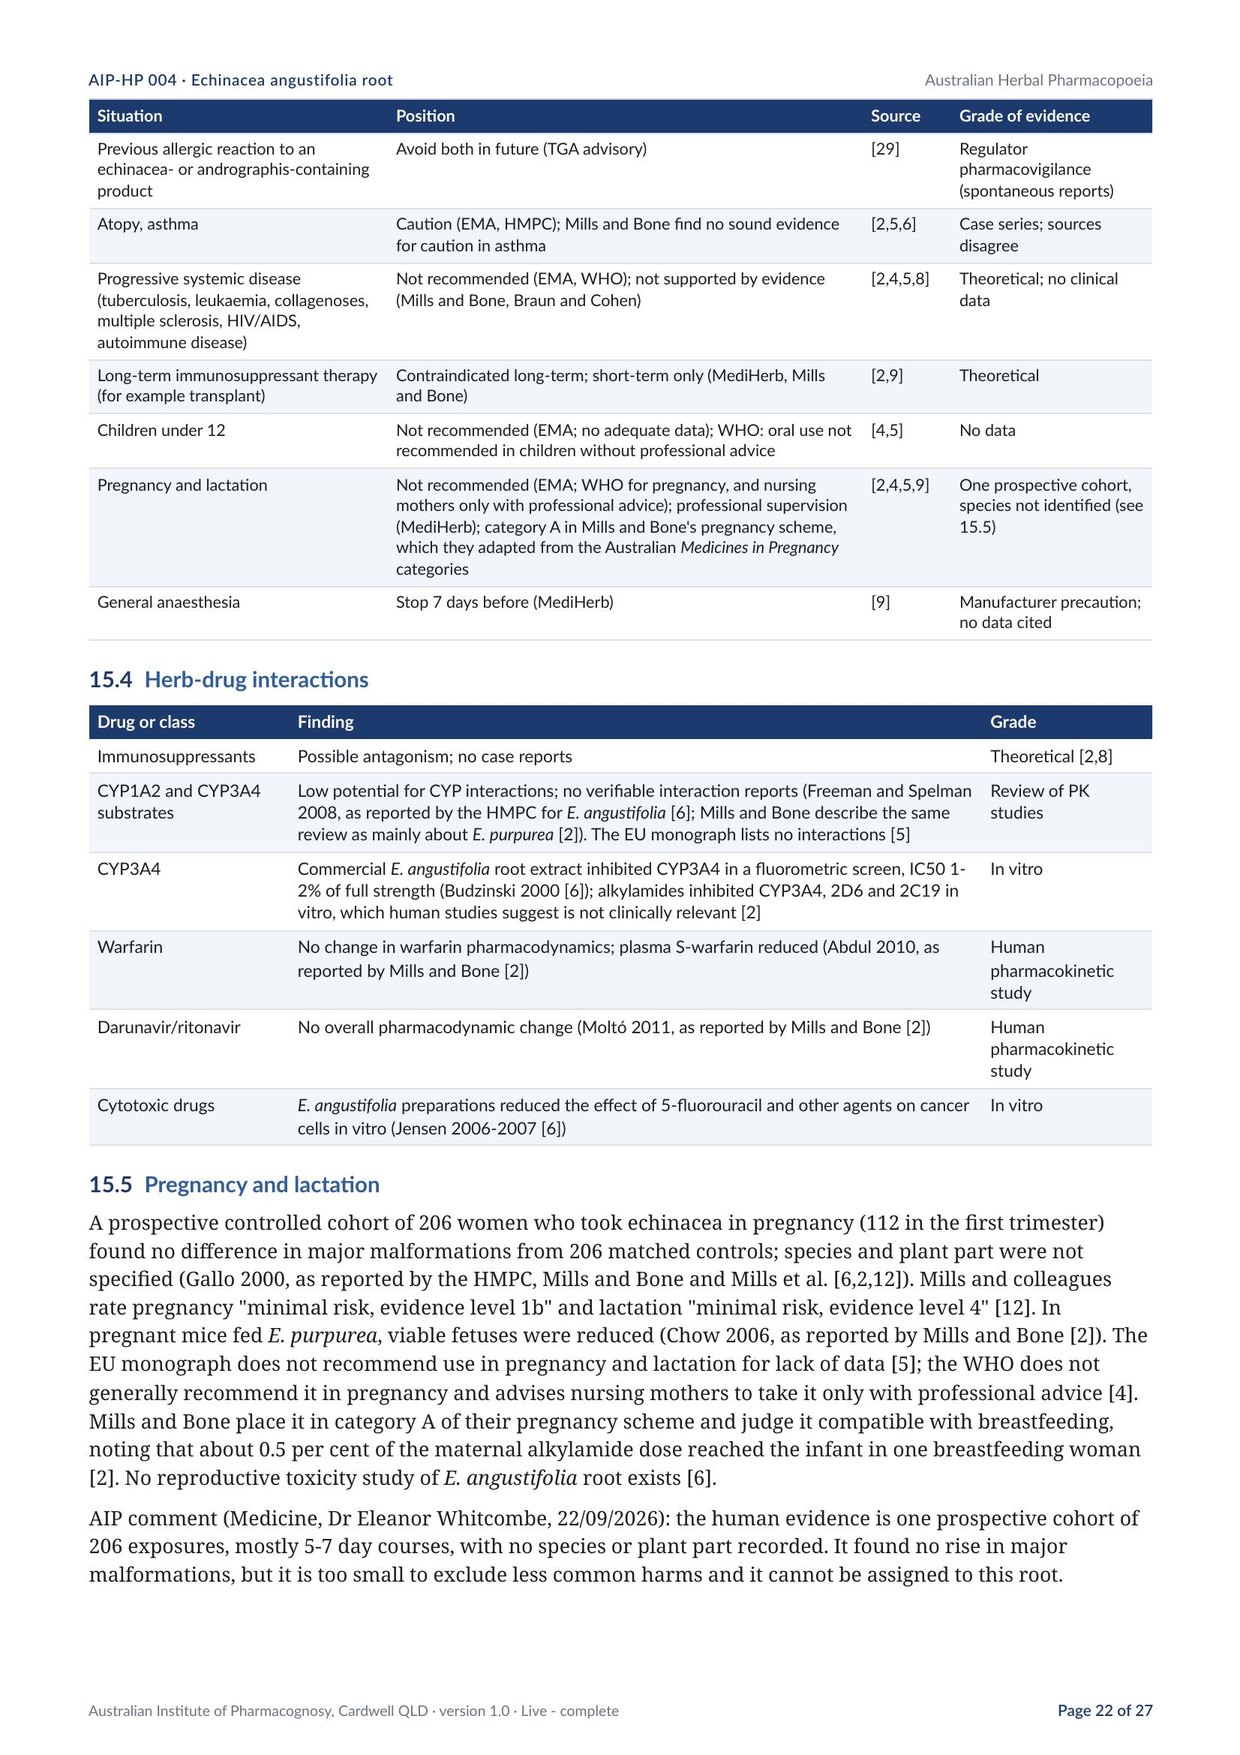
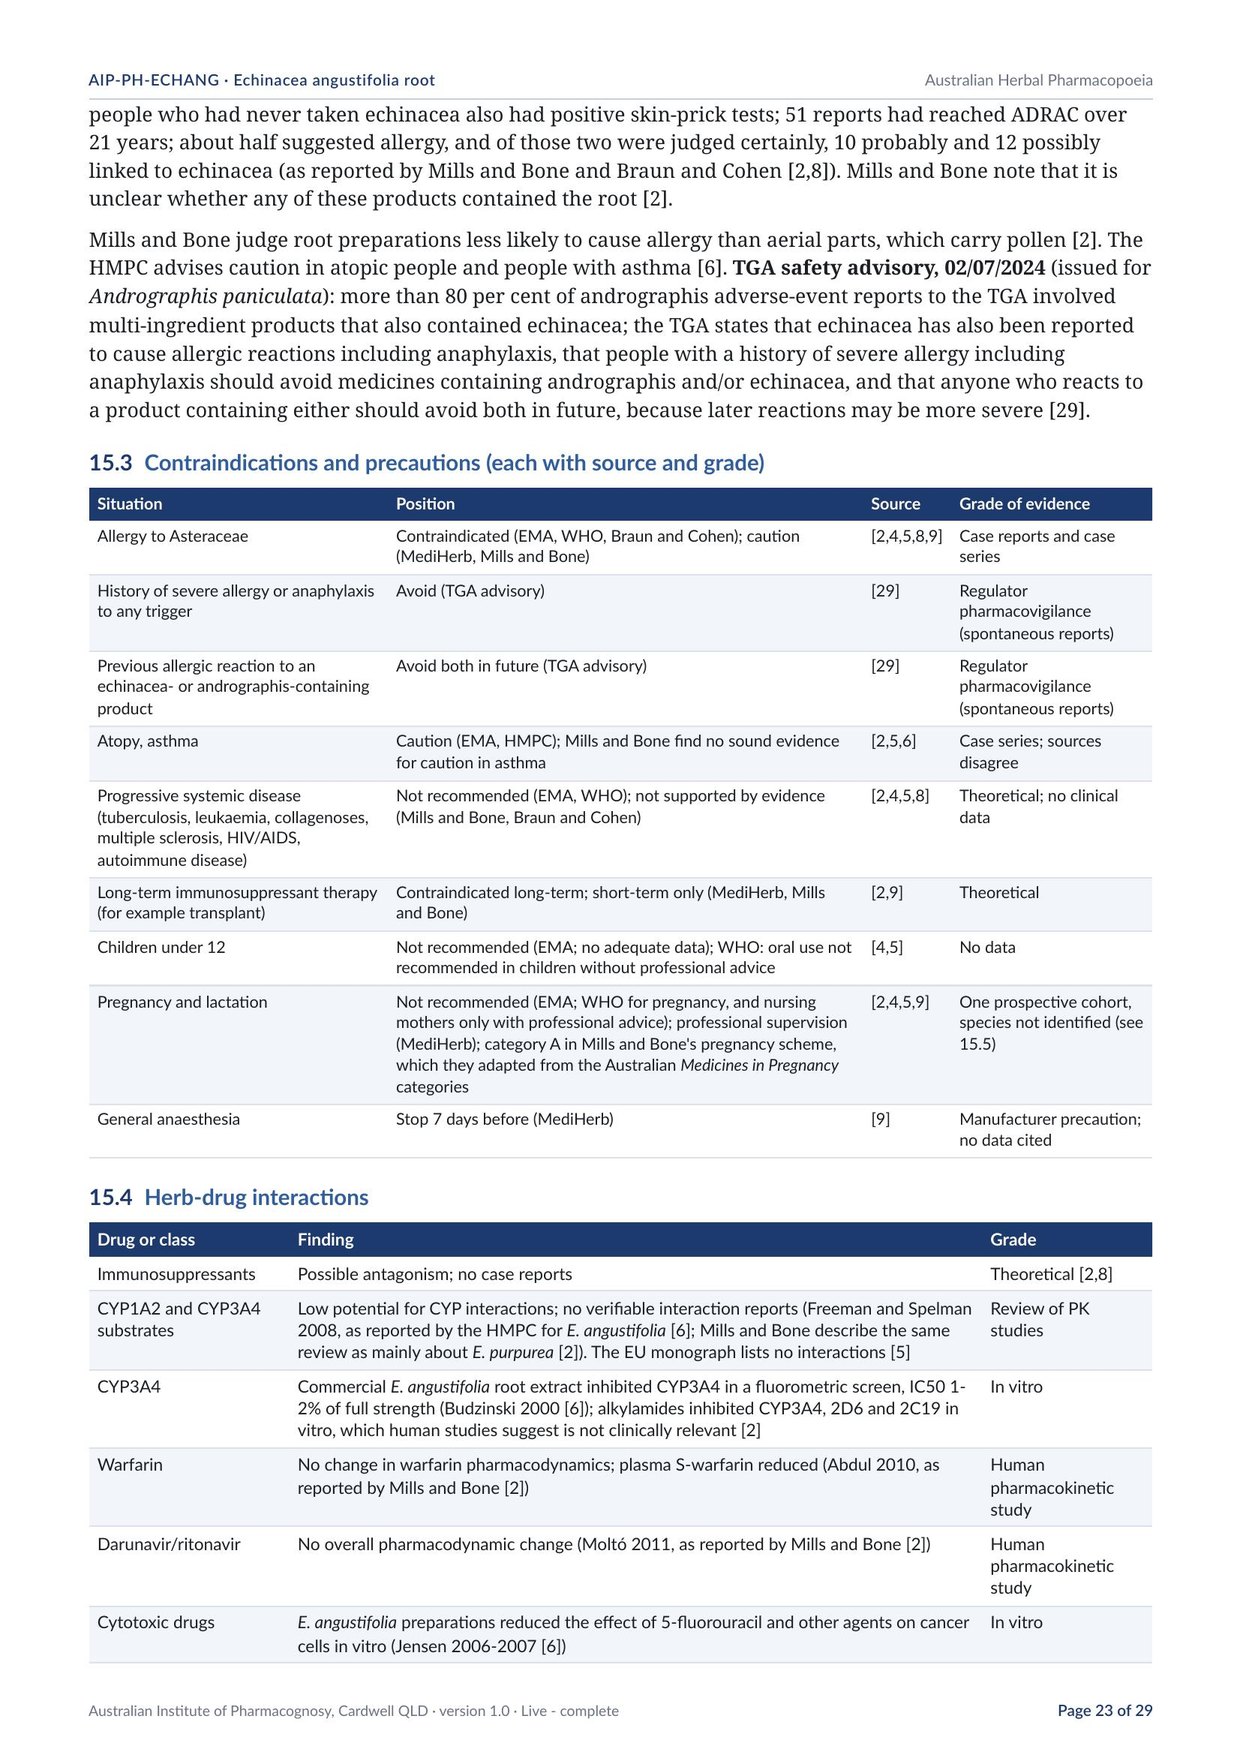



Tap a page to open it big enough to read.
9 pages read at full size, the safety section among them. The pages shown small are in the full monograph.
- 29 pages, read in the AIP Reader
- Version 1.0
- Licence personal, for life, one screen at a time
AUD $20this monograph in full, in the AIP Reader
The preview and the safety section are free, with no account and no sign-in. The microscopy, the chemistry, the TLC and HPLC fingerprints and the rest read in the AIP Reader, on this AUD $20 licence or a Scholar membership.
20 more pages follow · 10,247 words, 19 figures, 16 tables
Still to come in this monograph
- 4. Macroscopy
- 5. Microscopy
- 6. Chemistry
- 7. Named markers and assay limits
- 8. TLC fingerprint
- 9. HPLC fingerprint
- 10. Identity, purity, adulterants and contaminants
- 11. Traditional use
- 12. Current practice: use, preparations and doses
- 13. Clinical evidence
- 14. Pharmacology
- 16. Discussion
- 17. Conclusions
- 18. Research still needed
- 19. References
- 20. Document control
The rest of this monograph reads in the AIP Reader: every page in your name, always the current version, on a Scholar membership or the AUD $20 copy of this one title.
Checking your membership…
Report an error or submit evidence
If something in this monograph is wrong, out of date or missing, tell us and show us the evidence. Every report is logged under the AIP Evidence Charter and assessed on the evidence alone; the outcome is kept on the record, and an upheld report is corrected with a dated notice on this page.
Open the report form
The typeset edition of this monograph, set for print with the plates and chromatograms at full size, is $20 AUD in Publications.


